Alveolar Capillary Dysplasia With Misaligned Pulmonary Veins (ACDMPV): Description of Two Cases and Literature Review
Related Experiment Video
Updated: Jun 23, 2026
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Eleonora Guasti1, Giacomo Tardini2, Silvia Buratti3
1Department of Neurosciences, Rehabilitation, Ophthalmology, Genetics, Maternal and Child Health, University of Genoa, Genoa, Italy.

Introduction:
Alveolar capillary dysplasia with misaligned pulmonary veins (ACDMPV) is one of the major causes of neonatal interstitial lung disease, causing persistent pulmonary hypertension (PH) of the newborn, although symptoms can present later in infancy. Two patients were recently diagnosed with ACD at our Institution and prompted us to perform a structured review of the condition.
Methods:
We considered published articles from 2018 to 2025. The final population analyzed was composed of 165 patients, including our cases. From each publication, we extrapolated: clinical presentation, radiological reports, genetic and histopathological features, treatment, and outcome.
Results:
Respiratory failure due to PH during the neonatal period is typical, but a later and atypical presentation is possible (feeding problems, failure to thrive). Congenital malformations can be associated, including abdominal, cardiac, and genitourinary abnormalities. Radiological exams rule out other causes of hypoxemia, but a final diagnosis of ACD requires genetic or histological confirmation. The unique curative therapy is lung transplant; intensive support therapy (mechanical ventilation, vasoactive and pulmonary vasodilator drugs) is invariably needed. Extracorporeal membrane oxygenation (ECMO) was utilized in 45 patients and should be considered when medical therapy and mechanical ventilation are insufficient. The average survival for ACD-affected patients who do not receive a lung transplant is 7 months (mean value, outliers excluded). Ten patients received lung transplants; the average survival was 81 months (mean value, outliers excluded); six of them were alive at the time of publication. Improvements in intensive support therapy can improve clinical conditions and survival to the transplant target weight. Studies on genetic targets are in progress.
More Related Videos
 08:34
Left Atrial Stenosis Induced Pulmonary Venous Arterialization and Group 2 Pulmonary Hypertension in Rat
Published on: November 18, 2018
 13:10
Direct Re-implantation of Left Coronary Artery into the Aorta in Adults with Anomalous Origin of Left Coronary Artery from the Pulmonary Artery (ALCAPA)
Published on: April 24, 2017
Related Concept Videos
 01:27
Mitral Valve Prolapse I: Introduction
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:10
Atelectasis II: Pathophysiology
 01:18
Pulmonary Edema II: Pathophysiology
 01:23
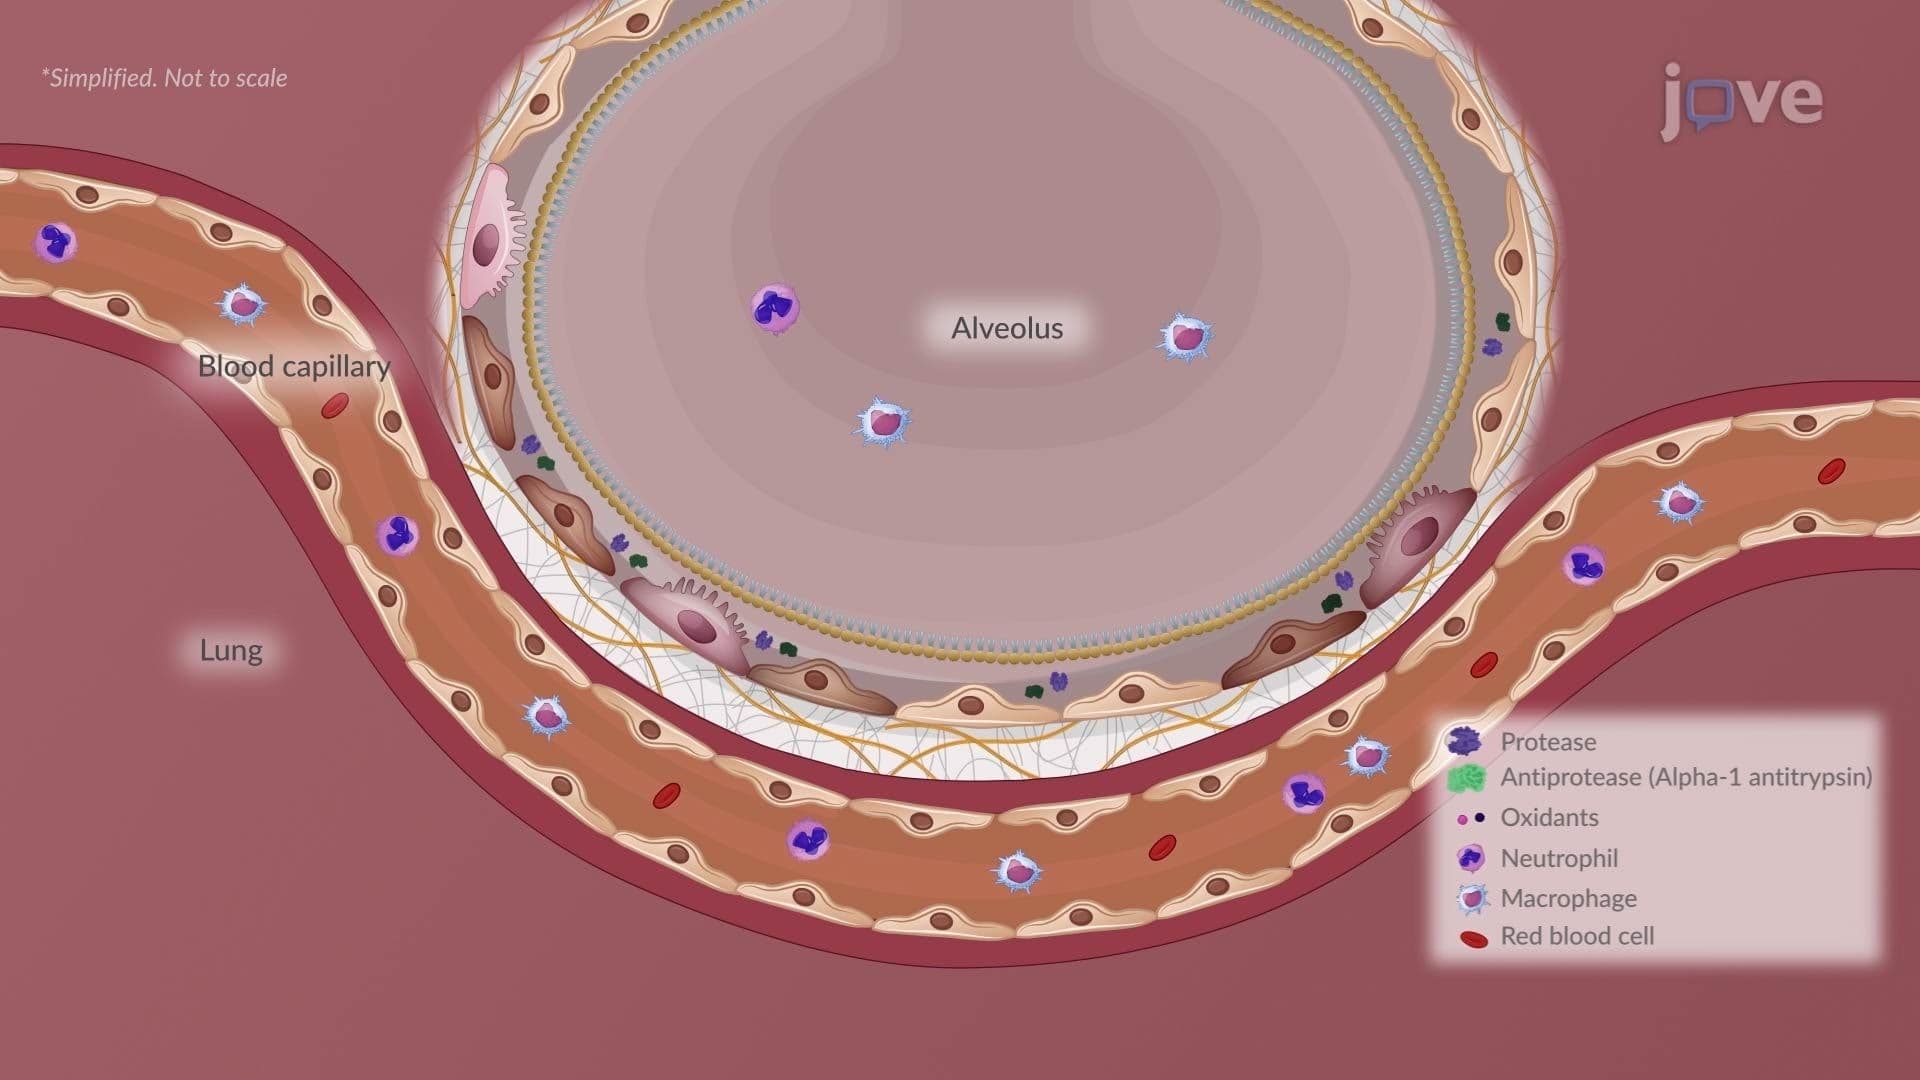
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...