Related Experiment Video
Updated: Jun 23, 2026
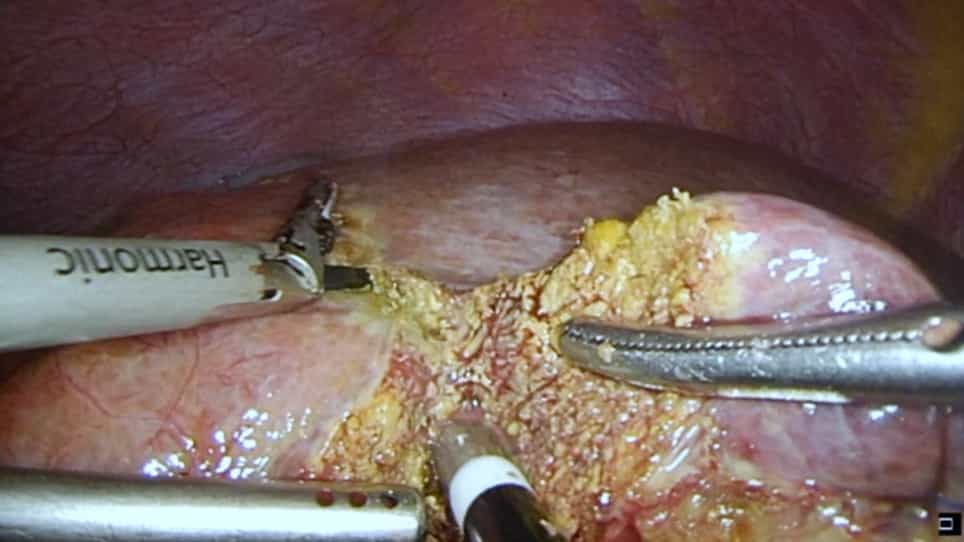
Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Potential Role of Liver Transplantation for Child-Pugh Class A Hepatocellular Carcinoma: Prognosis and Medical
Akihiro Seki1, Tomoyoshi Chiba1, Shintaro Yagi2
1Department of Gastroenterology, Kanazawa University Hospital, Kanazawa, Japan.

Insights
Many patients with Child-Pugh class A (CP-A) hepatocellular carcinoma (HCC) lose eligibility for liver transplantation (LT) before their liver decompensates. This highlights the need to re-evaluate LT criteria for HCC patients.
Area of Science:
- Hepatology
- Transplantation Surgery
- Oncology
Background:
- Liver transplantation (LT) in Japan for hepatocellular carcinoma (HCC) is currently limited to patients with decompensated cirrhosis.
- Child-Pugh class A (CP-A) patients with HCC initially meet Japan's LT criteria but may progress.
- Understanding the clinical course and LT eligibility changes in CP-A HCC is crucial.
Purpose of the Study:
- To investigate the clinical course, prognosis, and medical expenditure of CP-A HCC patients initially meeting LT criteria.
- To assess changes in oncological eligibility for LT during follow-up in this patient group.
- To compare survival and costs between LT recipients and CP-A HCC subgroups.
Main Methods:
- Retrospective analysis of HCC patients (2011-2021) at Kanazawa University Hospital.
- Inclusion of 134 CP-A HCC patients, 45 CP-B HCC patients, and 6 LT recipients (age < 70 years).
- Comparison of survival rates and cumulative HCC-related medical expenditures; definition of a transplantable period.
Main Results:
- LT offered the best prognosis (5-year overall survival: 83.3%).
- CP-A HCC patients progressing beyond criteria showed significantly reduced survival, similar to CP-B disease.
- Of 53 progressing patients, only 22.6% maintained LT eligibility (median 10.6 months); early recurrence and high FIB-4 index predicted poor prognosis.
Conclusions:
- A significant proportion of CP-A HCC patients lose LT eligibility before hepatic decompensation.
- Further research is needed to explore potential LT benefits for selected compensated cirrhosis patients.
- This study informs future discussions on expanding LT indications for HCC.
Aim:
In Japan, liver transplantation (LT) for hepatocellular carcinoma (HCC) is restricted to patients with decompensated cirrhosis. We investigated the clinical course, prognosis, and medical expenditure of patients with Child-Pugh class A (CP-A) HCC initially within the Japan criteria, including changes in oncological eligibility for LT during follow-up.
Methods:
We retrospectively analyzed patients with HCC treated at Kanazawa University Hospital between 2011 and 2021. After applying the age criterion (< 70 years), 134 patients with CP-A HCC, 45 with CP-B HCC, and 6 LT recipients were included. Survival and cumulative HCC-related medical expenditures were compared. A transplantable period was defined as the interval during which both hepatic reserve and tumor burden met LT eligibility.
Results:
LT achieved the most favorable prognosis, with a 5-year overall survival rate of 83.3%. Among patients with CP-A HCC, progression beyond the Japan criteria was associated with markedly reduced survival, approaching that observed in CP-B disease. Of 53 patients who progressed beyond the Japan criteria, only 12 (22.6%) retained a transplantable period (median, 10.6 months). Early recurrence and a FIB-4 index > 5 were independently associated with poor prognosis. The cost per treatment life-year did not differ significantly between LT recipients and certain CP-A HCC subgroups.
Conclusions:
Many patients with CP-A HCC initially within the Japan criteria lost oncological eligibility for LT before hepatic decompensation. Further studies are warranted to determine whether a subset of patients with compensated cirrhosis may benefit from LT and to inform future discussions regarding the potential expansion of LT indications.

