Related Experiment Video
Updated: Jun 23, 2026
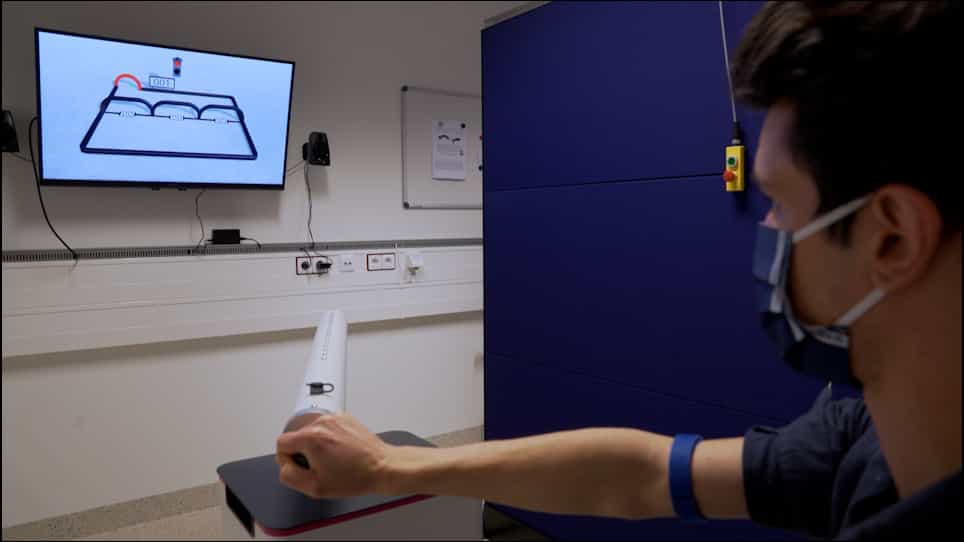
Investigating Pain-Related Avoidance Behavior using a Robotic Arm-Reaching Paradigm
Published on: October 3, 2020
Proposing an explanatory framework based on the fear-avoidance model: a mixed-methods analysis of kinesiophobia in
Li Sun1, Chunlei Nie2, Dandan Xu1
1Department of Cardiology, The First Affiliated Hospital with Nanjing Medical University, Nanjing, China.

Introduction:
Exercise-based cardiac rehabilitation is safe and effective for patients with coronary artery disease, with home-based programs typically delivered through digital platforms (e.g., mobile applications, wearable devices) that enable remote monitoring and personalized guidance. However, home-based rehabilitation, while offering flexibility in time and location, is frequently impeded by kinesiophobia. This study aimed to identify the determinants of kinesiophobia in patients following percutaneous coronary intervention and to examine their interplay in driving maladaptive fear and influencing engagement in rehabilitation.
Methods:
This study adopted a sequential explanatory mixed-methods design. A cross-sectional study was conducted to investigate kinesiophobia among hospitalized patients, followed by semi-structured interviews with patients exhibiting high levels of kinesiophobia selected through purposive sampling from the cross-sectional cohort.
Results:
The quantitative study involved a cross-sectional survey of 220 post-PCI patients, with a mean age of 57.85 ± 12.17 years. The majority were male (n = 170, 77.3%), living with a partner (n = 192, 87.3%), and had comorbid chronic conditions (n = 153, 69.5%). Multiple linear regression analysis revealed that living alone (β = 0.17, 95% CI: 1.53-6.45), urban residence (β = 0.16, 95% CI: 0.16-5.05), previous PCI history (β = 0.11, 95% CI: 0.15-4.21), comorbidities (β = 0.13, 95% CI: 0.41-3.91), clinical symptom severity (β = 0.23, 95% CI: 0.23-0.61), and lower cardiac rehabilitation knowledge scores (β = -0.43, 95% CI: -0.24-0.15) significantly predicted kinesiophobia levels, collectively explaining 46.5% of the variance in Tampa Scale for Kinesiophobia (TSK) scores. Building upon these quantitative findings, 18 participants (7 females, 11 males) with high kinesiophobia scores (TSK > 37) were purposively sampled for the qualitative phase. Fourteen open codes were collapsed into eight focused codes, which subsequently resulted in the following four themes: 1) catastrophic interpretation of somatic Sensations, 2) knowledge deficits and misinformation sustaining Fear, 3) vicious cycle of symptom misinterpretation and knowledge Gaps, and 4) Positive perception.
Conclusion:
Based on integrated findings, this study proposes an explanatory framework derived from the Fear-Avoidance Model, delineating three core pathways: the initial origination of fear through symptom misinterpretation, its subsequent amplification via cognitive and environmental factors, and its eventual consolidation through behavioral reinforcement via avoidance cycles.
Related Concept Videos
 01:09
Preparedness and Phobias
 03:26
Framing Effects
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:25
Models of Health Promotion and Illness Prevention I
The health belief model (HBM) attempts to predict health-related behavior in specific belief patterns. According to the HBM, a person's...
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast, controlled...