Related Experiment Video
Updated: Jun 23, 2026


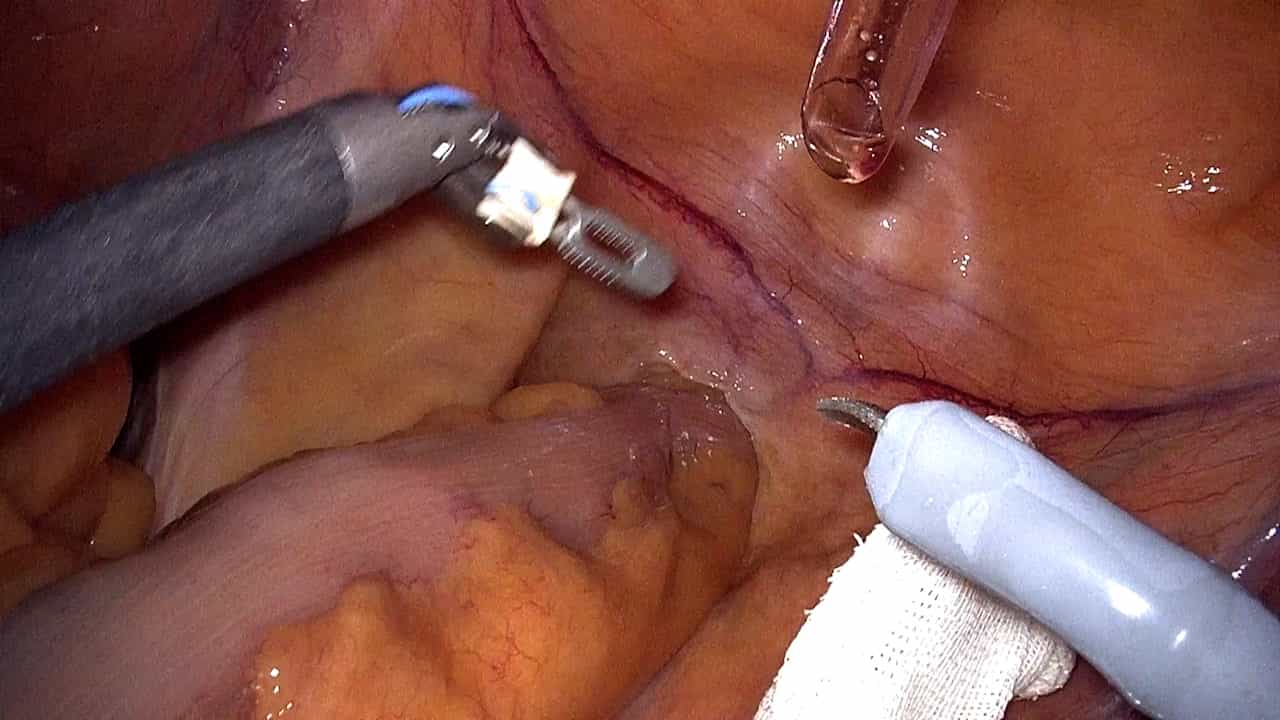
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Optimal surgical timing following neoadjuvant chemoradiotherapy in patients with rectal cancer: a systematic review
Zijie Tao1, Yuhang Jiang2, Qiyi Gui1
1Department of Immunology, Jiangsu Key Laboratory of Laboratory Medicine, Department of Laboratory Medicine, School of Medicine, Jiangsu University Zhenjiang 212013, Jiangsu, China.

Objective:
To determine the optimal surgical interval between neoadjuvant chemoradiotherapy (nCRT) and total mesorectal excision (TME) for patients with locally advanced rectal cancer through a network meta-analysis (NMA). Additionally, a continuous dose-response meta-regression analysis was conducted to explore potential non-linear associations.
Methods:
Electronic databases, including PubMed, Embase, Web of Science, and the Cochrane Library, were systematically searched from inception to July 18, 2024. The methodological quality of the included studies was assessed using the Cochrane Risk of Bias 2.0 (ROB 2.0) tool and the Newcastle-Ottawa Scale (NOS). The NMA was performed under a Bayesian framework, and surgical intervals ranging from <4 weeks to 28 weeks were ranked using the surface under the cumulative ranking curve (SUCRA). The primary endpoint was pathological complete response (pCR), while secondary endpoints included overall survival (OS), disease-free survival (DFS), recurrence rate, and sphincter preservation rate (SPR).
Results:
A total of 12 studies (3 randomized controlled trials and 9 cohort studies) involving 31,783 patients were included. SUCRA rankings indicated that an interval of 8-12 weeks was most effective for achieving pCR, prolonging DFS, and reducing recurrence rate. Conversely, a 6-8 week interval was most favorable for improving OS and SPR. Both very short (<4 weeks) and very long (>24 weeks) intervals ranked lower across most clinical outcomes. Dose-response analysis revealed a significant inverted U-shaped association for pCR, mathematically peaking at approximately 12.7 weeks, whereas DFS showed a peak at around 5.9 weeks.
Conclusion:
Current evidence suggests that an interval of 8-12 week is most strongly associated with improved pCR and prolonged DFS, whereas a 6-8 week interval shows the highest probability of improving OS and SPR. Clinical decision-making should balance oncologic and functional outcomes based on individualized assessments.