Biportal endoscopic spinal surgery for thoracic ossification of the ligamentum flavum: a study of different classification types and surgical outcomes
Related Experiment Video
Updated: Jun 23, 2026
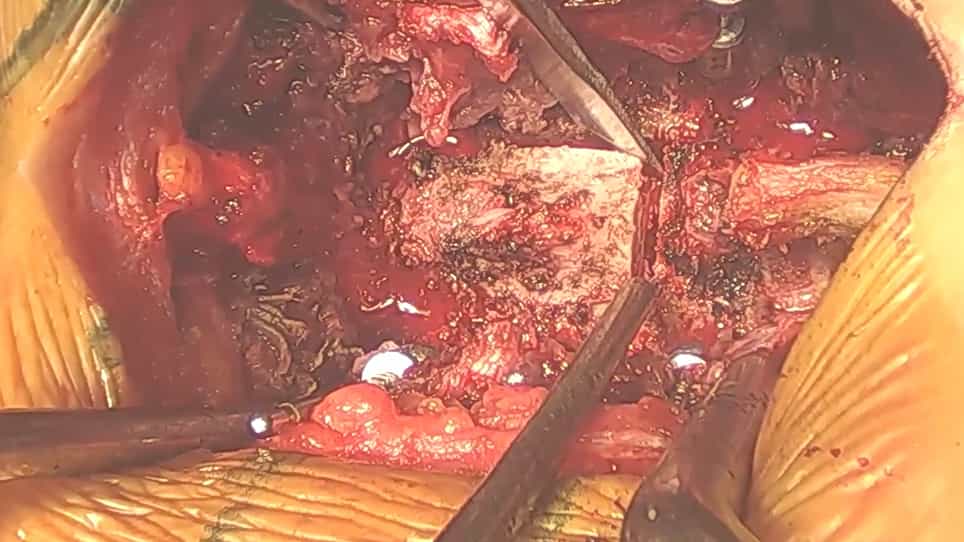
Laminectomy for the Removal of Thoracic Ossification of the Ligamentum Flavum (TOLF) Using Ultrasonic and Conventional Osteotomes
Published on: April 21, 2023
Honggang Wang1,2, Dongqing He1,2, Ruxing Liu1,2
1Department of Orthopedics, Second Hospital of Shanxi Medical University, Taiyuan, China.

Background:
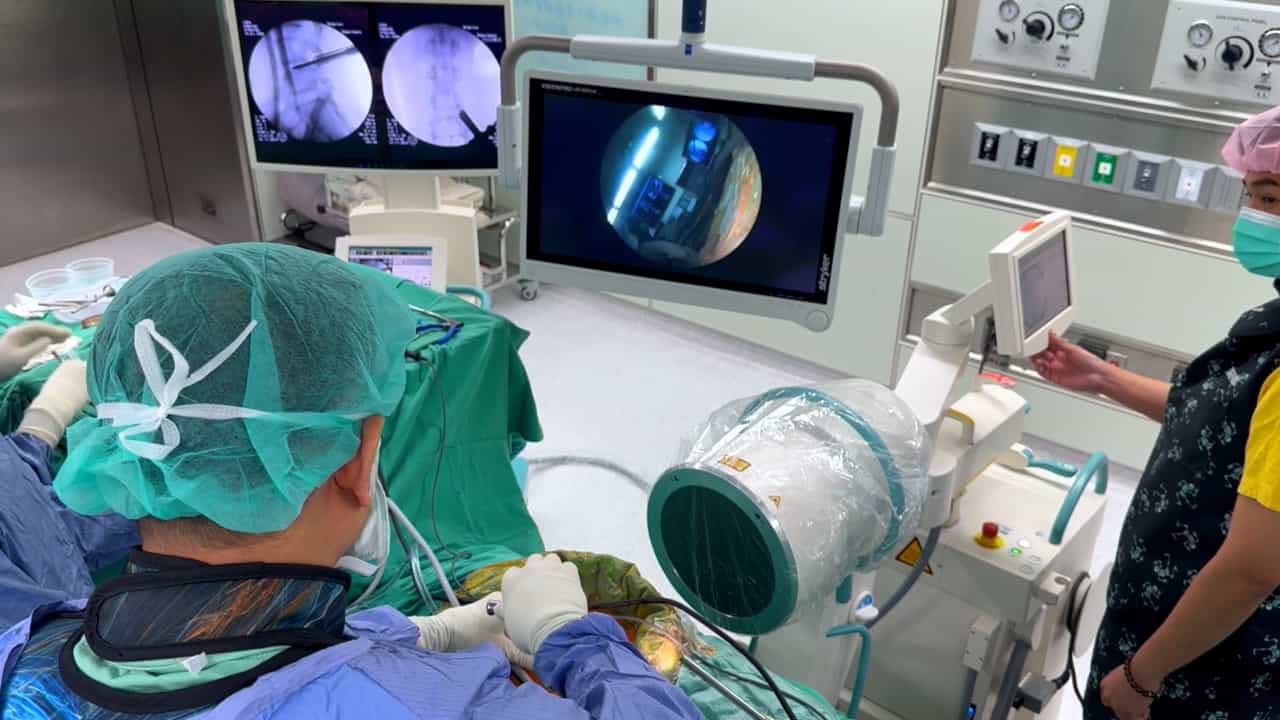
This study aimed to assess potential differences in the clinical effectiveness of biportal endoscopic spinal surgery (BESS) for treating various axial classifications of ossification of the ligamentum flavum (OLF).
Methods:
We retrospectively reviewed patients with thoracic OLF who underwent BESS between January 2023 and June 2024. The OLF type was classified based on preoperative computed tomography (CT) scans, and patients were divided into two groups: non-fused and fused. To evaluate primary radiographic outcomes, we measured changes in the cross-sectional area (CSA) and anteroposterior diameter (APD) on both preoperative and postoperative magnetic resonance imaging (MRI) scans. Clinical outcomes were assessed using the Visual Analog Scale (VAS), the modified Japanese Orthopedic Association (mJOA) score, and the MacNab criteria.
Results:
This study included 37 patients: 19 in the non-fused group and 18 in the fused group. Both groups showed significant improvements in VAS and mJOA scores from preoperative baseline values (p < 0.05). No significant differences in recovery rate were observed between the two groups at any postoperative time point (p > 0.05). The increase in APD was significantly greater in the fused group than in the non-fused group (p < 0.05), whereas the increase in CSA was similar between the two groups (p > 0.05). The fused group had longer operative times and a higher incidence of complications than the non-fused group.
Conclusion:
BESS produces comparable short-term clinical outcomes for fused and non-fused thoracic OLF; however, complex cases require careful patient evaluation and may be best managed by experienced endoscopic surgeons.