
Incidence and disease burden of bronchiectasis in systemic lupus erythematosus: a nationwide population-based study
Geonhui Min1, Dong Eun Kye2, Heajung Lee3
1Department of Biochemistry, Chungbuk National University College of Medicine, Chungbuk National University, Cheongju-si, The Republic of Korea.

Objectives:
Pulmonary abnormalities, such as interstitial lung disease, have been relatively well studied in patients with systemic lupus erythematosus (SLE). However, it remains unclear whether the risk of bronchiectasis and its associated disease burden are increased in SLE.
Methods:
Using the Korean National Health Insurance Service dataset, we conducted a population-based matched cohort study involving adults aged ≥20 years diagnosed with SLE (SLE cohort) between 2002 and 2012 and a 1:4 age, sex and health insurance service-matched cohort (matched controls). Beginning 1 year after enrolment, participants were followed until the date of a bronchiectasis diagnosis, death or 31 December 2019, whichever came first.
Results:
During a median follow-up of 12.8 years (IQR 10.0-16.0 years), the incidence rate of bronchiectasis was higher in the SLE cohort than in the matched controls (374.8 vs 236.2/100 000 person-years, p<0.001). The SLE cohort showed a 1.46-fold (95% CI 1.22 to 1.76) increased risk of developing bronchiectasis compared with the matched cohort. Within the SLE cohort, age older than 40 years (highest adjusted HR (aHR) in those ≥70 years 25.08, 95% CI 7.62 to 82.53) and asthma (aHR 1.73, 95% CI 1.11 to 2.70) were associated with an increased risk of bronchiectasis. In contrast, obesity was inversely associated with the risk of bronchiectasis (aHR 0.56, 95% CI 0.38 to 0.82). Individuals with SLE who developed bronchiectasis had significantly higher rates of mortality, emergency department visits and hospitalisations than those who did not develop bronchiectasis.
Conclusions:
The risk of bronchiectasis was higher in individuals with SLE than in controls, and its development was associated with a worse disease course, higher mortality during follow-up and increased healthcare utilisation.

Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:23
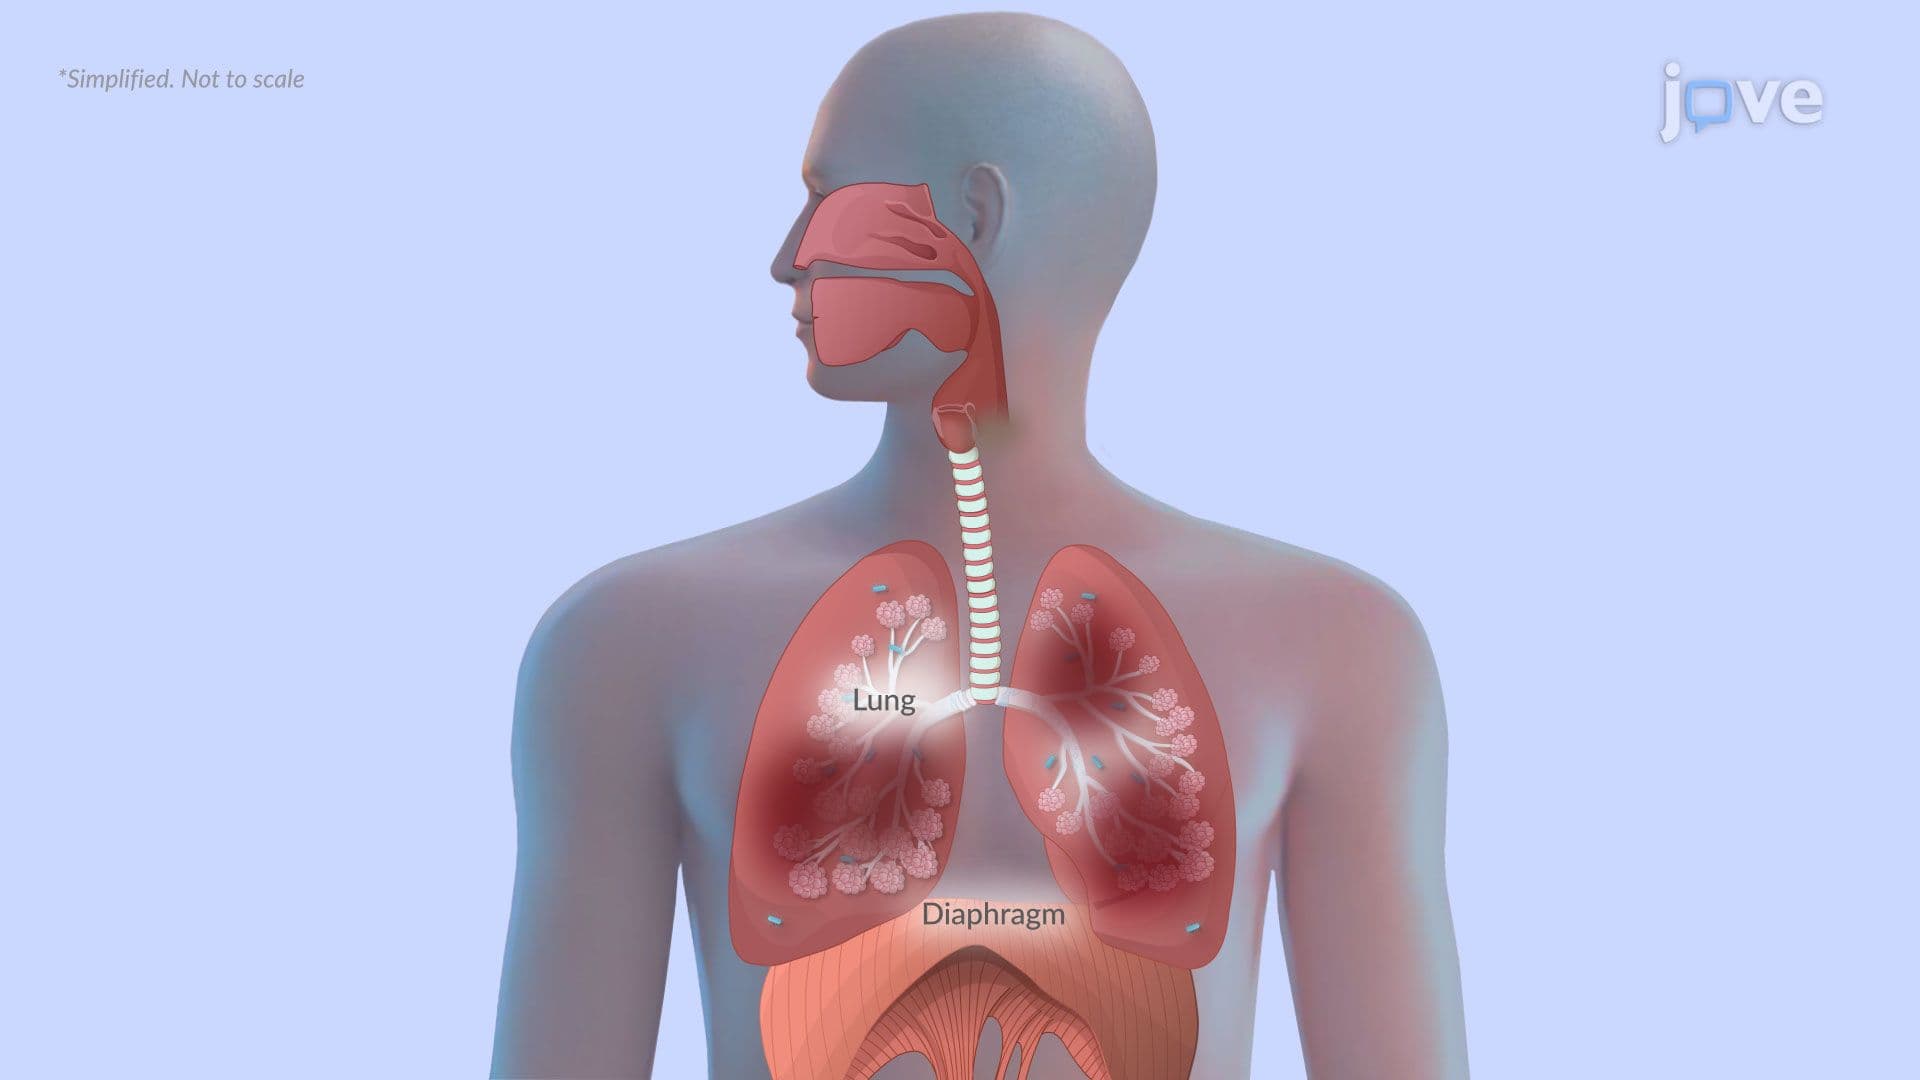
Chronic Obstructive Pulmonary Disease I: Introduction
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...