Related Experiment Video
Updated: Jun 25, 2026
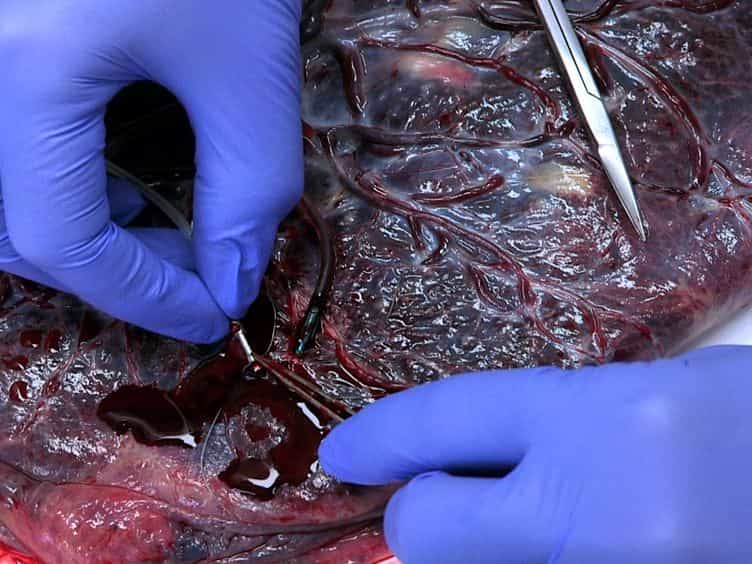
Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Transplacental transfer of osimertinib and alectinib using an ex vivo human placental perfusion model
Laure Benoit1, David Combarel2, Marie-Noëlle Dieudonne3
1Centre Hospitalier Intercommunal de Poissy Saint-Germain-en-Laye, Department of Gynecology and Obstetrics, Poissy, France; Université Paris-Saclay, UMR 1198, INRAE, BREED, RHuMA, Jouy-en-Josas, France.

Background:
The incidence of non-small cell lung cancer (NSCLC) is increasing in women, including those of childbearing age. While recent drugs such as osimertinib and alectinib have improved the prognosis of specific molecular subtypes (e.g., EGFR-mutant and ALK-rearranged NSCLC), their potential use during pregnancy remains inadequately supported by pharmacological data.
Objective:
To assess the transplacental transfer and placental cotyledon accumulation of osimertinib and alectinib, using a human ex vivo placental perfusion model.
Study Design:
Term placentas from normal pregnancies were collected after delivery and perfused with osimertinib or alectinib (in combination with alectinib major active metabolite M4) doses simulating steady state plasma concentrations observed in maternal plasma. Fetal transfer rate, clearance index, and cotyledon accumulation were evaluated, with antipyrine used as a control marker. Samples were collected during a 90-min procedure.
Results:
Significant transplacental transfer of osimertinib was observed, with a fetal transfer rate of 9.5% and a CI of 0.41, and cotyledon accumulation of 28.9%. In contrast, neither alectinib nor M4 were detected in fetal samples, although both were found to accumulate substantially in placental tissues (370.7% and 178.3%, respectively).
Conclusion:
These findings suggest that osimertinib crosses the placenta with a moderate tissue uptake, while alectinib and its metabolite M4 do not appear to be transferred to the fetus but accumulate significantly within the placental tissue. Further studies are needed to guide treatment selection for NSCLC in pregnant women.

