Related Experiment Video
Updated: Jun 25, 2026
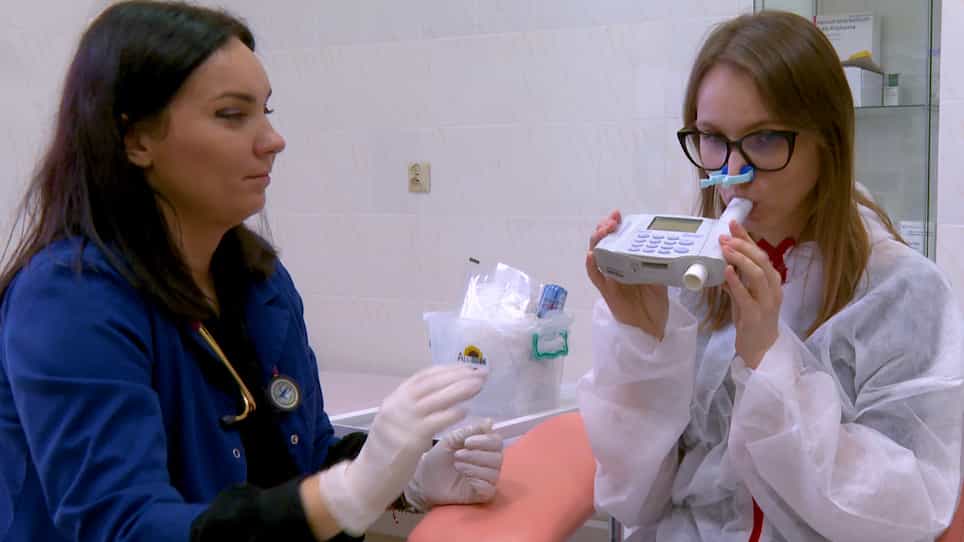
Symptom Assessment of Patients with Allergic Rhinitis Using an Allergen Exposure Chamber
Published on: March 3, 2023
Allergy burden score and lung function impairment in children with asthma: a dose-response cross-sectional study
Junlin Zhao1, Zhiyuan Wang1, Yanan Wang1
1Department of Pediatrics, The First Affiliated Hospital of Xinjiang Medical University, No. 137 Liyushan Road, Xinshi District, Urumqi, 830054, Xinjiang, China.

Insights
Children with asthma and a higher allergy burden score (ABS) show reduced lung function. This allergy burden score may help identify children with asthma needing closer monitoring for lung impairment.
Area of Science:
- Pediatric Allergy and Immunology
- Respiratory Medicine
- Clinical Pediatrics
Background:
- Allergic comorbidities are common in children with asthma, often linked to poorer health outcomes.
- The precise relationship between the total burden of allergies and lung function in pediatric asthma patients remains unclear.
Purpose of the Study:
- To investigate the dose-response association between cumulative allergic burden and lung function in children with asthma.
- To evaluate the role of type 2 inflammatory markers in this relationship.
Main Methods:
- Retrospective cross-sectional study of 264 treatment-naive children with asthma (ages 4-16).
- Developed an Allergy Burden Score (ABS) based on allergic rhinitis, atopic dermatitis, food/drug allergies, and family history.
- Utilized multivariable regression, restricted cubic splines, and logistic regression to analyze ABS and lung function (FEV1% predicted).
Main Results:
- Each 1-point increase in ABS correlated with a 3.03% decrease in FEV1% predicted (P < 0.001).
- A nonlinear relationship was observed, with accelerated lung function decline at ABS ≥ 3.
- Type 2 inflammatory markers explained only 2.7% of the association, indicating other contributing factors.
Conclusions:
- A significant dose-response link exists between cumulative allergic burden and impaired lung function in pediatric asthma.
- Mechanisms beyond peripheral type 2 inflammation likely contribute to this association.
- The ABS shows potential as a clinical tool for identifying children with asthma at higher risk for lung function deficits.
Abstract:
Children with asthma commonly present with multiple allergic comorbidities; however, the quantitative dose-response relationship between cumulative allergic burden and lung function has not been established in pediatric populations. This retrospective cross-sectional study included 264 treatment-naive children with asthma aged 4-16 years. An allergy burden score (ABS) was constructed using a cumulative disease count strategy incorporating allergic rhinitis, atopic dermatitis, food allergy, drug allergy, and family history of allergic disease. Multivariable linear regression and restricted cubic spline (RCS) analyses assessed dose-response relationships between ABS and FEV1% predicted. Bootstrap-based statistical decomposition examined the contribution of type 2 inflammatory markers, and logistic regression assessed the odds of lung function abnormality. In the fully adjusted model, each 1-point increase in ABS was associated with a 3.03% decrease in FEV1% predicted (95% CI: - 3.77 to - 2.29; P < 0.001). RCS analysis indicated significant nonlinearity (P for nonlinearity < 0.001), with accelerated decrease at ABS ≥ 3. Type 2 inflammatory markers accounted for only 2.7% of the statistically decomposed total association. Each 1-point increase in ABS was associated with 43% higher odds of lung function abnormality (adjusted OR = 1.43, 95% CI: 1.07-1.94).
Conclusion:
A dose-response association exists between cumulative allergic comorbidity burden and lung function impairment in treatment-naive children with asthma. Peripheral type 2 inflammatory markers explain only a small proportion of this association, suggesting additional contributing mechanisms. The ABS may warrant further evaluation as a simple clinical indicator for identifying children with greater lung function impairment, pending prospective multicenter validation.
Trial Registration:
Not applicable. As a retrospective cross-sectional study, this research analyzed existing medical records without prospective assignment of interventions by the research team, and therefore does not meet the WHO criteria for clinical trial registration.
What Is Known:
• Allergic comorbidities are prevalent in children with asthma and associated with worse clinical outcomes. The quantitative dose-response relationship between cumulative allergic burden and lung function has not been established in pediatric populations.
What Is New:
• Each 1-point increase in the Allergy Burden Score (ABS) was associated with a 3.03% decrease in FEV1% predicted, with a nonlinear threshold effect at ABS ≥ 3. Type 2 inflammatory markers collectively accounted for only 2.7% of the total association, suggesting that mechanisms beyond peripheral type 2 inflammation may be involved.

Related Concept Videos
 01:28
Asthma I: Introduction
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma
 01:29
Asthma-I: Introduction
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:13
Asthma III: Clinical Manifestations