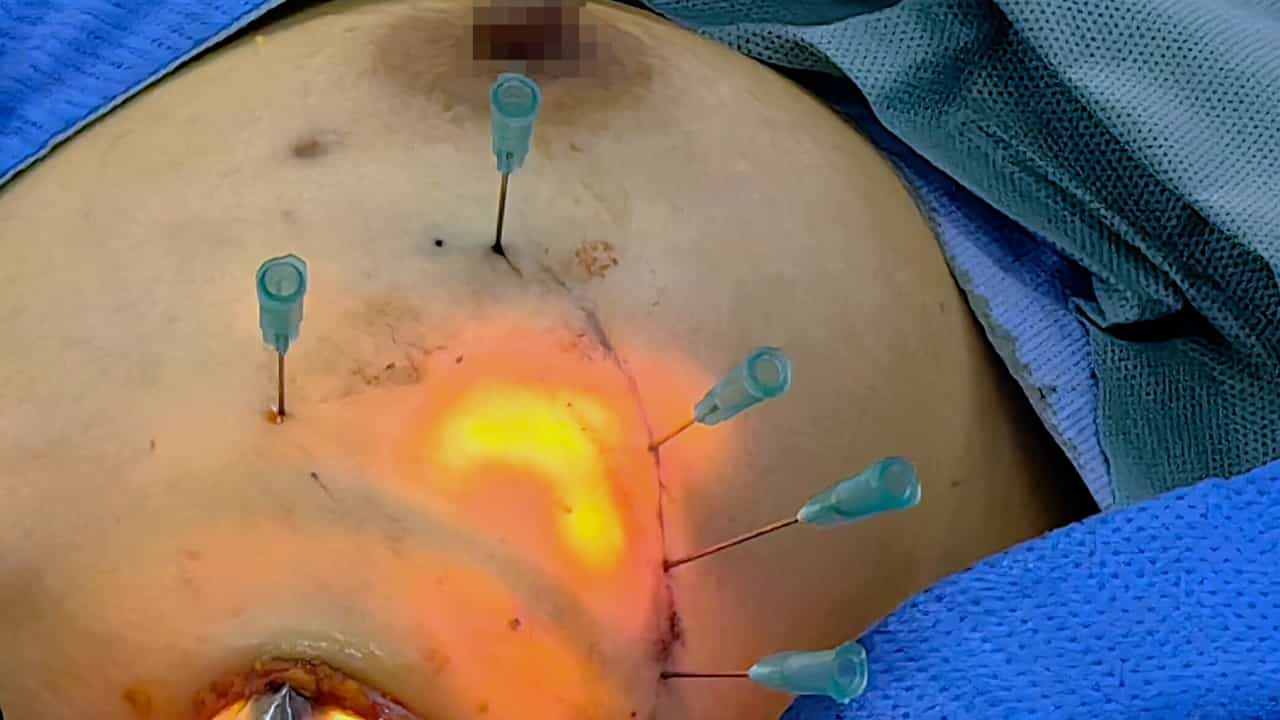
Related Experiment Video
Updated: Jun 25, 2026

Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Robotic-assisted versus conventional nipple-sparing mastectomy with immediate implant-based breast reconstruction: a
Wajahat Mirza1, Hania Iqbal2, Mehak Ejaz Khan2
1Shifa College of Medicine, Shifa Tameer-e-Millat University, Sector H-8/4, Islamabad, Pakistan. wajahatmirza.clinicalresearch@gmail.com.

Background:
Robotic nipple-sparing mastectomy with immediate implant-based reconstruction is increasingly adopted to improve cosmetic outcomes and patient experience; however, its comparative perioperative value against conventional or open nipple-sparing mastectomy remains uncertain when restricted to prospective evidence.
Methods:
We performed a PRISMA-aligned systematic review and random-effects meta-analysis of prospective comparative studies and randomized trials comparing robotic versus conventional or open nipple-sparing mastectomy with immediate implant-based reconstruction. The primary outcome was the total operative time, and the secondary outcomes were major complications, nipple-areolar complex ischemia or necrosis, and length of hospital stay. The risk of bias was assessed using RoB 2 for randomized data and ROBINS-I for nonrandomized data. Leave-one-out sensitivity analyses were conducted for outcomes with substantial heterogeneity, and the certainty of the evidence was graded using GRADE.
Results:
Three prospective studies were included. Robotic surgery was associated with a significantly longer total operative time (mean difference 64.01 min, 95% confidence interval 8.54-119.47). Major complications did not differ between the approaches (risk ratio 0.63, 95% confidence interval 0.27-1.47), nor did nipple areolar complex ischemia or necrosis (risk ratio 0.56, 95% confidence interval 0.28-1.11) or length of hospital stay (mean difference 0.22 days, 95% confidence interval - 0.26 to 0.70). Heterogeneity was high for operative time and moderate to substantial for length of stay. The certainty of the evidence was low overall, driven by imprecision, heterogeneity, and limitations of the non-randomized design.
Conclusions:
Robotic nipple-sparing mastectomy is associated with a longer operative time than conventional or open approaches. No statistically significant differences were observed in major complications or nipple-areolar complex viability; however, the current prospective evidence base is limited, heterogeneous, and imprecise, and clinically important differences cannot be excluded. In experienced centers, robotic nipple-sparing mastectomy may be considered for carefully selected patients who prioritize scar concealment and minimally invasive access; however, its broader role in routine practice remains uncertain pending stronger prospective data on safety, patient-reported outcomes, and resource use.