Related Experiment Video
Updated: Jun 25, 2026

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Lumbar degenerative disease: association of serum complement levels with diagnosis, structural severity, and
Zaiyin Deng1,2, Xiaoxuan Zhu1,2, Yiqiu Cao1,2
1Division of Spine, Department of Orthopedics, Tongji Hospital affiliated to Tongji University, School of Medicine, Tongji University, Shanghai, China.

Purpose:
The clinical evaluation of lumbar degenerative disease (LDD) severity relies on symptoms and imaging, lacking biologically specific diagnostic markers. This study investigated the role of serum complements in LDD to assess their potential as diagnostic biomarkers, their correlation with anatomical stenosis, and their ability to predict postoperative recovery. We hypothesized that specific serum complement levels correlate with both structural severity and clinical outcomes.
Methods:
A prospective investigation was conducted on 82 patients with LDD and 90 healthy controls. To minimize selection bias, a 1:1 propensity score matching (PSM) was performed for age and gender, resulting in a matched cohort of 112 participants. Serum levels of C1q, C3, and C4 were compared, while CRP and ESR were screened to exclude systemic inflammation. Anatomical severity was quantified using the S1/S0 ratio (dural sac area ratio) on MRI. Pain intensity was evaluated via Visual Analogue Scale (VAS) scores; quality of life was appraised using ODI and Barthel scales. Surgical prognosis was defined by achieving the Minimal Clinically Important Difference (MCID, ΔVAS ≥ 1.6) at 2-month follow-up.
Results:
Serum C1q levels were significantly higher in the LDD group compared to controls (184.62 vs. 156.51 g/L, P = 0.001), whereas C3 and C4 showed no significant difference. Baseline CRP and ESR levels were within normal ranges, confirming the specificity of complement activation. ROC analysis demonstrated that C1q effectively distinguished LDD patients (AUC = 0.688), with an optimal cut-off of 154.40 g/L. Serum C4 levels exhibited a significant inverse correlation with the S1/S0 ratio (β = -0.867, P = 0.004). Baseline C1q was an independent predictor of failing to achieve MCID (OR = 0.980, P = 0.010). Patients who did not attain MCID had significantly higher baseline C1q levels. The rate of achieving MCID was lower in the highest C1q quartile (Q4: 52.6%) compared to the lowest (Q1: 75.0%).
Conclusion:
Serum C1q and C4 serve as dual biomarkers in LDD. C4 correlates with anatomical stenosis severity, while C1q predicts surgical prognosis. Integration of serum complement profiling and radiological imaging improves preoperative risk stratification and facilitates surgical decision-making.
Related Concept Videos
 01:27
Degenerative Disc Disease I: Introduction
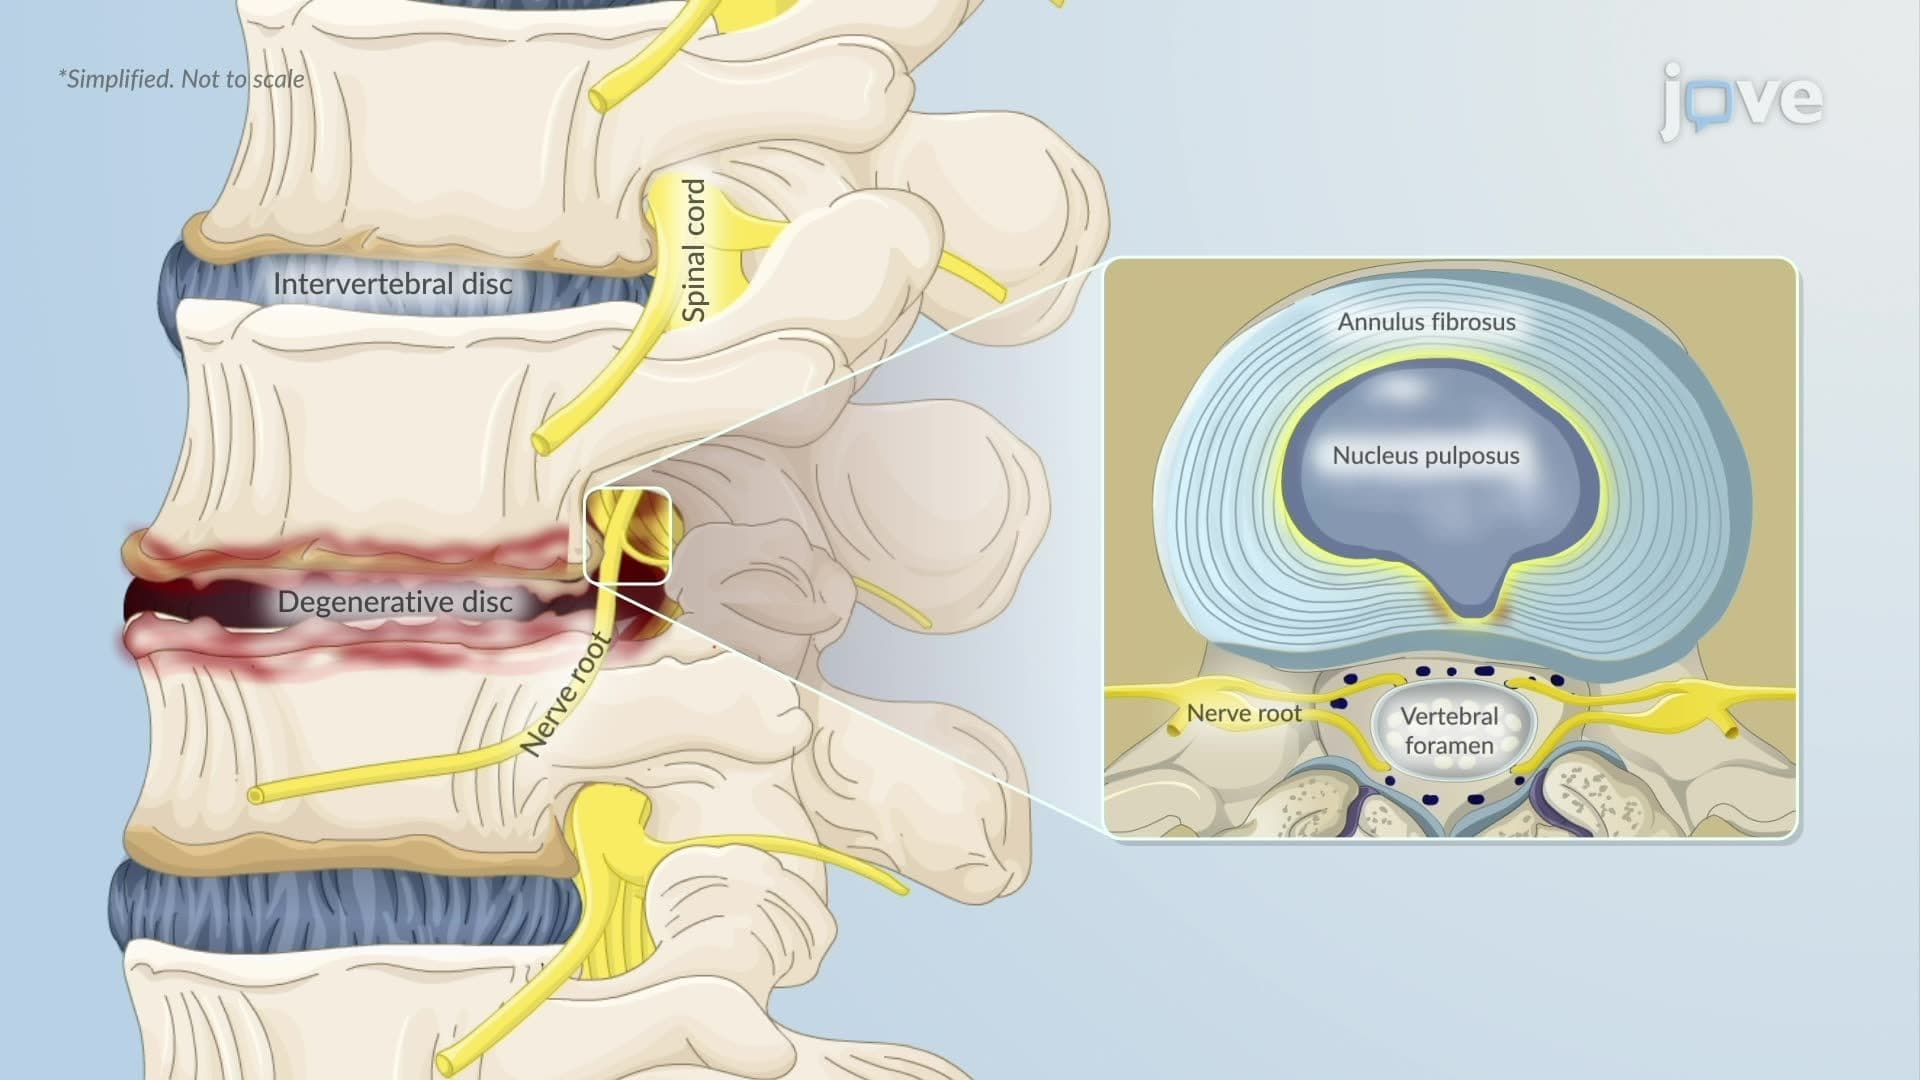 01:23
Degenerative Disc Disease ll: Pathophysiology