Related Experiment Video
Updated: Jun 26, 2026
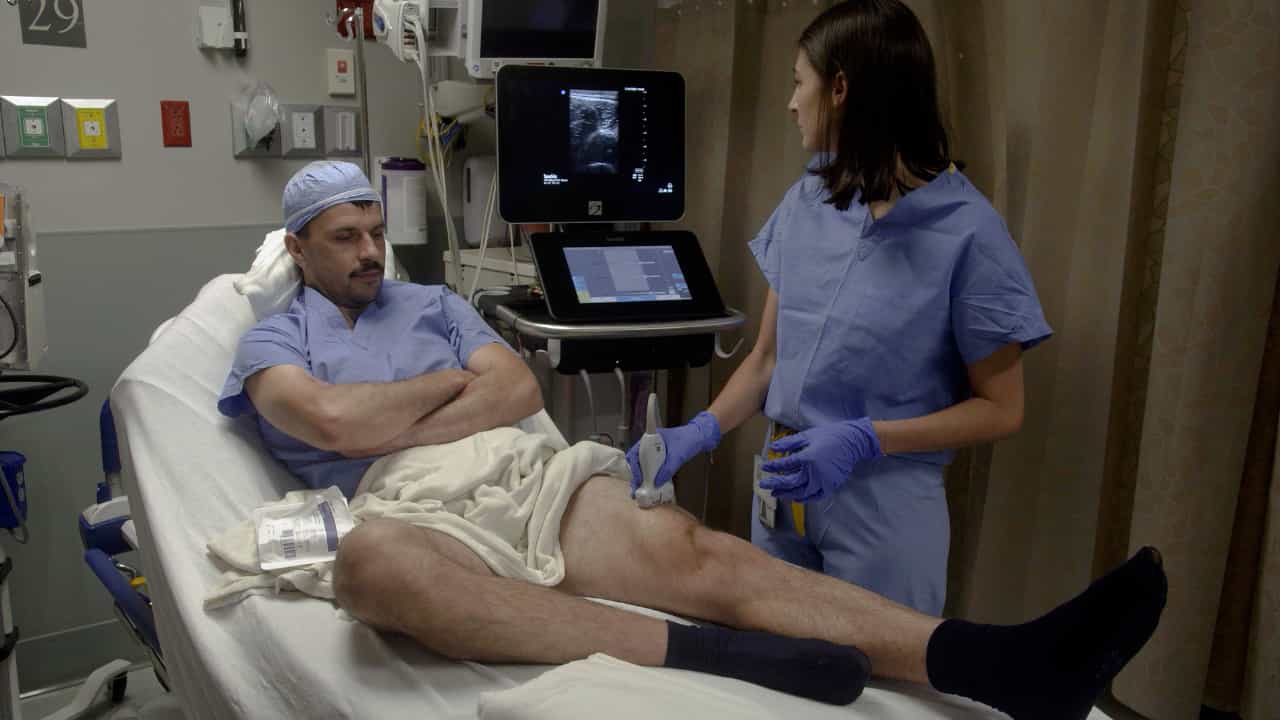

Identifying Frailty Using Point-of-Care Ultrasonography: Image Acquisition and Assessment
Published on: July 26, 2024
Risk Stratification in Periprosthetic Hip Fracture Surgery: The Risk Analysis Index Is Superior to the Five-Item
Nick Jowkar1, Maxwell Ruffner2, Victor Koltenyuk2
1The Robert Larner, MD College of Medicine at the University of Vermont, Burlington, Vermont; REAM Orthopedics, Columbus, Ohio.

Background:
Periprosthetic femoral fractures account for up to 16% of all revision total hip arthroplasties with one- and two-year mortality rates of 23.4 and 29.2%, respectively. Given the substantial clinical and financial burden, accurate preoperative risk assessment is essential. This study evaluated the predictive performance of the Five-Item Modified Frailty Index (mFI-5) and Risk Analysis Index (RAI) in patients undergoing surgery for PFs, aiming to improve preoperative assessment, inform surgical decision-making, and facilitate postoperative planning.
Methods:
A total of 824 patients at least 18 years old who underwent revision total hip arthroplasty and/or open reduction internal fixation for periprosthetic femoral fractures were identified in a national surgical database. The RAI and mFI-5 were calculated for each patient. Outcomes were major and minor complications, readmission, reoperation, nonhome discharge, wound complications, venous thromboembolisms, and mortalities. Multivariable logistic regression models for each index-outcome were fitted, controlling for body mass index, operative time, procedure type, and smoking status. The ability of RAI and mFI-5 to predict postoperative outcomes was assessed using the area under the receiver operating curve (AUC) with DeLong's test used to compare differences between correlated AUCs.
Results:
The RAI demonstrated significantly better predictive ability for mortality (AUC: 0.69 versus 0.53; P = 0.033) and nonhome discharge (AUC: 0.71 versus 0.57; P < 0.001) compared with mFI-5. In adjusted models, RAI was significantly associated with mortality (odds ratio: 1.08; 95% confidence interval: 1.00 to 1.17; P = 0.040) and nonhome discharge (odds ratio: 1.16; 95% confidence interval: 1.12 to 1.20; P < 0.001).
Conclusions:
The RAI was superior to the mFI-5 in predicting mortality and nonhome discharge for patients undergoing surgical management of PPFs. Our findings support the implementation of RAI as a tool for preoperative risk stratification and may be impactful in surgical planning and counseling of geriatric orthopaedic patients and their families.
