Related Experiment Video
Updated: Jun 26, 2026
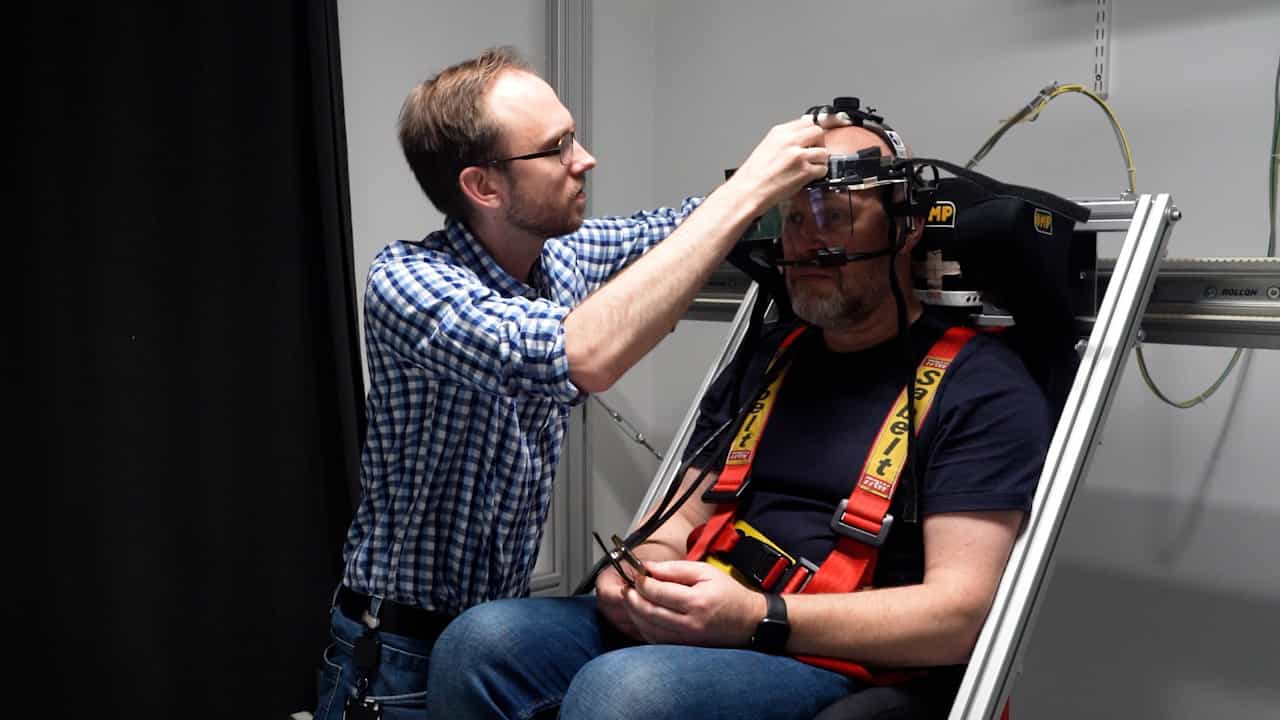
Using Eye-tracking to Assess the Relative Importance of Visual and Vestibular Input to Subcortical Motion Processing in the Roll Plane
Published on: August 22, 2025
Meta-analysis of the therapeutic effects of traumatic BPPV and idiopathic BPPV
1Department of Otolaryngology Head and Neck Surgery, Hainan General Hospital, Hainan Affiliated Hospital of Hainan Medical University, Xiuying, Haikou, China.

Objective:
To systematically evaluate differences in treatment efficacy and prognosis between traumatic benign paroxysmal positional vertigo (t-BPPV) and idiopathic BPPV (i-BPPV), and to provide evidence-based guidance for clinical practice.
Methods:
We systematically searched 8 databases (PubMed, EMBASE, Cochrane Library, Web of Science, CBMdisc, Wanfang, CNKI, and VIP) for cohort studies comparing t-BPPV and i-BPPV, with the search period extending until September 2023. Two independent reviewers screened literature, extracted data, and assessed methodological quality using the Newcastle-Ottawa Scale (NOS). Meta-analyses were performed using RevMan 5.3 and Stata 12.0. Risk ratios (RR) with 95% confidence intervals (CI) were calculated for dichotomous outcomes. Heterogeneity was evaluated via p-values and I2statistics, with fixed-effects models applied for I2 ≤ 50% and random-effects models otherwise.
Results:
Seven high-quality cohort studies (NOS ≥ 6) involving 4,074 patients were included. Compared with i-BPPV, t-BPPV demonstrated significantly poorer outcomes across all metrics: higher recurrence rate (RR = 3.39, 95%CI 3.07-3.74, p < 0.00001), greater repositioning difficulty (RR = 3.05, 95%CI 2.74-3.40, p < 0.00001), lower treatment efficacy (RR = 0.87, 95%CI 0.84-0.90, p < 0.00001), higher proportion of multi-semicircular canal involvement (RR = 2.91, 95%CI 1.55-5.47, p = 0.0009), and elevated bilateral BPPV incidence (RR = 3.37, 95%CI 1.86-6.10, p < 0.00001). Egger's test revealed no significant publication bias for any outcome (p > 0.05).
Conclusion:
t-BPPV exhibits inferior repositioning efficacy, higher risks of residual symptoms and recurrence, and increased rates of multi-semicircular canal and bilateral involvement compared with i-BPPV. Clinicians should adopt tailored management strategies for t-BPPV, emphasizing long-term follow-up and personalized interventions.

