Related Experiment Video
Updated: Jun 26, 2026
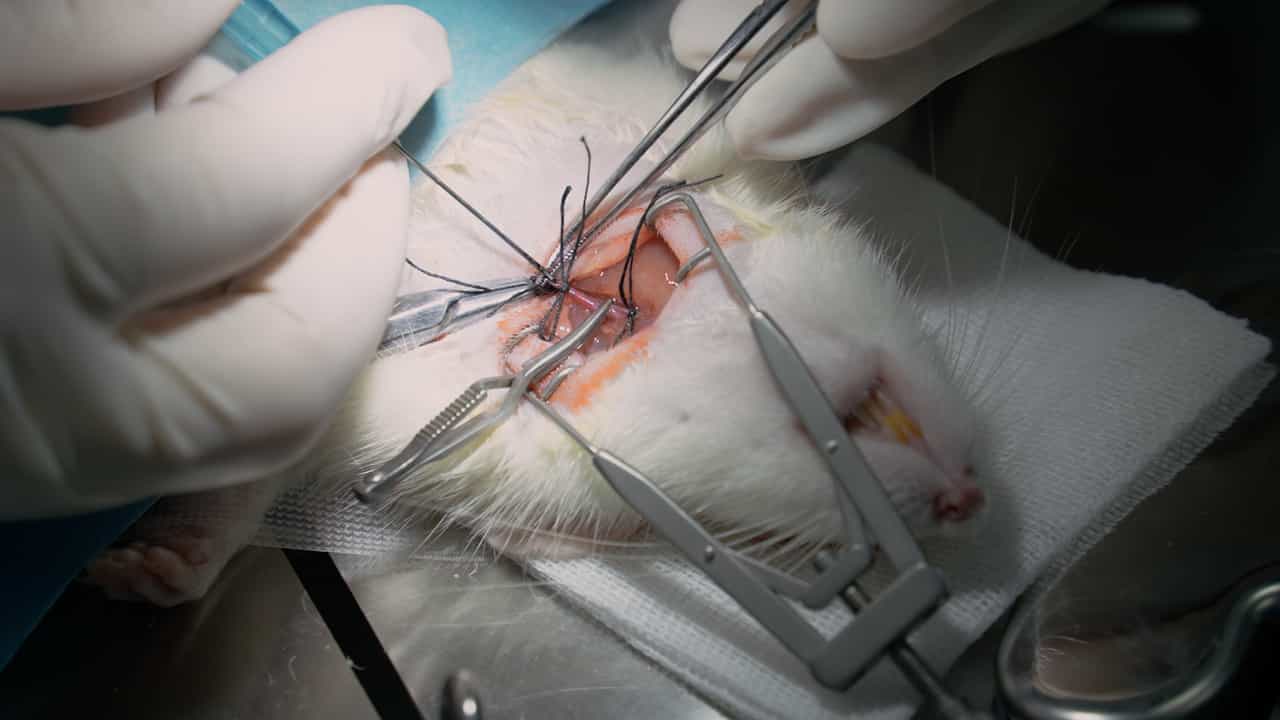

A Modified Model Preparation for Middle Cerebral Artery Occlusion Reperfusion
Published on: May 31, 2024
Predictors of Futile Recanalization after Mechanical Thrombectomy for Middle Cerebral Artery M2 Occlusion
Yuki Nakamura1, Rintaro Yokoyama2, Takehiro Saga2
1Department of Neurology, Hakodate Shintoshi Hospital, Hakodate, Hokkaido, Japan.

Objective:
Futile recanalization (FR) is defined as a poor functional outcome despite successful reperfusion after mechanical thrombectomy (MT) and remains a clinical concern in acute ischemic stroke. This study investigated clinical predictors of FR in patients with middle cerebral artery (MCA) M2 occlusion.
Methods:
This single-center retrospective study included consecutive patients with acute cardioembolic stroke due to MCA M2 occlusion who underwent MT between April 2021 and December 2025. We included patients with successful reperfusion (modified Thrombolysis in Cerebral Infarction score ≥2b), and a pre-stroke modified Rankin Scale (mRS) score of 0-2. FR was defined as mRS 3-6 at discharge. We compared clinical, procedural, and outcome variables between patients with FR and those with effective recanalization (mRS 0-2). Multivariable logistic regression analysis adjusted for age and sex was performed to identify independent predictors of FR. A potential cutoff for receiver-operating characteristic (ROC) analysis was determined using the Youden index.
Results:
Participants comprised 30 patients (median age, 79 years; 56.7% men), with FR identified in 13 patients (43.3%). Patients in the FR group showed a higher baseline National Institutes of Health Stroke Scale (NIHSS) score than those in the effective recanalization group (median 19 vs. 10; p <0.01). In multivariable analysis, the NIHSS score was independently associated with FR (odds ratio, 1.18; 95% confidence interval, 1.01-1.39; p = 0.044). ROC analysis showed an area under the curve of 0.76, and an NIHSS score of 11 was identified as a potential cutoff for predicting FR. Procedural variables, including puncture-to-recanalization time, did not remain significant after adjustment. No significant differences in anatomical characteristics of M2 occlusion were observed between groups.
Conclusion:
A higher baseline NIHSS score may be associated with FR after MT in patients with MCA M2 occlusion. An NIHSS score of 11 may serve as a practical reference for risk stratification, although these findings should be considered exploratory. Baseline neurological severity may have a greater influence on clinical outcome than procedural factors after successful recanalization.
Insights
Futile recanalization (FR) after mechanical thrombectomy (MT) for middle cerebral artery M2 occlusion is linked to higher baseline National Institutes of Health Stroke Scale (NIHSS) scores. An NIHSS score of 11 may help predict this poor outcome.
Area of Science:
- Neurology
- Interventional Neurology
- Stroke Medicine
Background:
- Futile recanalization (FR), a poor outcome despite successful reperfusion after mechanical thrombectomy (MT), is a significant concern in acute ischemic stroke management.
- Identifying predictors of FR is crucial for optimizing treatment strategies and patient outcomes in stroke care.
Purpose of the Study:
- To investigate clinical predictors of futile recanalization (FR) in patients with acute ischemic stroke due to middle cerebral artery (MCA) M2 occlusion undergoing mechanical thrombectomy (MT).
Main Methods:
- A single-center retrospective study included patients with acute cardioembolic stroke and MCA M2 occlusion who underwent MT with successful reperfusion.
- Futile recanalization was defined as a modified Rankin Scale (mRS) score of 3-6 at discharge, compared to effective recanalization (mRS 0-2).
- Multivariable logistic regression and receiver-operating characteristic (ROC) analysis were used to identify independent predictors of FR.
Main Results:
- Of 30 patients, 13 (43.3%) experienced FR. The FR group had a significantly higher baseline National Institutes of Health Stroke Scale (NIHSS) score (median 19 vs. 10; p <0.01).
- The NIHSS score was independently associated with FR (odds ratio, 1.18; p = 0.044).
- ROC analysis identified an NIHSS score of 11 as a potential cutoff for predicting FR (area under the curve, 0.76). Procedural factors were not significant predictors after adjustment.
Conclusions:
- Higher baseline NIHSS scores are associated with futile recanalization after MT in MCA M2 occlusion stroke.
- An NIHSS score of 11 may serve as a practical reference for risk stratification in these patients.
- Baseline neurological severity appears to influence clinical outcomes more than procedural factors following successful reperfusion.