Related Experiment Video
Updated: Jun 26, 2026
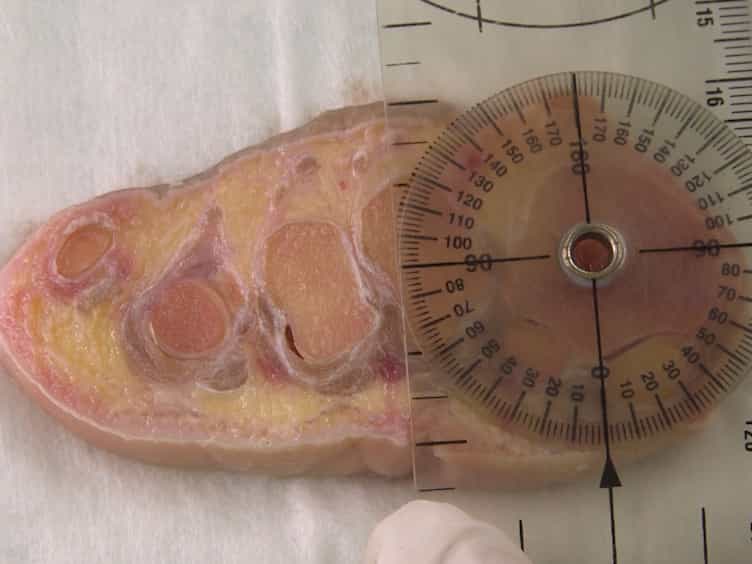

An Anatomical Study of Nerves at Risk During Minimally Invasive Hallux Valgus Surgery
Published on: February 17, 2018
Defining Potential Neurovascular Risk Zones in Superficial Plantar-Medial Release: An Anatomical Study
Elisabeth M Mandler1, Zehra Düzgün1, Johannes M Mittendorfer1
1Center for Anatomy and Cell Biology, Medical University of Vienna, 1090 Vienna, Austria.

Abstract:
Background: The superficial plantar-medial release (S-PMR) refers to a group of surgical procedures involving the release of the plantar aponeurosis and adjacent medial plantar soft tissues that are used in selected cases of plantar fasciitis and cavovarus foot deformity. The procedure aims to address pain and contracture of the plantar aponeurosis and intrinsic foot muscles, which may contribute to pathological foot alignment and gait instability. Due to the close proximity of highly variable neurovascular structures in the plantar region, precise anatomical knowledge and a patient-specific, personalized approach are essential to reduce the risk of iatrogenic injury during surgery. This study defined procedure-specific anatomical "low-risk" and "high-risk" zones. Methods: From the initial forty-two included feet, one specimen was excluded due to insufficient tissue quality, leaving forty-one specimens for analysis. The plantar aponeurosis, origins of the abductor hallucis muscle and regional neurovascular structures were analyzed. Distances between key landmarks were measured. Results: Abductor hallucis origins I and IV were present in all specimens, while origins II and III showed variable presence. Subdivision of muscle origin I was observed and was associated with the course of the medial calcaneal nerve. The medial calcaneal nerve demonstrated the closest proximity to origin I (3.2 mm) whereas both the medial and lateral plantar nerves showed close proximity to origin II (3 mm and 5.3 mm). Conclusion: Significant interindividual variability exists in the plantar region, highlighting the need for a personalized, anatomy-based approach for patients considered for surgical intervention. Anatomical "high-risk" zones were identified between origin I and the medial calcaneal nerve and near origin II by the bifurcation of the tibial nerve and posterior tibial artery. Anatomical "low-risk" zones were defined as dorsal regions at the calcaneus between origin I and the tibial neurovascular bundle, as well as medial areas near the malleolus.