Related Experiment Video
Updated: Jun 26, 2026
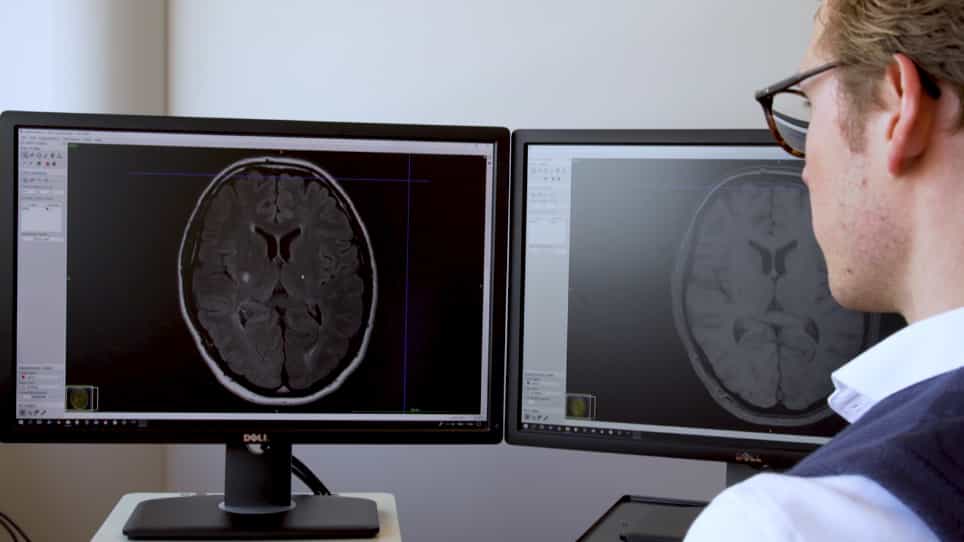

Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
The Role of AI-Based Software BrainScan in the Interpretation of Non-Contrast Head CT in Acute Ischemic Stroke: An
Eray Halil1,2, Ivan Sitnikov1,2, Neli Atanasova3
1Department of Neurology, Medical University of Plovdiv, 15A Vasil Aprilov Blvd., 4002 Plovdiv, Bulgaria.

Background/Objectives:
Artificial intelligence (AI) tools are increasingly integrated into acute stroke imaging workflows, but real-world performance for ischemia detection on non-contrast CT (NCCT) remains incompletely validated by investigators independent of the developer. This study externally validated the BrainScan AI system in an unselected, consecutively enrolled emergency cohort.
Methods:
Consecutive adult patients undergoing NCCT under the routine acute stroke protocol at a single tertiary centre between January and December 2025 were prospectively enrolled. The reference standard was the post-consensus radiological diagnosis, supplemented where available by follow-up imaging and clinical course. Primary outcomes were diagnostic accuracy for ischemia and intracranial haemorrhage detection, assessed by sensitivity, specificity, predictive values, likelihood ratios, and area under the ROC curve (AUC; DeLong). Pre-specified secondary analyses included regional sensitivity, confidence-score behaviour, artefact robustness, threshold sensitivity, a cluster-robust bootstrap for within-patient correlation, and a quantitative bias analysis under non-differential reference-standard misclassification. Sample size adequacy was assessed using a precision-based framework.
Results:
A total of 1419 NCCT examinations from 1260 patients were analysed. Ischemia sensitivity was 59.2% (95% CI 52.1-66.1) and specificity was 99.8% (99.4-100), with an AUC of 0.930 (0.906-0.954). The Youden-optimal threshold (0.055) recovered sensitivity to 86.1% with negligible specificity loss, reflecting a markedly bimodal score distribution. Regional sensitivity was lower in infratentorial structures. Bias-corrected estimates were stable across all reference-standard parameters consistent with the data. Haemorrhage detection performed substantially better (sensitivity 96.7%; AUC 0.983).
Conclusions:
The system shows excellent specificity and strong discrimination but moderate sensitivity for ischemia, supporting its role as a rule-in adjunct rather than a stand-alone tool, pending multicentre validation and site-specific threshold recalibration.
