Related Experiment Video
Updated: Jun 27, 2026

Assessment of Human Natural Killer Cell Events Driven by FcγRIIIa Engagement in the Presence of Therapeutic Antibodies
Published on: May 22, 2020
Mechanistic modeling of FcRn-dependent IgG drug interactions: Clinical applications and dosing implications
Paridhi Gupta1, Vivaswath S Ayyar2
1Department of Pharmaceutical Sciences, College of Pharmacy, University of Tennessee Health Science Center, Memphis, TN, USA.

Concomitant use of intravenous immunoglobulin (IVIG) with monoclonal antibodies (mAbs) or bispecific T-cell engagers (TCEs) is routinely encountered across autoimmune diseases, B-cell malignancies, immunodeficiencies, and transplantation. These therapies share a key salvage pathway through the neonatal Fc receptor (FcRn), raising the potential for pharmacokinetic (PK) and pharmacodynamic (PD) interactions. A mechanistic model of IgG disposition originally developed in mice was extended and revalidated with an array of human datasets to investigate how IVIG dose, timing, and IgG pool dynamics influence therapeutic IgG behavior and PK/PD outcomes. The model captures endogenous and exogenous IgG kinetics via FcRn-mediated recycling in a peripheral (endosomal) compartment, coupled with first-order catabolism of unbound IgG. Simultaneous model-fitting against clinical data reproduced serum IgG kinetics and endogenous/pathogenic IgG reductions across autoimmune and transplant settings. It recapitulated the ~36% decrease in tesidolumab exposure observed during IVIG co-administration in renal transplant recipients, largely explaining associated PD alterations. In pemphigus vulgaris, model-predicted total IgG increases following 2 g/kg IVIG aligned with observed values. Predicted endogenous IgG decline mirrored the time-course of anti-BP180 autoantibody reduction. Upon suitably adapting and requalifying the model, it was applied to examine two co-therapy scenarios: (i) IVIG supplementation in multiple myeloma patients receiving the TCE teclistamab, and (ii) immunosuppressive rituximab-IVIG co-therapy for transplant desensitization. Simulations revealed how IVIG co-therapy may alter mAb effects depending on IVIG regimen, IgG pool dynamics, and the exposure-response relationship of the mAb. This generalizable framework supports model-informed drug development and prospective management of therapeutic IgG interactions.
Concomitant use of intravenous immunoglobulin (IVIG) with monoclonal antibodies (mAbs) or bispecific T-cell engagers (TCEs) is routinely encountered across autoimmune diseases, B-cell malignancies, immunodeficiencies, and transplantation. These therapies share a key salvage pathway through the neonatal Fc receptor (FcRn), raising the potential for pharmacokinetic (PK) and pharmacodynamic (PD) interactions. A mechanistic model of IgG disposition originally developed in mice was extended and revalidated with an array of human datasets to investigate how IVIG dose, timing, and IgG pool dynamics influence therapeutic IgG behavior and PK/PD outcomes. The model captures endogenous and exogenous IgG kinetics via FcRn-mediated recycling in a peripheral (endosomal) compartment, coupled with first-order catabolism of unbound IgG. Simultaneous model-fitting against clinical data reproduced serum IgG kinetics and endogenous/pathogenic IgG reductions across autoimmune and transplant settings. It recapitulated the ~36% decrease in tesidolumab exposure observed during IVIG co-administration in renal transplant recipients, largely explaining associated PD alterations. In pemphigus vulgaris, model-predicted total IgG increases following 2 g/kg IVIG aligned with observed values. Predicted endogenous IgG decline mirrored the time-course of anti-BP180 autoantibody reduction. Upon suitably adapting and requalifying the model, it was applied to examine two co-therapy scenarios: (i) IVIG supplementation in multiple myeloma patients receiving the TCE teclistamab, and (ii) immunosuppressive rituximab-IVIG co-therapy for transplant desensitization. Simulations revealed how IVIG co-therapy may alter mAb effects depending on IVIG regimen, IgG pool dynamics, and the exposure-response relationship of the mAb. This generalizable framework supports model-informed drug development and prospective management of therapeutic IgG interactions.

Related Concept Videos
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:29
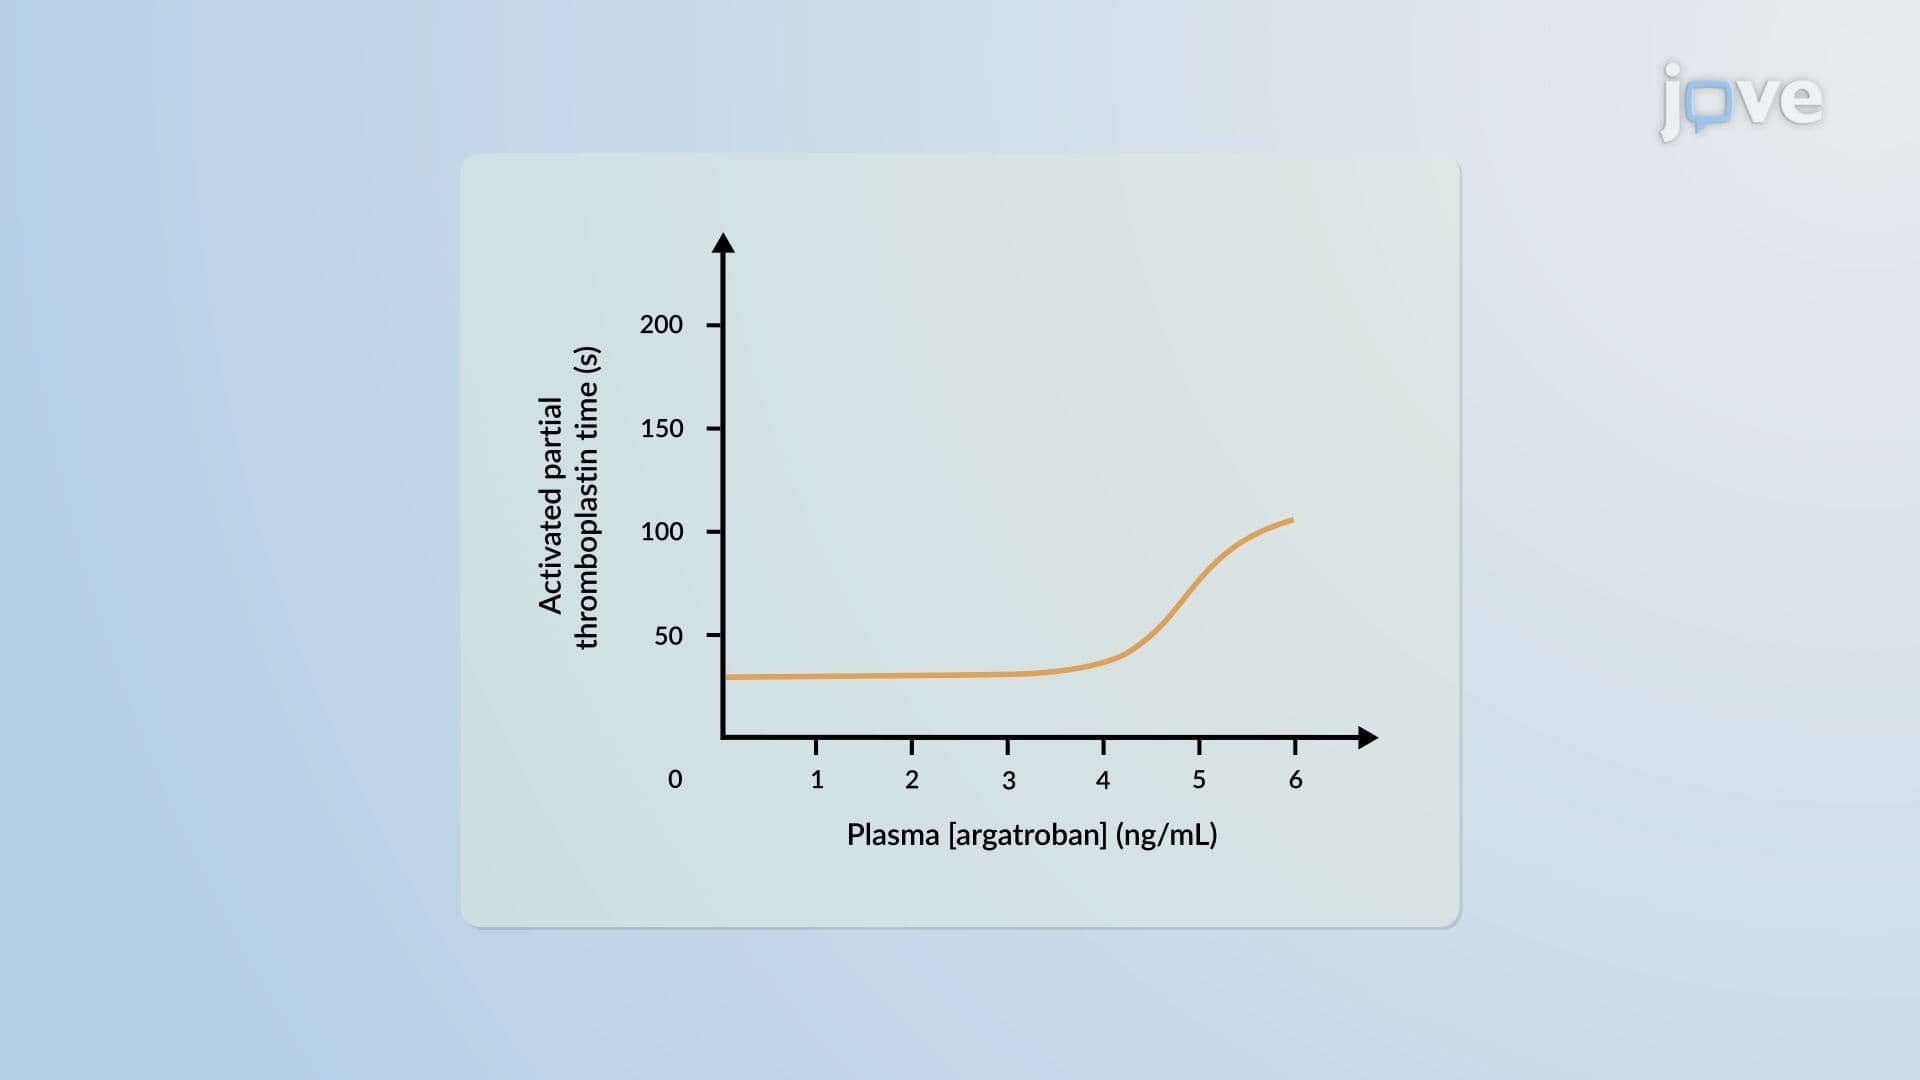
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model
 01:30
Quantitative Aspects of Drug-Receptor Interaction
 01:09
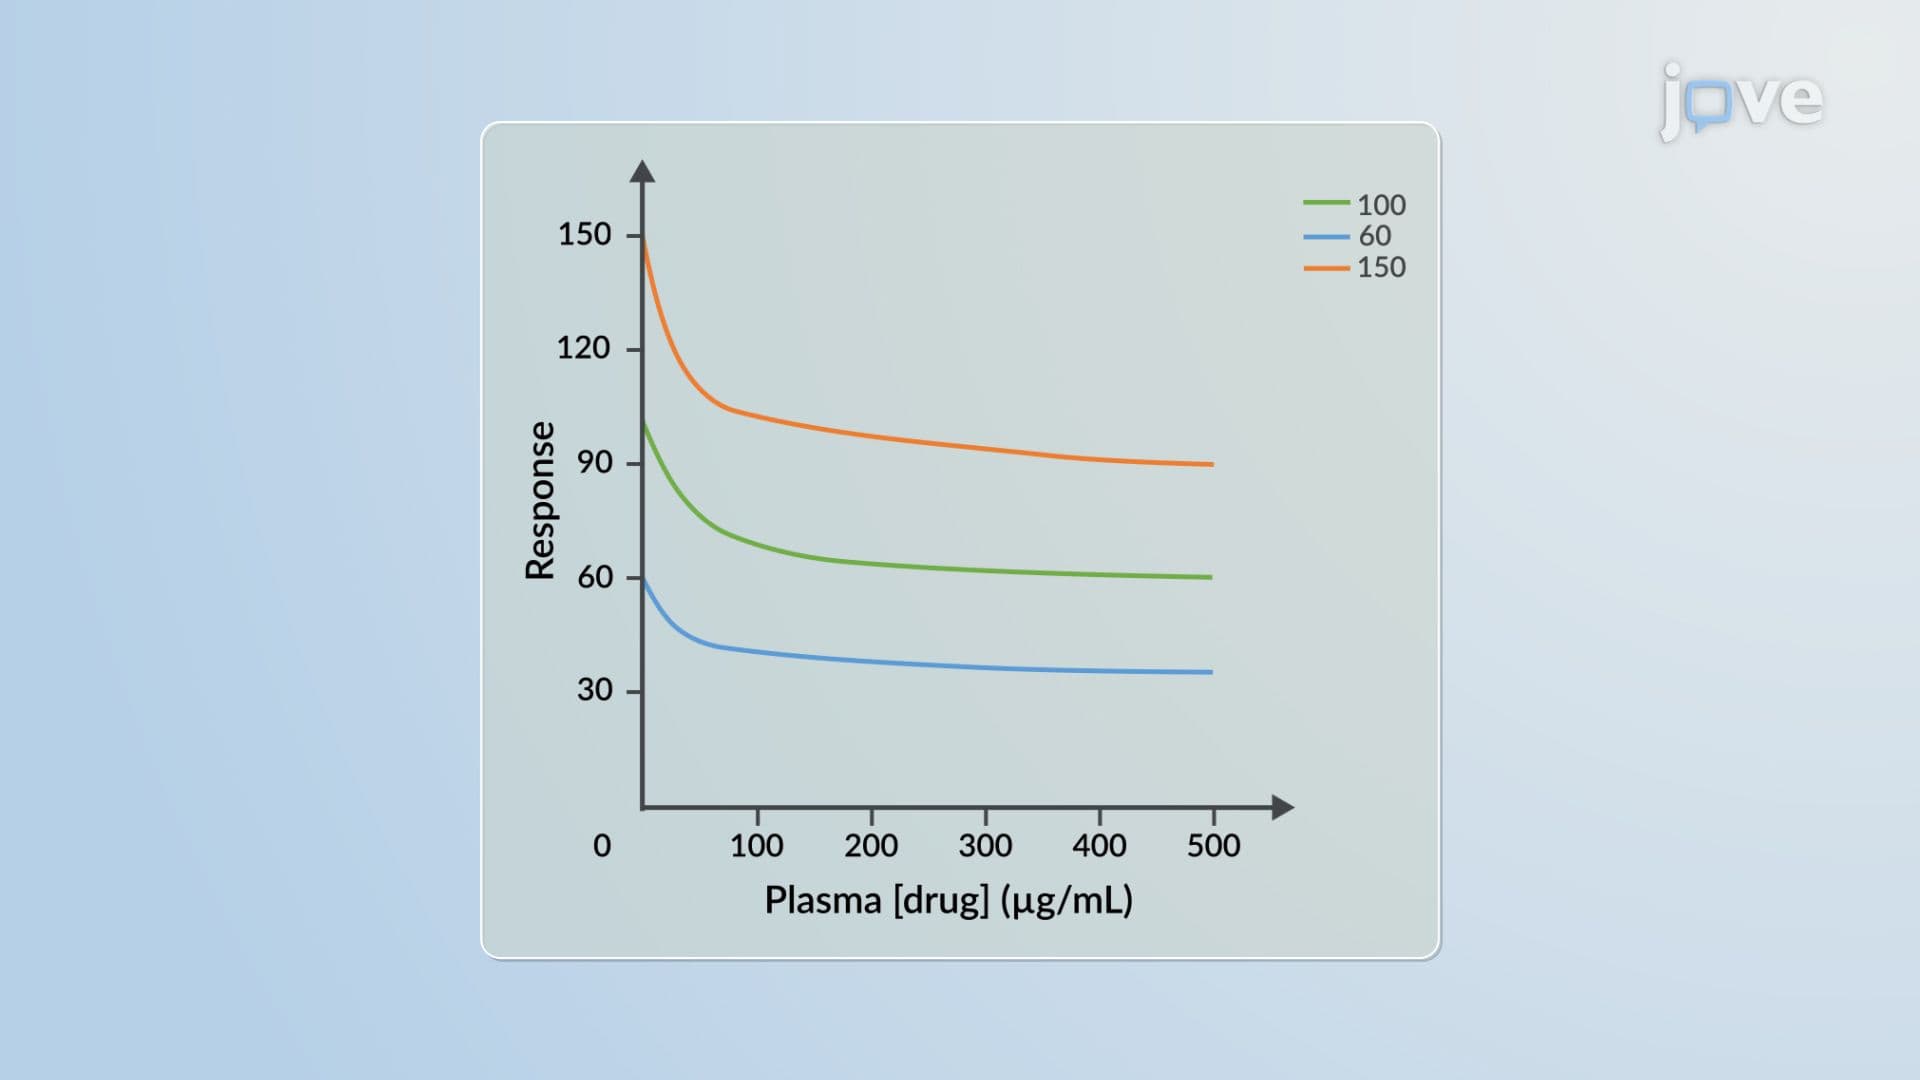
Pharmacodynamic Models: Additive and Proportional Drug Effect Model
 01:29
Drug-Receptor Interactions
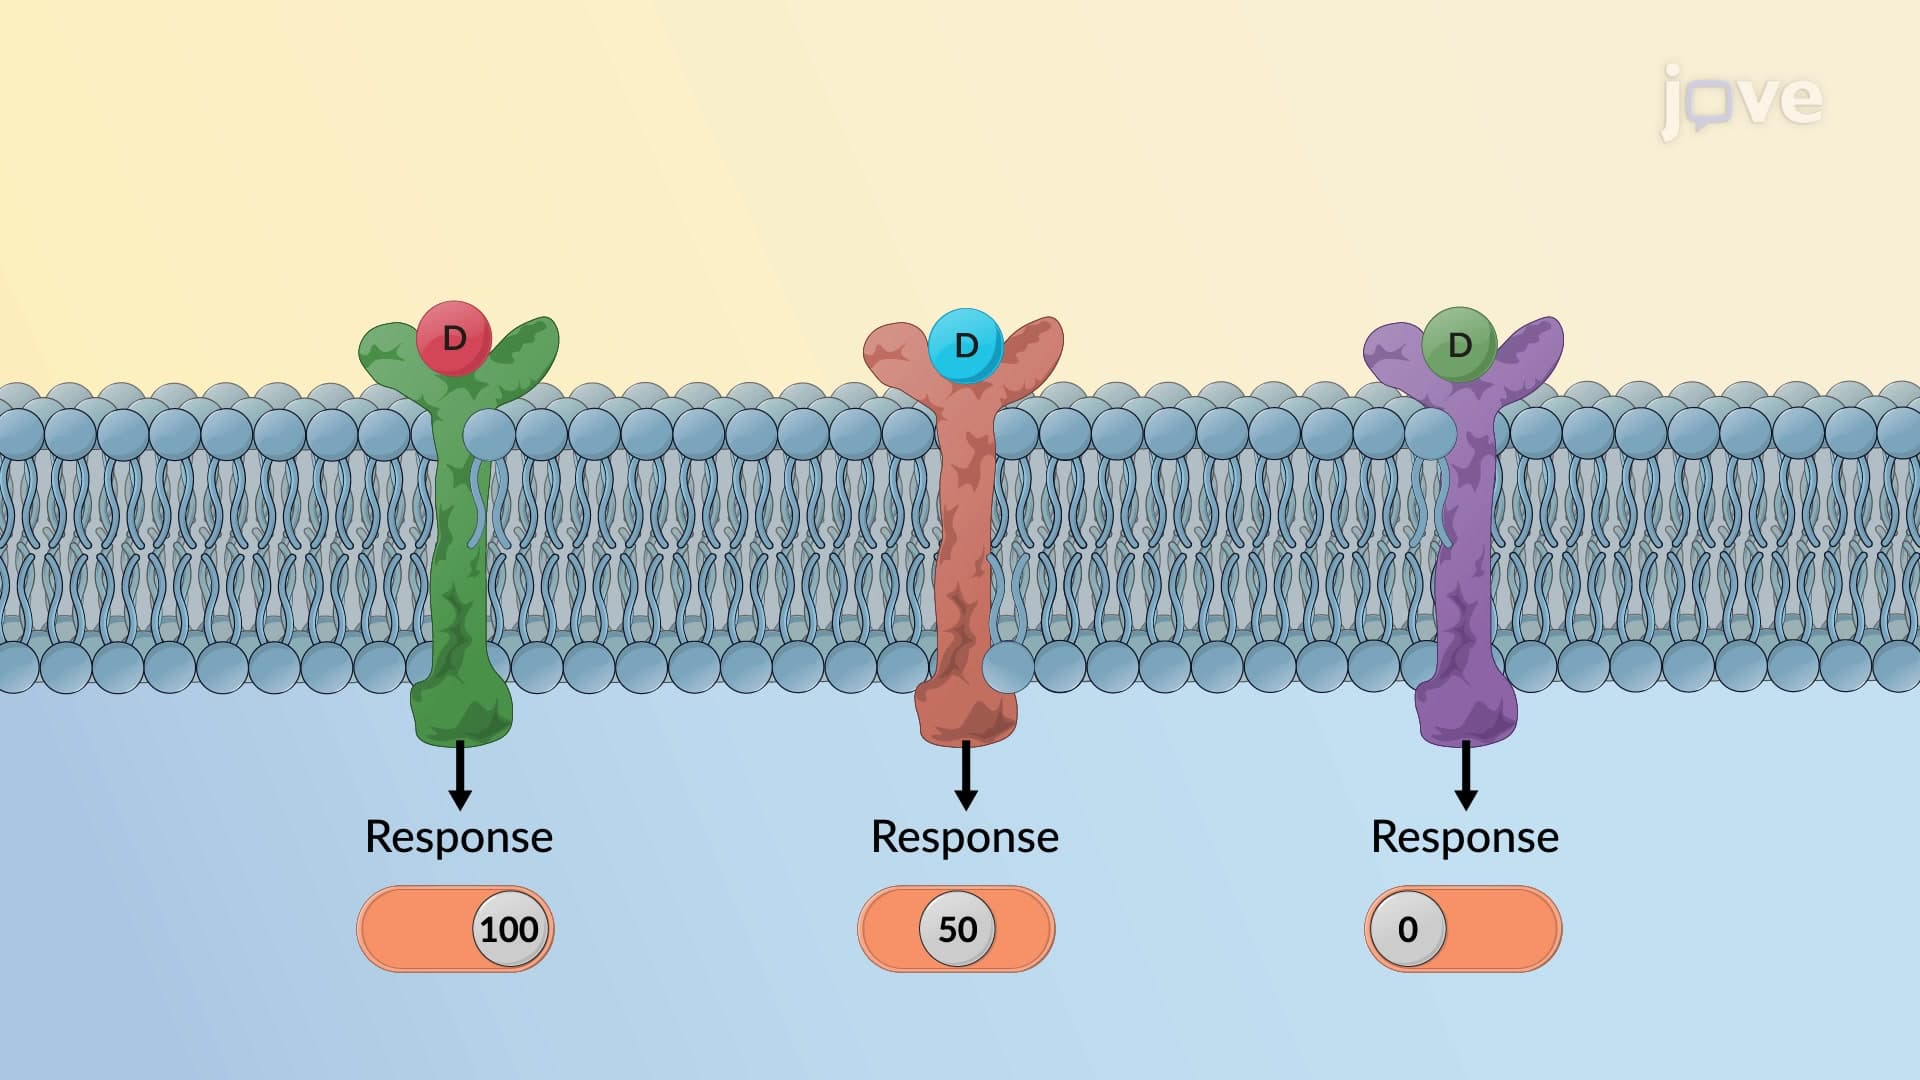
Several parameters, such as the drug's affinity for its receptor and its efficacy, which is its ability to activate the receptor, determine the drug's effect on the tissue.
 01:13
Physiological Pharmacokinetic Models: Assumption with Protein Binding