Related Experiment Video
Updated: Jun 27, 2026


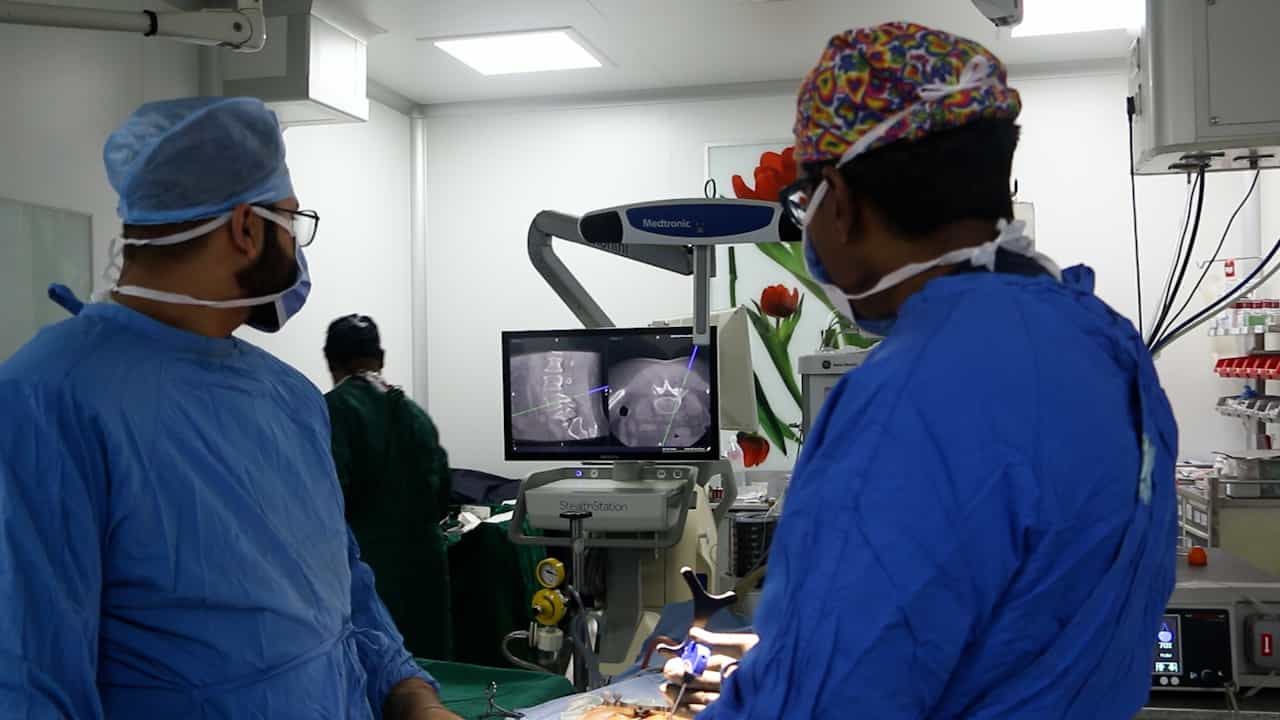
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Asymmetric Safety Corridors for Free-Hand S2-Alar-Iliac Screw Placement: Quantifying Direction-Specific Tolerance
Se Jun Park1, Dong Kyu Kim2, Sun Joon Yoo1
1Department of Neurosurgery, Yongin Severance Hospital, Yonsei University College of Medicine, Yongin 16995, Republic of Korea.

Abstract:
Background/Objectives: Optimal trajectories for S2-alar-iliac (S2AI) screw placement have been widely studied; however, in fluoroscopy-assisted free-hand techniques, exact reproduction is rarely achievable. This study aimed to quantify direction-specific safety margins around patient-specific optimal trajectories and to determine their relationship with pelvic parameters. Methods: We retrospectively analyzed patients who underwent S2AI screw fixation with available preoperative and postoperative CT imaging. Pelvic parameters, including pelvic tilt (PT), sacral slope (SS), and pelvic incidence (PI), were measured. Optimal transverse and sagittal screw angles were determined using CT-based planning. Postoperative CT was used to assess actual screw trajectories and cortical violations. Direction-specific generalized estimating equation models were used to evaluate associations between trajectory deviation and screw malposition. Receiver operating characteristic (ROC) analysis was performed to determine cutoff values for safe deviation. Results: A total of 62 patients (105 screws) were included in axial analysis and 41 patients (76 screws) in sagittal analysis. PT and PI showed significant inverse correlations with both optimal transverse and sagittal angles (all p < 0.001). Greater lateral and medial deviations were significantly associated with corresponding cortical violations (OR 2.33, 95% CI 1.51-3.59; and OR 2.10, 95% CI 1.40-3.15 per degree, respectively; both p < 0.001). Inferior deviation was significantly associated with violation in the sagittal plane (OR 1.39, 95% CI 1.18-1.65 per degree; p < 0.001), whereas superior deviation was not significant. ROC analysis demonstrated asymmetric safety margins: 1.5° lateral (AUC = 0.972), 8.1° medial (AUC = 0.965), and 18.5° inferior (AUC = 0.897). Conclusions: S2AI screw placement may be conceptualized as a tolerance-based process centered on a patient-specific optimal trajectory. Safety margins are direction-dependent and asymmetric, with a narrow tolerance for lateral deviation. These findings provide practical guidance for intraoperative trajectory adjustment in free-hand techniques.