Related Experiment Video
Updated: Jun 27, 2026
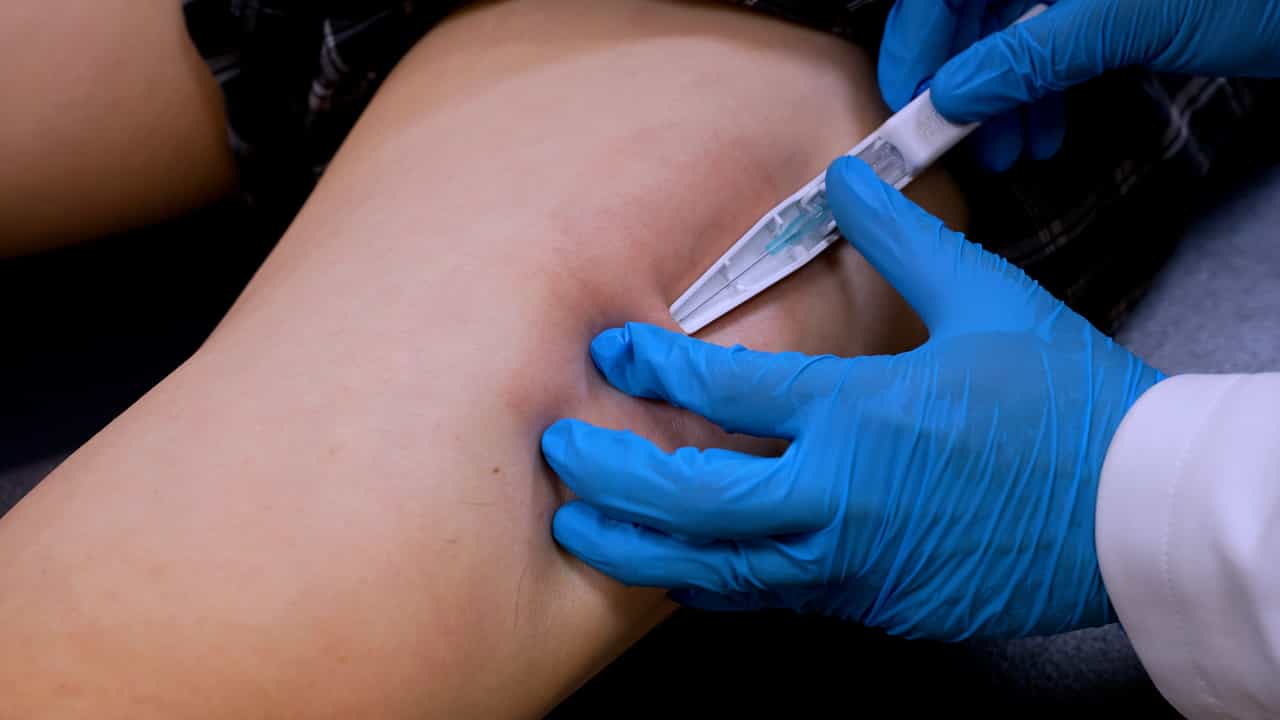

Fu's Subcutaneous Needling for Knee Osteoarthritis Pain
Published on: March 24, 2023
The Use of Physical Energy-Based Therapies in the Management of Osteoarthritis
Marco Giuseppe Musorrofiti1, Marco Bonifacio2, Valerio Cipolloni3
1Faculty of Exercise and Sport Sciences, Università Telematica eCampus, 22060 Novedrate, CO, Italy.

Abstract:
Physical energy-based therapies are non-invasive adjunctive interventions that deliver mechanical, electromagnetic, light, or radiofrequency/thermal energy to tissues with the aim of reducing symptoms and improving tolerance of active rehabilitation. Osteoarthritis (OA) is a heterogeneous whole-joint disorder in which cartilage degeneration, subchondral bone remodeling, synovitis, peri-articular tissue dysfunction, neuromuscular impairment, and pain sensitization may interact to produce pain, stiffness, and activity restriction. As conservative therapy for OA, education, progressive therapeutic exercise, weight management when indicated, and self-management remain the core of care. Nevertheless, some patients cannot fully participate in exercise because of pain, fear of movement, load intolerance, comorbidity, or limited access to supervised rehabilitation. This narrative review synthesizes evidence published mainly between 2016 and 2026 for extracorporeal shock wave therapy (ESWT), photobiomodulation/low-level laser therapy (PBMT/LLLT), pulsed electromagnetic field therapy (PEMF), transfer energy capacitive and resistive/capacitive-resistive electric transfer (TECAR/CRET) therapy, body weight support and aquatic unloading strategies, and mechanosonic vibration therapies. The available literature suggests that ESWT and PBMT/LLLT may provide short- to mid-term pain and function benefits in selected patients with knee OA when parameters are aligned with evidence-supported dosing windows. PEMF and vibration therapies show promising but less consistent effects because protocols, devices, sham conditions, and populations vary. TECAR/CRET and unloading approaches are best interpreted as enabling tools that may reduce guarding, improve walking tolerance, or increase the quality of therapeutic exercise, rather than stand-alone disease-modifying treatments. Current national and society guidelines consistently prioritize exercise, education, and weight management; most of the modalities reviewed here are absent from guidelines or are supported only indirectly, which justifies cautious wording and individualized use. A practical application model is, therefore, time-limited and goal-oriented: identify the barrier to rehabilitation, select a modality with a plausible mechanism and published protocol, monitor pain and functional response, and discontinue the modality if it does not improve participation in active care.
