Related Experiment Video
Updated: Jun 28, 2026
One-day Workflow Scheme for Bacterial Pathogen Detection and Antimicrobial Resistance Testing from Blood Cultures
Published on: July 9, 2012
Population pharmacokinetics and resistance patterns of vancomycin and amikacin in pediatric oncology patients
Khalid M Alkharfy1, Ajaz Ahmad1, Mitab Alenazi2
1Department of Clinical Pharmacy, College of Pharmacy, King Saud University, Riyadh, Saudi Arabia.

Insights
Febrile episodes in pediatric oncology patients often require vancomycin and amikacin. Standard dosing may lead to suboptimal exposure, necessitating personalized treatment and therapeutic drug monitoring for better outcomes.
Area of Science:
- Pharmacology
- Pediatric Oncology
- Infectious Diseases
Background:
- Febrile episodes in pediatric oncology patients with neutropenia are a clinical challenge.
- Prompt empiric antimicrobial therapy is crucial for these patients.
Purpose of the Study:
- To evaluate the pharmacokinetics (PK) and pharmacodynamics of vancomycin and amikacin in pediatric oncology patients.
- To identify factors influencing drug exposure and assess target attainment with standard dosing.
Main Methods:
- Retrospective review of 105 pediatric oncology patients.
- Collected data on demographics, clinical parameters, and vancomycin/amikacin serum concentrations.
- Population PK analyses were performed to identify covariates and project target attainment.
Main Results:
- Standard vancomycin and amikacin dosing resulted in suboptimal exposure and target attainment in a significant proportion of patients.
- Body weight, bilirubin level (vancomycin), and tumor type (amikacin) were identified as key PK covariates.
- Dose escalation recommendations were provided to improve exposure adequacy.
Conclusions:
- Significant pharmacokinetic variability of vancomycin and amikacin exists in pediatric oncology patients.
- Individualized dosing strategies and therapeutic drug monitoring are essential for optimizing antimicrobial therapy in this population.
Abstract:
Febrile episodes in pediatric oncology patients, particularly those with neutropenia, pose major clinical challenges and require prompt empiric antimicrobial therapy. The current study evaluated the pharmacokinetics (PK) and pharmacodynamics of vancomycin and amikacin in pediatric oncology patients. A retrospective review was conducted in 105 pediatric oncology patients admitted between January 2020 and January 2024. Data collected included demographic characteristics, vital signs, laboratory findings, neutropenic status, malignancy type, microbial cultures, resistance profiles, and total serum concentrations of vancomycin and amikacin obtained during routine therapeutic drug monitoring (TDM). Blood cultures were positive in ∼39% of cases, with Staphylococcus epidermidis (∼24%) and methicillin-resistant Staphylococcus aureus (∼16%) being the predominant isolates. Vancomycin peak and trough concentrations were 18.37 ± 7.42 μg/mL and 8.63 ± 3.81 μg/mL, respectively. Amikacin peak and trough concentrations were 26.27 ± 12.11 μg/mL and 1.09 ± 0.67 μg/mL, respectively. Population PK analyses identified body weight and bilirubin level as key covariates for vancomycin (CL = 0.169 L/h/kg; V = 1.519 L/kg), and body weight and tumor type for amikacin (CL = 0.182 L/h/kg; V = 0.505 L/kg). Solid tumors were associated with a lower amikacin volume of distribution (∼0.32 L/kg). The calculated area under the curve (AUC) of vancomycin exposure over one dosing interval was estimated as AUC0-6 = 62.76 ± 22.25 μg·h/mL; assuming steady-state every 6 hours dosing, the corresponding daily exposure was AUC0-24 = 251.04 ± 89.00 μg·h/mL. Using a reference minimum inhibitory concentration (MIC) of 1 μg/mL, the mean vancomycin AUC0-24/MIC remained well beneath the therapeutic target of ≥400. Similarly, the calculated Cpeak/MIC of amikacin was 6.57 ± 3.03, which was below the optimal PK/pharmacodynamics target (ie, 8-10), with only ∼30% accomplished therapeutic goals, highlighting the need for personalized dosing and TDM in this cohort. Analytical target attainment projections derived from the final population PK models confirmed that standard dosing regimens achieved suboptimal probability of target attainment for both drugs, and indicated that dose escalation to at least 20 mg/kg every 6 hours for vancomycin and 22.5 mg/kg every 24 hours for amikacin would be required to meaningfully improve exposure adequacy across this population. These outcomes emphasize the need for individualized dosing strategies and TDM in pediatric oncology patients receiving antimicrobial therapy. SIGNIFICANCE STATEMENT: Vancomycin and amikacin display pharmacokinetic variability in pediatric oncology patients, with body weight identified as determinant for both drugs, bilirubin level for vancomycin, and tumor type for amikacin. standard dosing was associated with lower-than-target exposure in a proportion of patients. Analytical target attainment projections from population PK models quantified this exposure gap and identified dose requirements to improve target attainment across this population. Findings support therapeutic drug monitoring and evaluation of individualized dosing approaches in this population.
Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
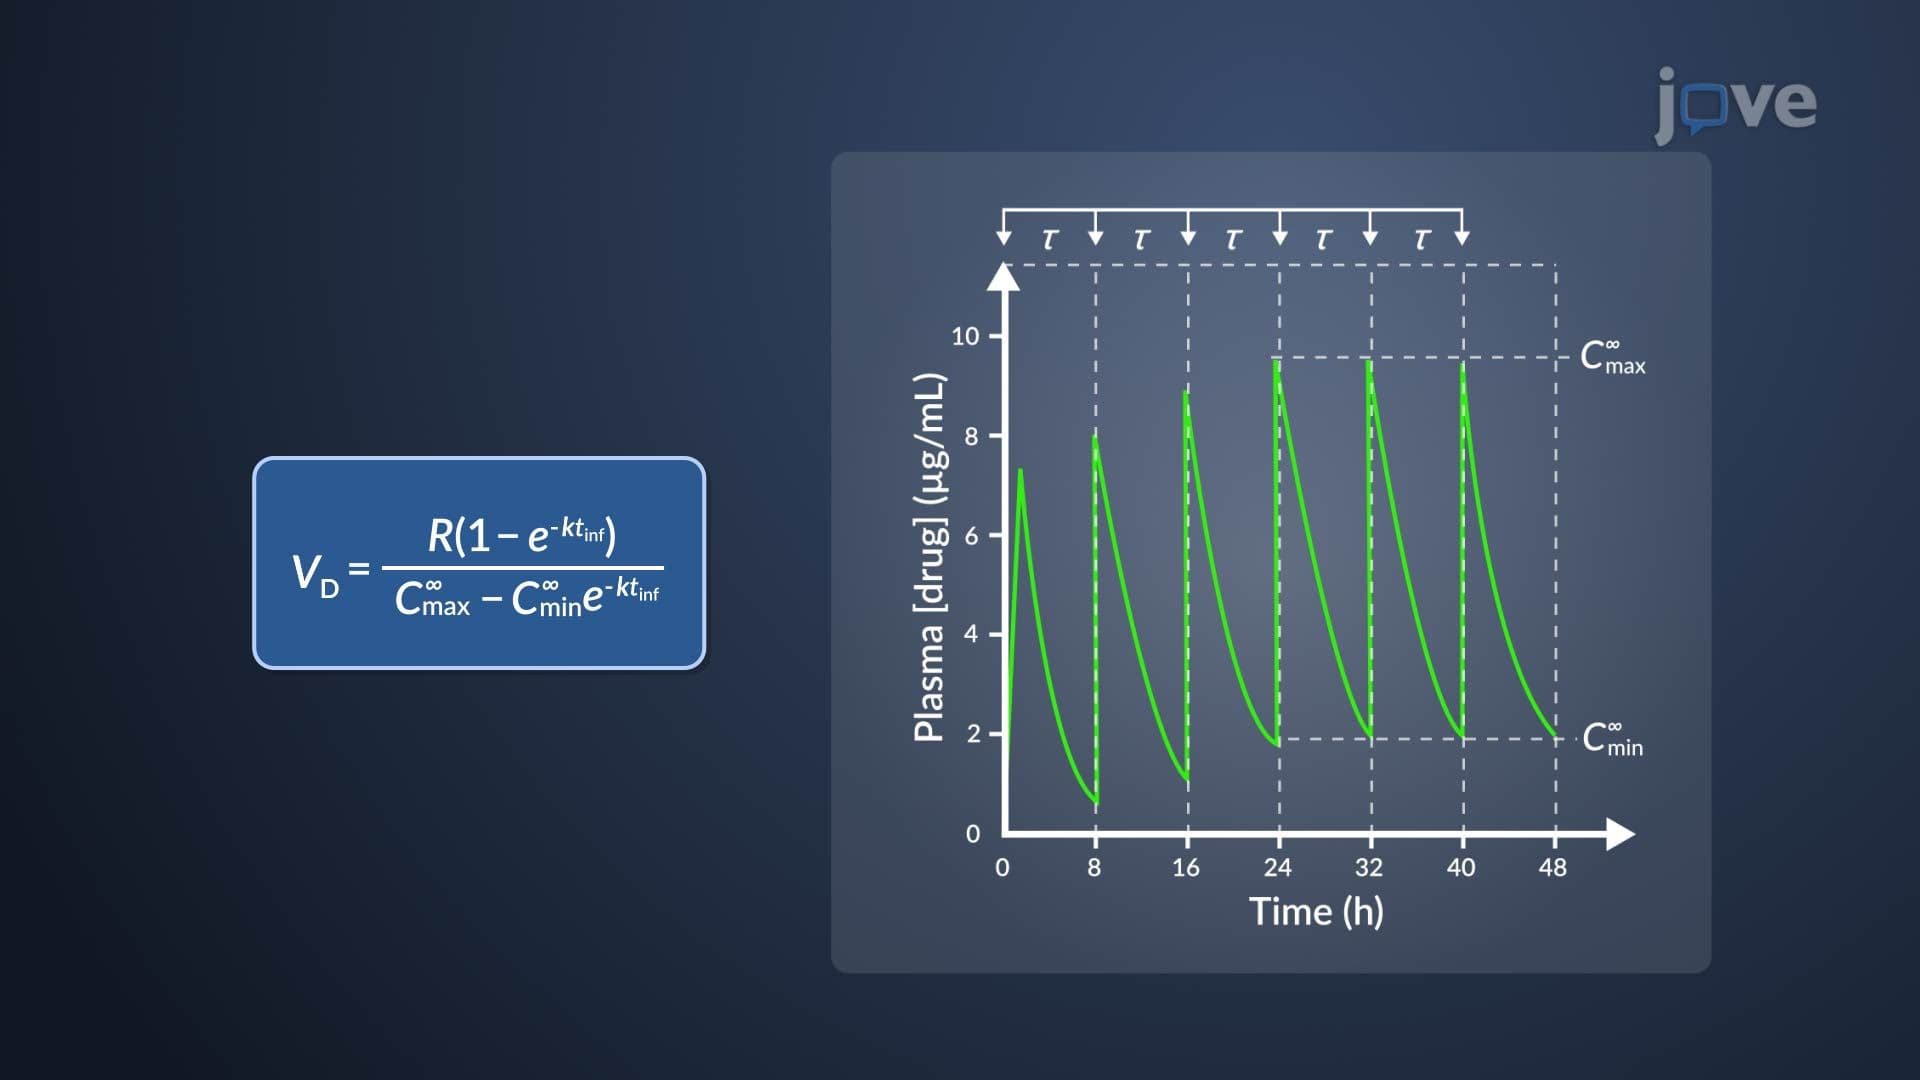 01:20
Estimation of k and VD of Aminoglycosides
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
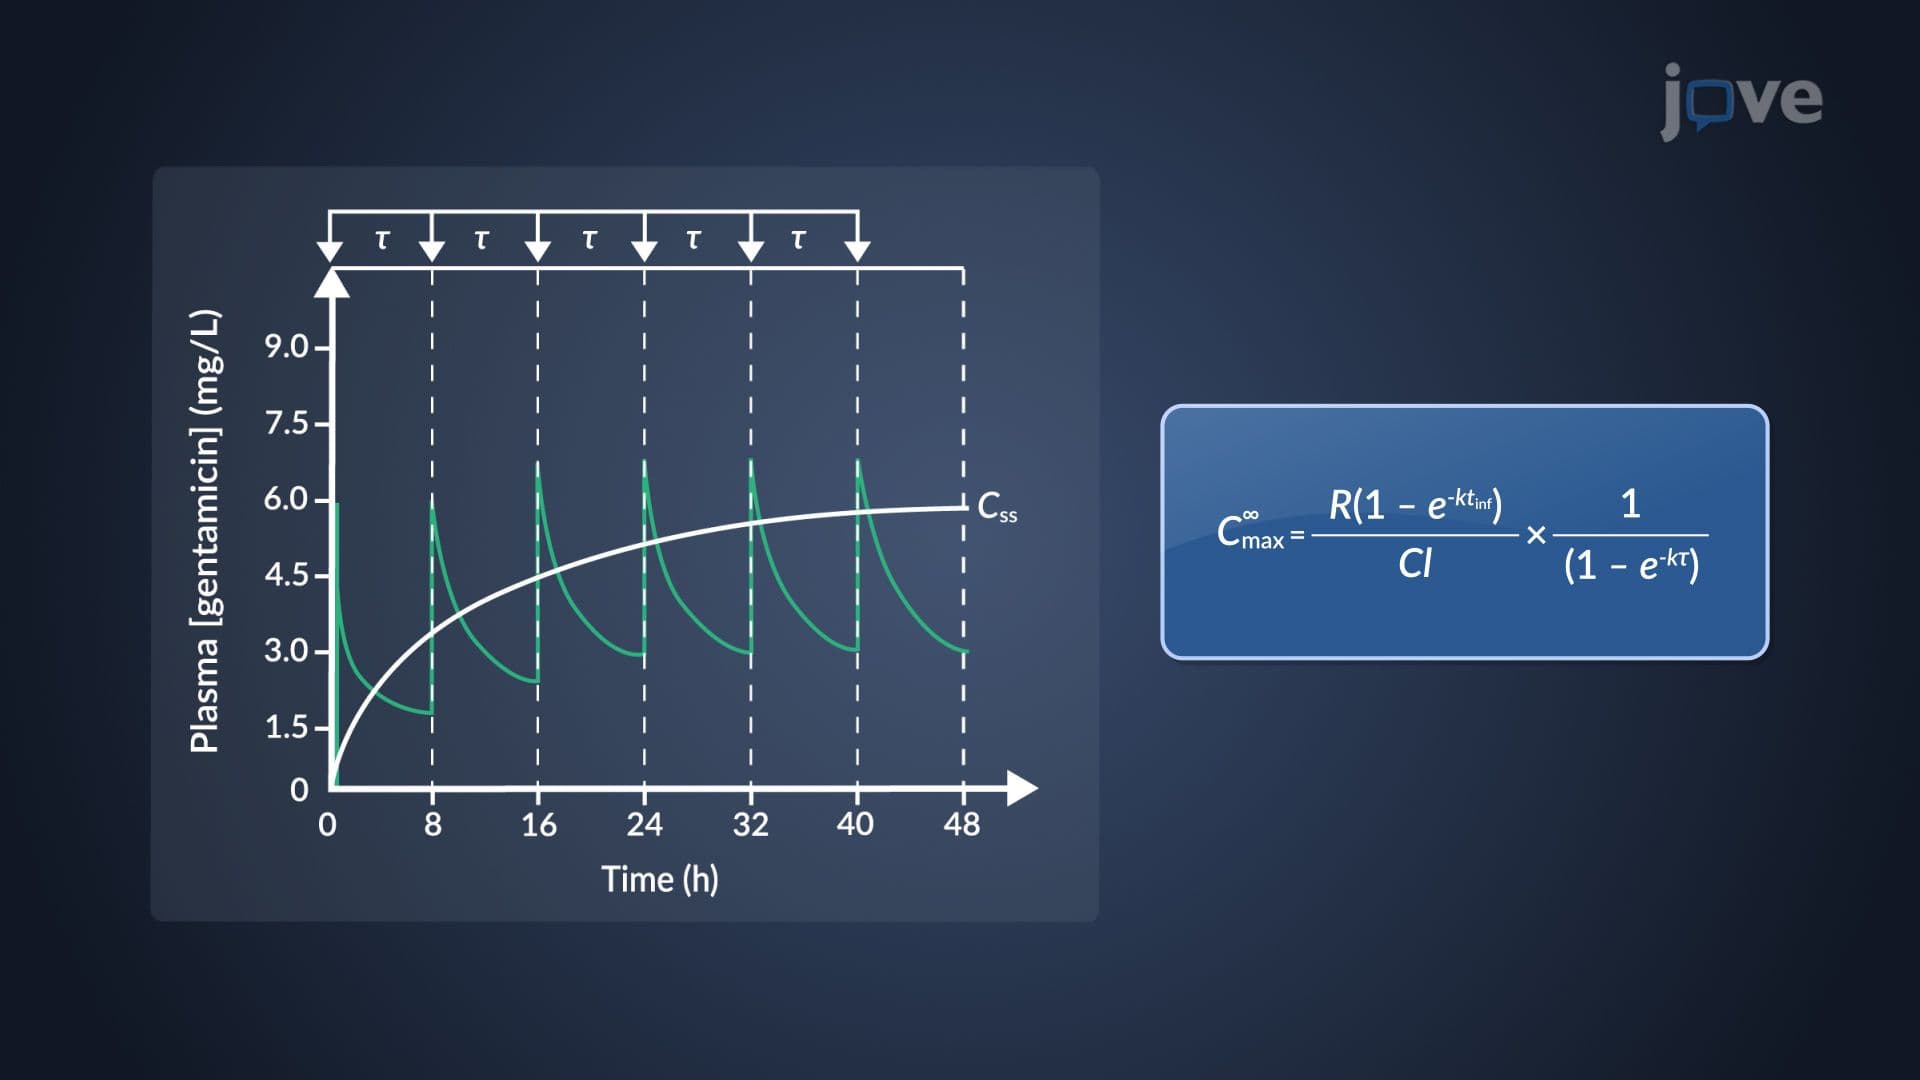 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations