Related Experiment Video
Updated: Jun 30, 2026
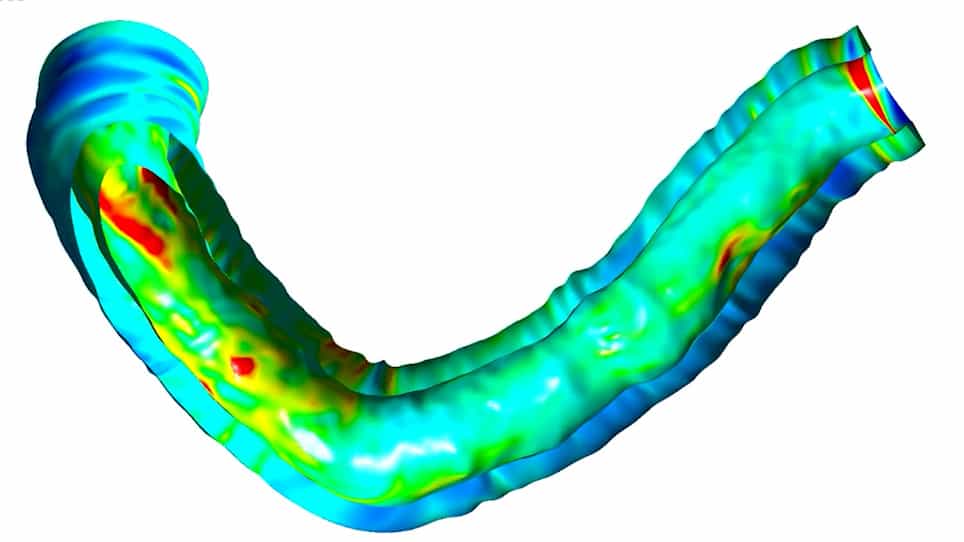
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Association of AI-assisted quantitative coronary plaque burden and CT-derived fractional flow reserve with major
Xinwei Zhang1, Mengyuan Bao1, Yongshun Wu1
1Imaging Center, The First Affiliated Hospital of Xinjiang Medical University, No. 137 South Liyushan Road, Xinshi District, Urumqi, Xinjiang, P.R. China.

Insights
Artificial intelligence-quantified noncalcified plaque burden is the strongest predictor of major adverse cardiovascular events (MACEs). CT-derived fractional flow reserve (CT-FFR) did not significantly improve MACE prediction when added to plaque parameters.
Area of Science:
- Cardiovascular Imaging
- Artificial Intelligence in Medicine
- Predictive Analytics in Cardiology
Background:
- Coronary artery disease (CAD) management relies on accurate risk stratification.
- Coronary computed tomography angiography (CCTA) provides detailed plaque information.
- CT-derived fractional flow reserve (CT-FFR) assesses lesion-specific ischemia.
Purpose of the Study:
- To evaluate the association of AI-quantified coronary plaque parameters and CT-FFR with major adverse cardiovascular events (MACEs).
- To derive optimal risk cutoff values for plaque burden in patients with CAD.
- To compare the predictive performance of plaque burden, CT-FFR, and combined models for MACEs.
Main Methods:
- Retrospective analysis of 381 patients undergoing CCTA.
- AI quantification of coronary plaque parameters and calculation of CT-FFR.
- MACEs defined as composite of death, myocardial infarction, heart failure death, malignant arrhythmia, revascularization, and angina rehospitalization over 18 months.
- Development and comparison of plaque, CT-FFR, combined, LASSO-Cox, and Cox survival neural network models.
Main Results:
- 67 (17.6%) patients experienced MACEs.
- Total noncalcified percent atheroma volume (NCPAV) > 4.68% was the strongest predictor of MACEs (HR 5.073).
- The combined model showed comparable performance to the plaque model alone; CT-FFR did not significantly improve prediction.
- Landmark analyses suggested a potential trend for CT-FFR's incremental value after excluding early revascularization events.
Conclusions:
- AI-quantified noncalcified plaque burden is a potent predictor of MACEs in CAD patients.
- CT-FFR did not demonstrate clinically meaningful incremental value over plaque burden for overall MACE prediction.
- Exploratory analyses indicated potential prognostic weight of right coronary artery plaque burden, requiring further validation.
Rationale And Objective:
This single-center retrospective study evaluated the associations of AI-quantified coronary plaque parameters and CT-derived fractional flow reserve (CT-FFR) with major adverse cardiovascular events (MACEs) in patients with coronary artery disease, and derived optimal risk cutoff values for plaque burden.
Methods:
A total of 381 patients who underwent CCTA were consecutively enrolled. MACEs were defined as a composite of all-cause death, myocardial infarction (fatal and nonfatal), heart failure death, malignant arrhythmia, coronary revascularization, and rehospitalization for angina exacerbation. Maximum follow-up was 18 months. Risk cutoff values were derived from receiver operating characteristic analysis. Univariate and multivariate Cox regression, Kaplan-Meier analysis, and five predictive models (plaque model, CT-FFR model, combined model, LASSO-Cox, and Cox survival neural network) were constructed.
Results:
Among 381 patients, 67 (17.6%) developed MACEs. All six total plaque parameters showed significant associations with MACEs. In multivariate Cox regression, total noncalcified percent atheroma volume (NCPAV) > 4.68% emerged as the strongest predictor (HR 5.073, 95% CI 2.930-8.786, P < 0.001). Analyzed continuously, each 1-SD increase in total-NCPAV conferred an HR of 1.82 (95% CI 1.54-2.14, P < 0.001). The combined model C-index was 0.750 (95% CI 0.696-0.804; optimism-corrected 0.708), comparable to the plaque model alone (0.744, 95% CI 0.686-0.801; corrected 0.705). The LASSO-Cox and Cox survival neural network models achieved C-indices of 0.747 (95% CI 0.674-0.816) and 0.730 (95% CI 0.628-0.833), respectively. In landmark sensitivity analyses excluding early events, the combined model C-index rose to 0.792, with the likelihood ratio test P value narrowing from 0.117 to 0.061, suggesting a trend toward incremental value for CT-FFR after accounting for potential incorporation bias.
Conclusions:
AI-quantified total noncalcified plaque burden was the strongest predictor of MACEs. The addition of CT-FFR to plaque parameters did not provide a clinically meaningful or statistically significant improvement in overall model performance, including discrimination, model fit, reclassification, or discrimination slope. Although landmark analyses suggested a possible trend toward incremental value after exclusion of early revascularization-driven events, this finding should be considered exploratory and requires further validation. Vessel-specific analyses identified RCA plaque burden as having the greatest prognostic weight among the target vessels; however, this exploratory finding also warrants confirmation in independent cohorts.
Related Concept Videos
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:30
Acute Coronary Syndrome III: Diagnostic Studies