Related Experiment Video
Updated: Jun 30, 2026
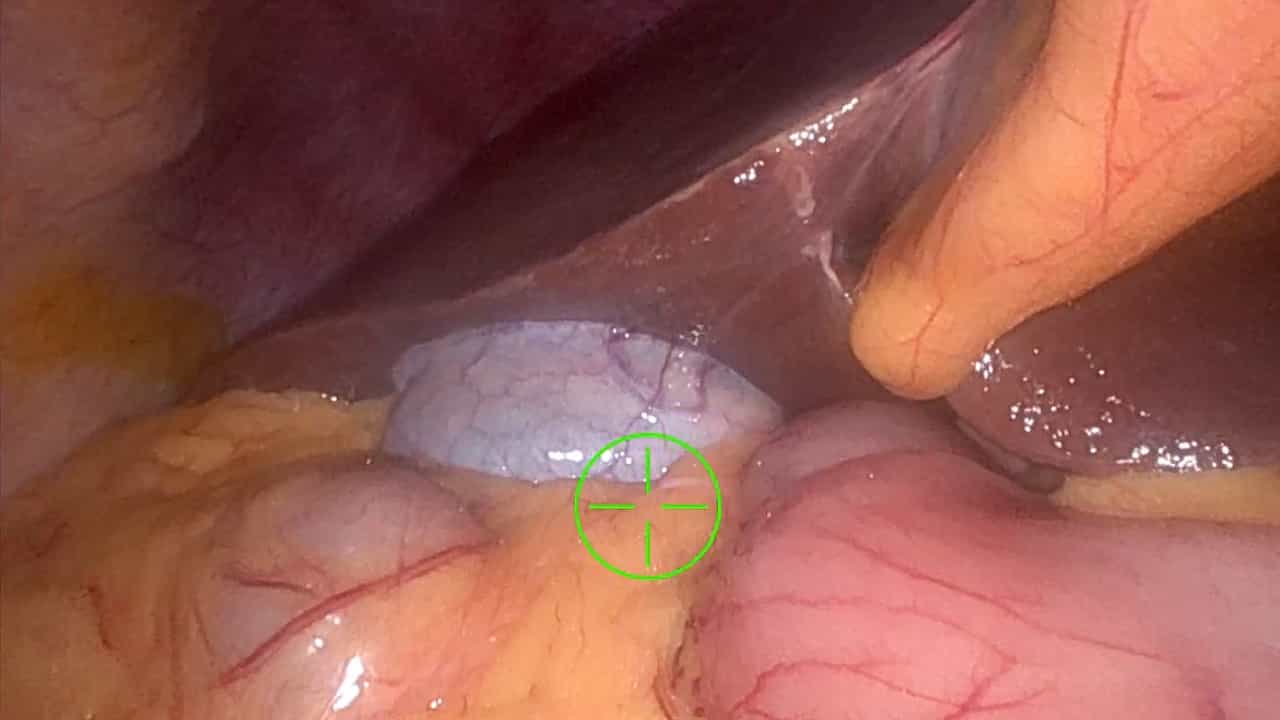

Application of Robot-assisted Pancreaticobiliary Junction Resection in Benign Duodenal Tumors
Published on: December 20, 2024
Case Report: a case of prolonged post-traumatic duodenal obstruction complicated by traumatic pancreatitis and
Li-Bin Deng1, Wen-Na Liu2, Zheng-Hong Jiang1
1Department of Gastrointestinal Hernia and Abdominal Wall Surgery, Affiliated Hospital of Chengdu University, Chengdu, Sichuan, China.

Background:
Post-traumatic gastrointestinal injuries, especially those involving the duodenum and proximal jejunum, present significant management challenges. Complications such as retroperitoneal abscess, high intestinal obstruction, and secondary pancreatitis can lead to prolonged fasting and severe nutritional deficiencies. We report a complex case where a patient developed a rare triad of post-operative combined abscess (retroperitoneal abscess and intra-abdominal abscess)-induced high intestinal obstruction, traumatic pancreatitis, and subsequent Wernicke's encephalopathy (WE), highlighting the diagnostic and therapeutic complexities.
Case Presentation:
A 52-year-old woman was admitted 10 days after undergoing a partial jejunectomy for a traumatic jejunal perforation. Post-admission, she developed a combined abscess (retroperitoneal abscess and intra-abdominal abscess) adjacent to the duodenum, causing high intestinal obstruction manifested by intractable nausea and vomiting. Despite conservative management and placement of a nasointestinal decompression tube, her symptoms persisted. The clinical course was further complicated by a significant elevation in serum lipase, indicating traumatic pancreatitis. Following prolonged fasting and vomiting, the patient received total parenteral nutrition (TPN) during the prolonged period of duodenal obstruction; however, the thiamine content in the TPN formulation was inadequate, contributing to the development of thiamine deficiency. The patient presented with atypical neurological symptoms, including severe dizziness, orthostatic instability, and nystagmus (horizontal and vertical). Brain MRI revealed characteristic hyperintensities in the periaqueductal gray matter, mammillary bodies, and bilateral medial thalami, confirming a diagnosis of Wernicke's encephalopathy. High-dose parenteral thiamine (vitamin B1) was promptly initiated, resulting in rapid and significant improvement in both neurological and gastrointestinal symptoms. Subsequently, the combined abscess (retroperitoneal abscess and intra-abdominal abscess) resolved, duodenal patency was confirmed by imaging, and the patient successfully transitioned to an oral diet.
Conclusion:
This case underscores the critical importance of a multidisciplinary approach in managing complex post-traumatic gastrointestinal sequelae. It highlights the need for a high index of suspicion for Wernicke's encephalopathy in patients with prolonged fasting, especially when neurological symptoms are atypical. Early recognition and treatment with thiamine are paramount to prevent irreversible neurological damage. Furthermore, the interplay between mechanical obstruction, inflammation (pancreatitis and abscess formation), and metabolic derangements (thiamine deficiency) created a self-perpetuating cycle of morbidity that required sequential, targeted interventions.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Chronic Pancreatitis I: Introduction
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Acute Pancreatitis I: Introduction