Related Experiment Video
Updated: Jul 1, 2026


Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Impulse oscillometry with quantitative computed tomography provides additional clinical information beyond spirometry
Gyuri Kim1, Hyonsoo Joo2, Hyeon-Kyoung Koo3
1School of Mechanical Engineering & Research Institute of Engineering Design & Technology (IEDT), Kyungpook National University, Daegu, Republic of Korea.

Background:
Conventional spirometric indices such as forced expiratory volume in 1 second (FEV1), forced vital capacity (FVC), and its ratio, FEV1/FVC, are commonly used to assess functional alterations in lungs. Quantitative computed tomography (qCT) and impulse oscillometry (IOS) provide additional insights on the traditional metrics. This study aims to investigate the interrelationship among spirometric, oscillometric, and qCT measures in subjects with varying pulmonary function.
Methods:
Sixty-four subjects with variable pulmonary functions were recruited and stratified into four sub-groups (G1-G4) based on spirometric severity defined by FVC and FEV1/FVC. The qCTs at full inspiration and normal expiration enable image registration-based metrics, including the determinant of the Jacobian (Jacobian), the anisotropic deformation index (ADI), and functional small airway disease (fSAD%). We also obtained IOS metrics to measure reactance (X5 through X20), resonant frequency (fres) and reactance area (AX) for respective subjects.
Results:
IOS-based reactances at 10 and 15 Hz (X10 and X15) were significantly more negative in groups with reduced FVC (G2 and 4) than in those with preserved FVC (G1 and 3), whereas resistances did not differ significantly between the sub-groups. The Jacobian and ADI were predominantly decreased in Groups 2 and 4 with FVC<80%. fSAD% was predominantly increased in Groups 3 and 4 with FEV1/FVC<70%. In particular, the X10 was most significantly correlated with Jacobian in the left and right lower lobes.
Conclusion:
The IOS-based reactances with low frequency were significantly associated with spirometry-pulmonary function and CT-based parenchymal lung function metrics. This finding suggests that a combined approach using IOS and CT can provide a better understanding of parenchymal alterations than spirometry alone.


Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:25
Pulmonary Function Tests
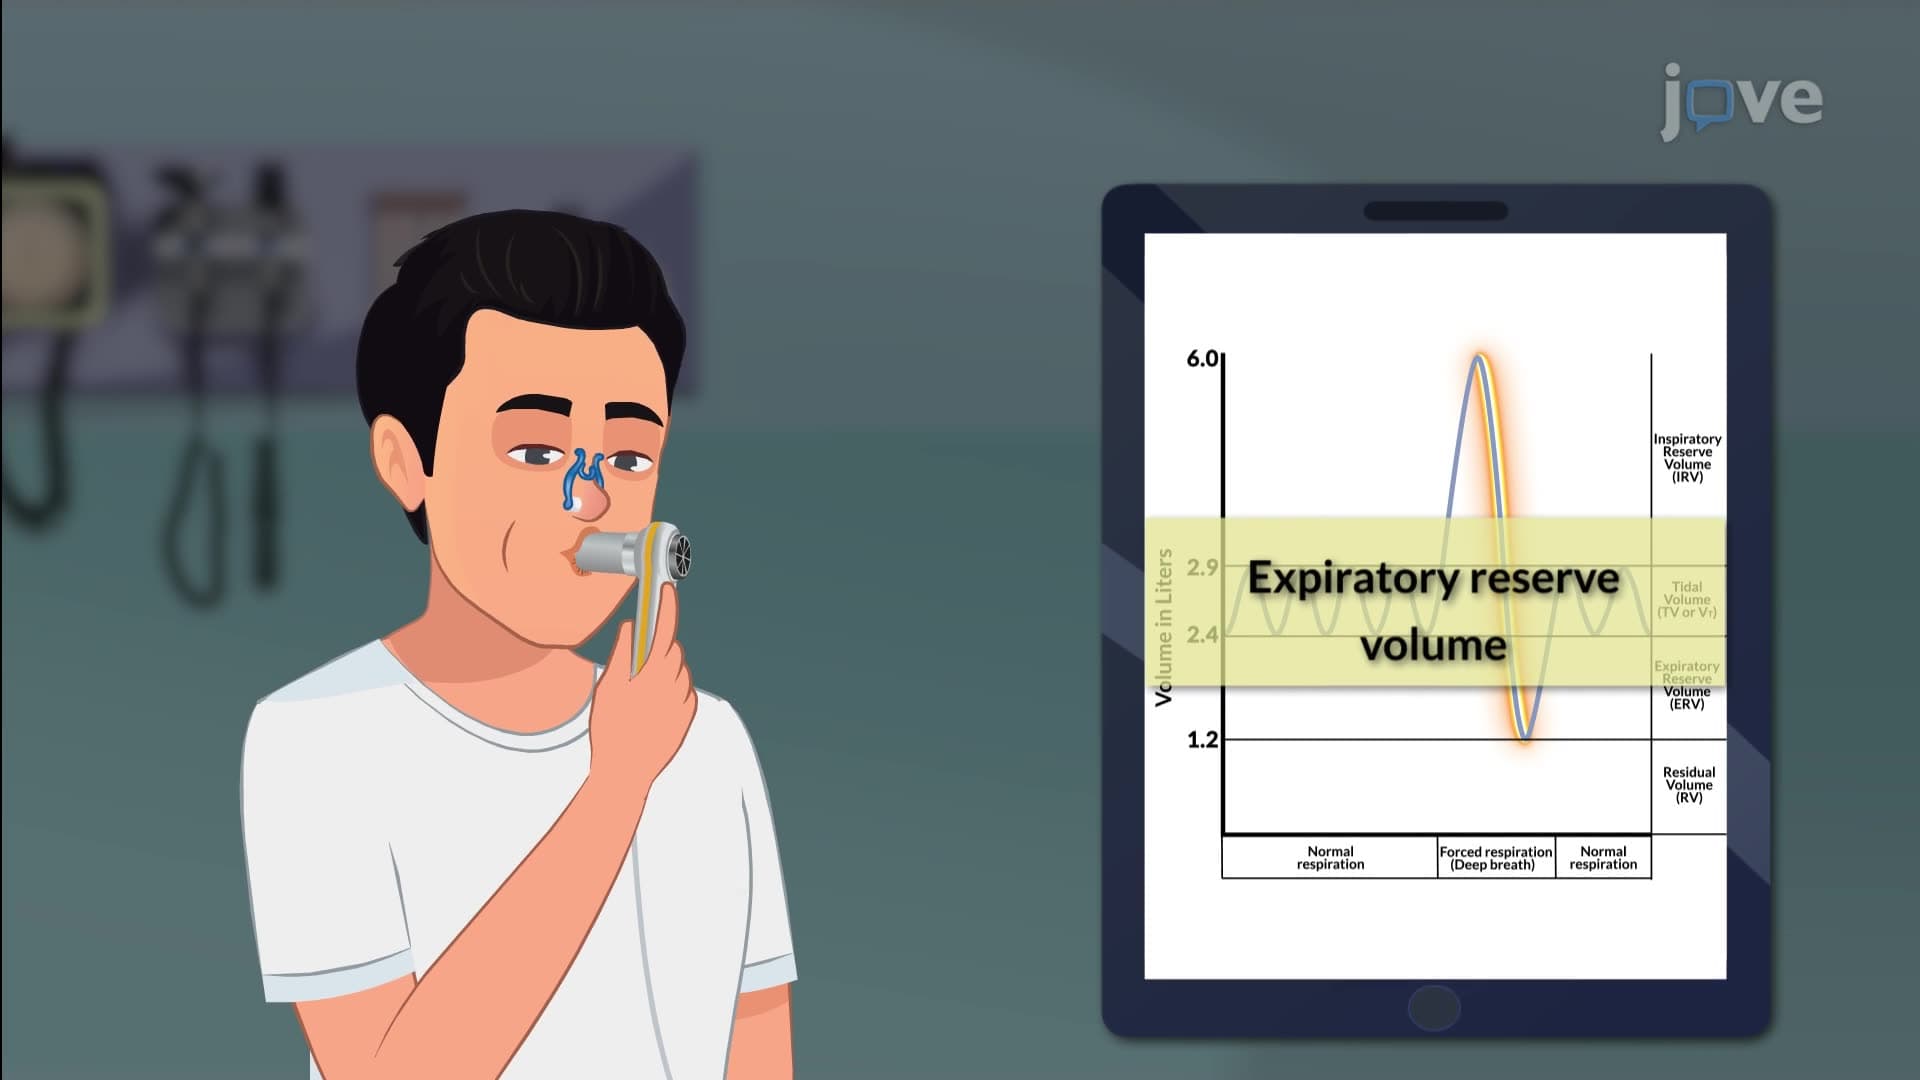
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction