Related Experiment Video
Updated: Jul 1, 2026

Modeling Hypoxia/Reoxygenation Injury in Proximal Tubular Epithelial Cells
Published on: November 21, 2025
Effects of SGLT2I Therapy on Tubular Reabsorption and Tubular Epithelial Stress Injury in Patients With CKD
Ann-Kathrin C Schäfer1, Dennis Pieper1, Bilgin Bayram1
1Department of Nephrology and Rheumatology, University Medical Center Göttingen, Göttingen, Germany.

Rationale & Objective:
Sodium-glucose cotransporter-2 inhibitors (SGLT2I) are a standard of care treatment for chronic kidney disease (CKD). However, the effects of SGLT2I on tubular function and stress are rare.
Study Design:
A monocentric, prospective, observational study.
Setting & Participants:
Patients with CKD who were referred to the outpatient clinic of the Department of Nephrology at Göttingen University Hospital and for whom SGLT2I therapy was indicated as part of standard treatment were prospectively included and treated with SGLT2I in accordance with current guidelines.
Analytical Approach:
Urine samples were collected, and the levels of urinary α1-microglobulin (uα-1-MG), urinary Dickkopf-3 (uDKK3), and urinary albumin creatinine ratio (UACR), each normalized to urinary creatinine, were measured at baseline and after 6 months of therapy.
Results:
Total of 57 patients were included. The mean age was 66.4 ± 12.4 years; 42.1% were female. At baseline, mean estimated glomerular filtration rate was 42.0 ± 15.3 mL/min/1.73m2. Within 6 months, the mean estimated glomerular filtration rate decreased by -2.1 ± 7.6 mL/min/1.73 m2 (P = 0.04). While overall patients, UACR (P = 0.23) and uDKK3 (P = 0.87) remained unchanged, there was a significant increase in median uα-1-MG within 6-months (+9.7 mg/g creatinine [IQR 1.0-22.2]; P < 0.001). Although patients with A3 albuminuria (n = 14) showed only a numerical increase of median uα-1-MG level (+4.6 mg/g creatinine [IQR -7.1 to 20.8]; P = 0.30), there was a significant increase of median uα-1-MG in stage A1 (n=22, +11.5 mg/g creatinine [IQR 3.8-23.2]; P < 0.001) and A2 patients (n = 21, +7.2 mg/g creatinine [IQR 0.7-30.8]; P = 0.006).
Limitations:
The small sample size, lack of a control group, and the short follow-up duration may restrict the findings.
Conclusions:
This study demonstrates an increase in uα-1-MG during SGLT2I treatment in patients with CKD, particularly in UACR stage A1, in which reduction of hyperfiltration is less pronounced. Because uDKK3 as a parameter of tubular damage remained stable, the increase in uα-1-MG may reflect a functional reduction of protein reabsorption and thus reduced intratubular protein overload as a potential nephroprotective effect.
Insights
Sodium-glucose cotransporter-2 inhibitors (SGLT2I) increase urinary α1-microglobulin (uα-1-MG) in chronic kidney disease (CKD) patients. This suggests reduced protein reabsorption, potentially offering a nephroprotective effect by decreasing intratubular protein overload.
Area of Science:
- Nephrology
- Pharmacology
- Biochemistry
Background:
- Sodium-glucose cotransporter-2 inhibitors (SGLT2I) are established treatments for chronic kidney disease (CKD).
- Limited data exist on the specific effects of SGLT2I on tubular function and stress markers in CKD patients.
Purpose of the Study:
- To investigate the impact of SGLT2I on tubular function markers in patients with CKD.
- To assess changes in urinary α1-microglobulin (uα-1-MG), urinary Dickkopf-3 (uDKK3), and urinary albumin creatinine ratio (UACR) during SGLT2I therapy.
Main Methods:
- A prospective, observational study involving 57 CKD patients treated with SGLT2I.
- Urine samples were collected at baseline and after 6 months of therapy.
- Measurements included uα-1-MG, uDKK3, and UACR, all normalized to urinary creatinine.
Main Results:
- A significant increase in median uα-1-MG was observed within 6 months of SGLT2I treatment (P < 0.001).
- No significant changes were noted in overall UACR (P = 0.23) or uDKK3 (P = 0.87).
- The increase in uα-1-MG was particularly pronounced in CKD patients with UACR stage A1 and A2 albuminuria.
Conclusions:
- SGLT2I treatment in CKD patients leads to increased uα-1-MG.
- Stable uDKK3 levels suggest the observed uα-1-MG increase may reflect reduced tubular damage.
- This elevation in uα-1-MG might indicate a functional reduction in protein reabsorption, potentially contributing to a nephroprotective effect through decreased intratubular protein overload.

Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:22
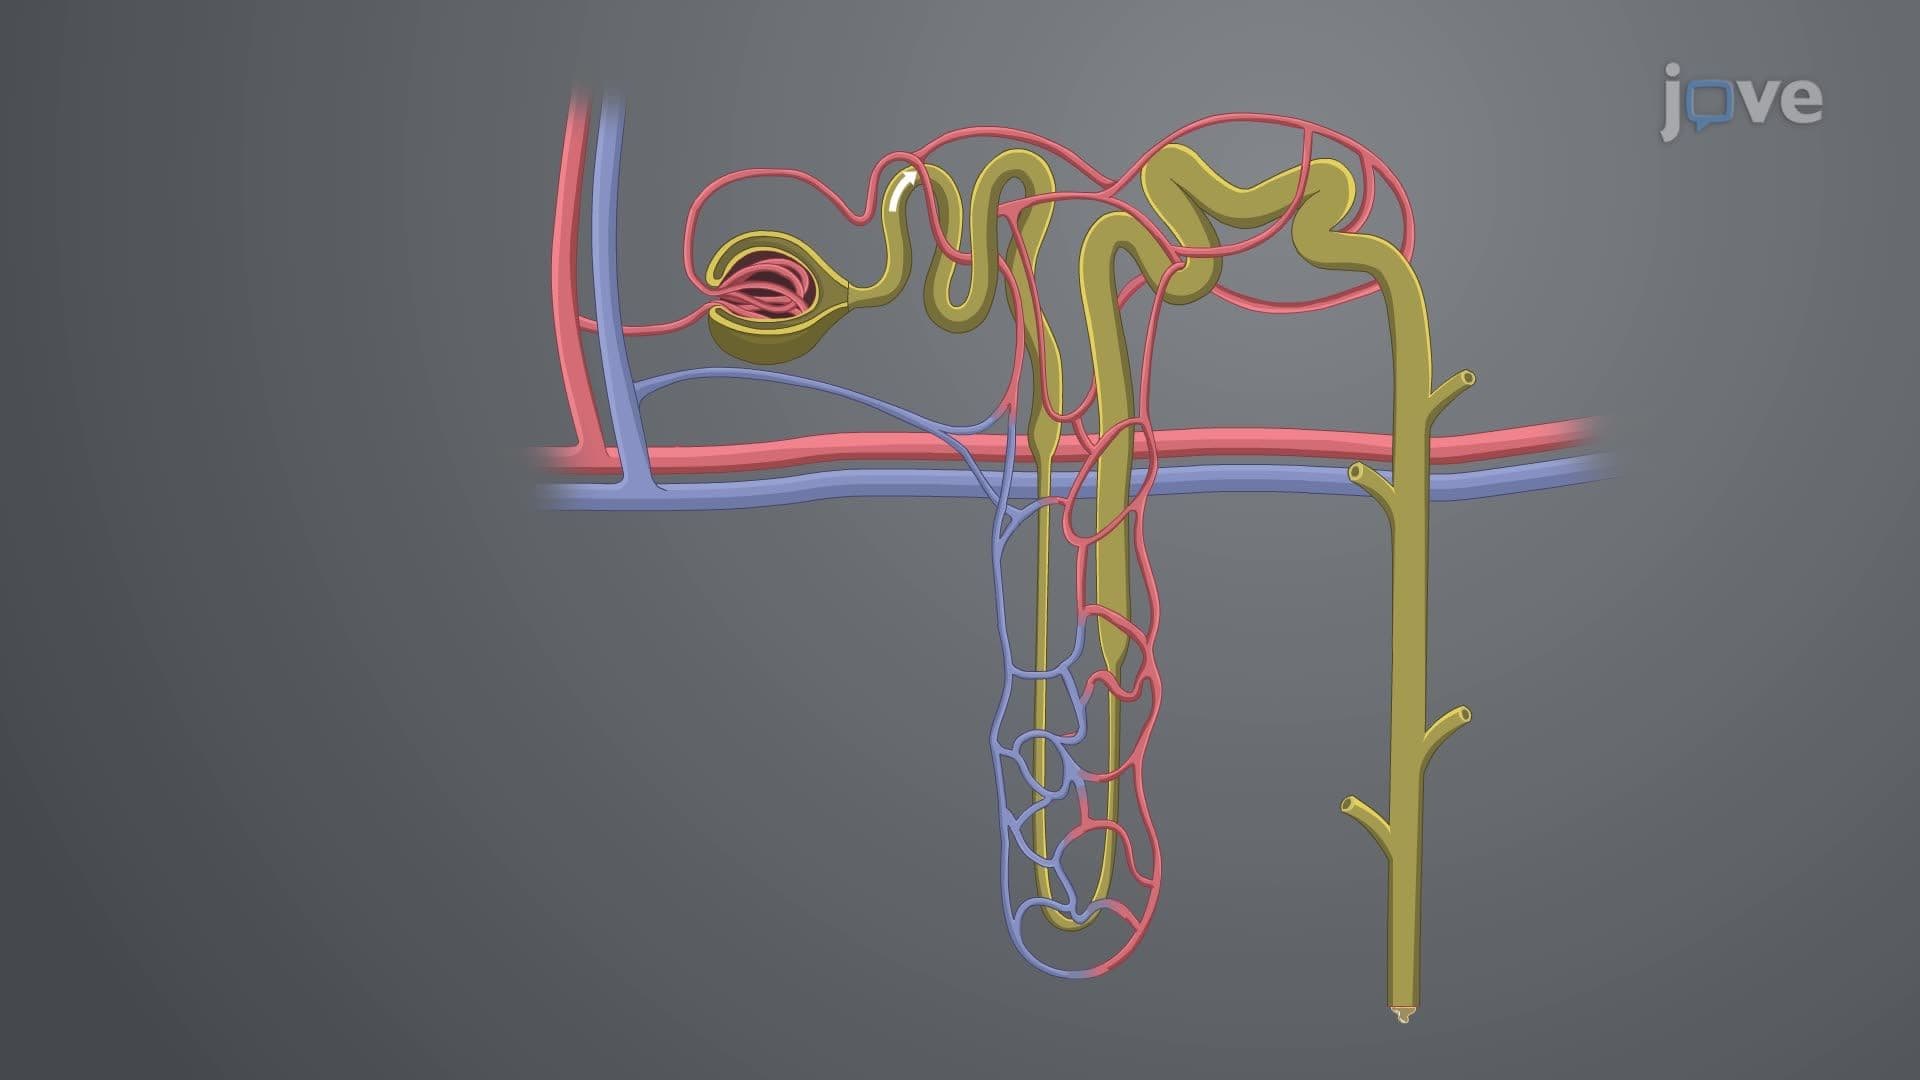
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:29
Acute Kidney Injury II: Pathophysiology