Related Experiment Video
Updated: Jul 2, 2026
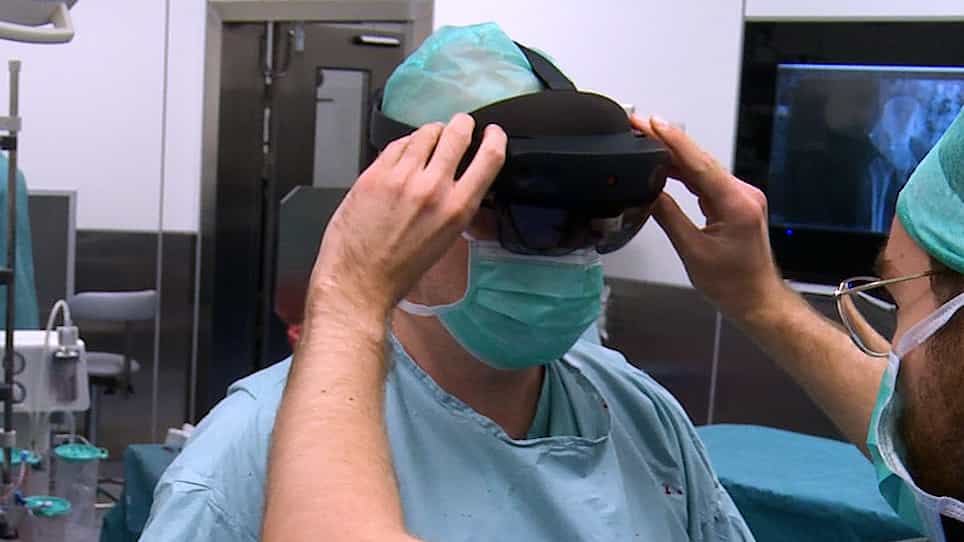
The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Lower septic revision rates following cementless compared with cemented robotic-assisted total knee arthroplasty
Carmelo Burgio1, Harold I Salmons1, Karlos E Zepeda1
1Department of Orthopaedic Surgery, Adult Reconstruction and Joint Replacement Service, Hospital for Special Surgery, New York, New York, USA.

Aims:
The choice of fixation for total knee arthroplasty (TKA) remains controversial. Cementless designs incorporating highly porous titanium surfaces may achieve durable biological fixation and mitigate cement-related complications. However, little has been written comparing the methods of fixation for robotic-assisted (RA) TKA. The aim of this study was to compare the implant survival and complication rates between cemented and cementless RA-TKA using a single robotic system and uniform implant design.
Methods:
This retrospective review involved 2,647 consecutive primary RA-TKAs undertaken by 27 surgeons at a high-volume academic centre, between 2016 and 2024, using a single CT-based robotic platform and implant design (Triathlon). Patients aged > 18 years with primary osteoarthritis and at least one year of follow-up were included. The method of fixation was determined by the operating surgeon. This resulted in 1,289 cemented and 1,358 cementless RA-TKAs. The mean follow-up was 3.5 years (SD 2.1). Outcomes included Kaplan-Meier survival free from revision (overall, septic, and aseptic), all-cause further surgery, and 90-day readmissions and nonoperative complications. Multivariable Cox regression analysis adjusted for age, BMI, sex, race, ethnicity, and operating time was performed to identify independent predictors.
Results:
The five-year revision-free survival was 98.0% (95% CI 97.1 to 98.9) and 98.5% (95% CI 97.4 to 99.6) for cemented and cementless fixation, respectively (p = 0.137, log-rank test). Cementless fixation was associated with a significantly decreased risk of septic revision (hazard ratio 0.21 (95% CI 0.03 to 0.71); p = 0.021), whereas there were no differences between the groups for aseptic revision. The five-year survival free from any reoperation was 96.6% (95% CI 95.5 to 97.7) in the cemented group and 97.1% (95% CI 95.9 to 98.4) in the cementless group (p = 0.472, log-rank test). The most common indication for reoperation was stiffness, followed by periprosthetic joint infection. The 90-day readmission and nonoperative complication rates were similar between the groups (p = 0.999 and p = 0.290, respectively).
Conclusion:
Cementless RA-TKA showed excellent five-year survival with a significantly decreased risk of septic revision compared with cemented RA-TKA. These findings suggest a decreased infection-related risk of failure with cementless fixation, without compromising the short-term implant survival.