Related Experiment Video
Updated: Jul 2, 2026
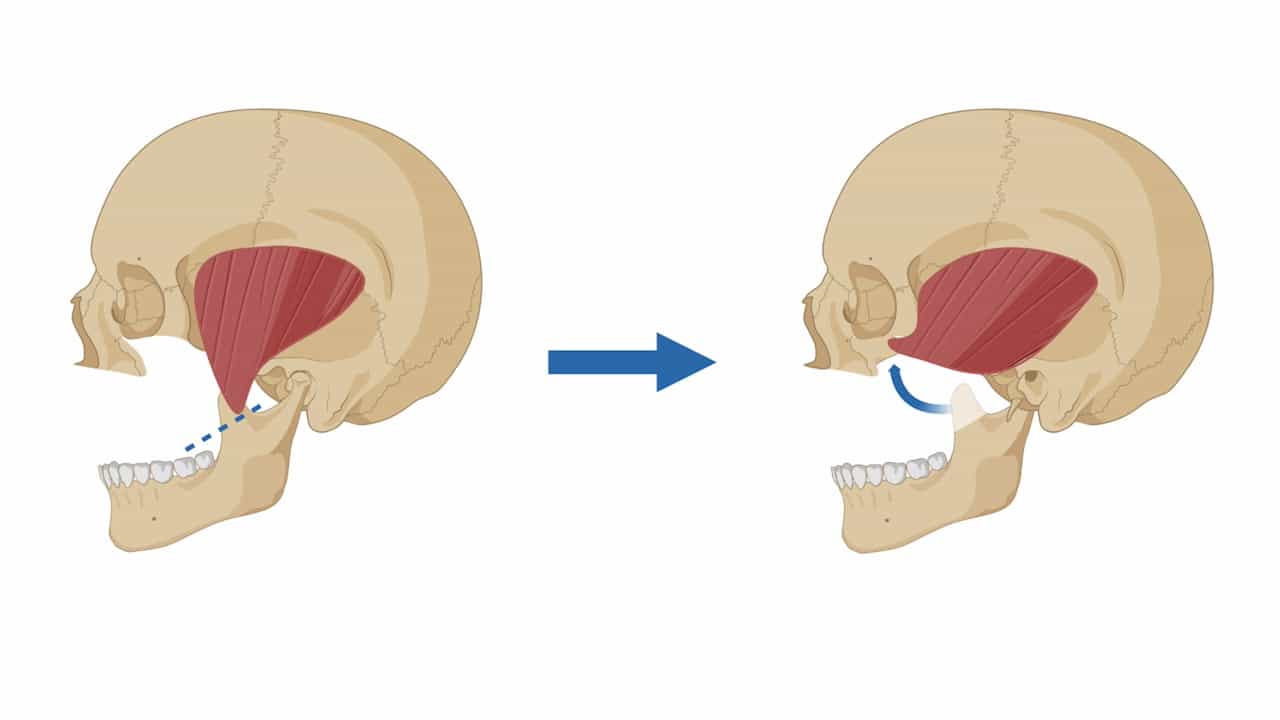

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
OOM-ORL-ROOF Composite Flap Suspension (ORRCS) to the Lateral Orbital Thickening for Lateral Hooding
Ying Lv1, Xi Da Ma2, Hong Jin Sui3
1Shenzhen Yestar Medical Aesthetic Hospital, Shenzhen, China.

Background:
Lateral hooding of the upper eyelid is a common yet frequently undertreated aspect of periorbital aging in East Asians. This study aimed to investigate the roles of the orbicularis oculi muscle (OOM), retro-orbicularis oculi fat (ROOF), orbicularis retaining ligament (ORL), and lateral orbital thickening (LOT) in the pathogenesis and to evaluate the novel OOM-ORL-ROOF composite suspension (ORRCS) technique.
Methods:
Anatomical analyses were conducted on 6 cadaveric heads and 18 plastinated specimens. Clinical outcomes of the ORRCS procedure were retrospectively reviewed in 85 East Asian patients with lateral dermatochalasis (LDC grade ≥1). Assessments included LDC grade, lateral canthal tilt, brow position, complications, and patient satisfaction preoperatively and at 6 and 12 months postoperatively.
Results:
Anatomically, the age-related descent of the continuous OOM-ORL-ROOF composite is primarily due to the attenuation of its deep retaining structures, the ORL-LOT retaining complex. Clinically, ORRCS significantly improved the mean LDC grade from 2.24±0.77 to 0.40±0.49 (p<0.001) and increased lateral canthal tilt by ~5° (from 3.0° ± 1.13° to 8.0° ± 1.25°). Brow position remained stable ( p >0.05). Scars were inconspicuous, with no major complications and high patient satisfaction (4.7/5).
Conclusions:
Lateral hooding primarily results from the descent of the OOM-ORL-ROOF composite unit due to the attenuation of the deep ORL-LOT retaining complex. The ORRCS technique corrects this deformity by re-suspending the complex to the robust LOT, providing a promising anatomy-guided deep-plane approach with favorable early outcomes in this cohort while restoring a natural contour and preserving brow dynamics.
Level Of Evidence Iii:
This journal requires that authors assign a level of evidence to each article. For a full description of these Evidence-Based Medicine ratings, please refer to the Table of Contents or the online Instructions to Authors www.springer.com/00266 .

Related Concept Videos
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:17
Accessory Structures of the Eye
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:25
Suctioning the Oropharyngeal Airway
After assembling the equipment, the nurse should practice hand hygiene and don appropriate PPE according to infection control guidelines to avoid the...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...