Related Experiment Video
Updated: Jul 2, 2026


Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
Catheter architecture as a determinant of cerebrospinal fluid flow in pediatric hydrocephalus
Christopher W Roberts1, Brandon G Rocque2, Leopold Arko Iv3
1Department of Chemical Engineering and Material Science, Wayne State University, 5050 Anthony Wayne Dr, Detroit, MI, 48202, USA.

Insights
Ventricular catheter design, patient anatomy, and placement critically impact cerebrospinal fluid (CSF) shunt function in pediatric hydrocephalus. Optimizing these factors is key to preventing catheter obstruction and improving shunt reliability.
Area of Science:
- Biomedical Engineering
- Fluid Dynamics
- Pediatric Neurosurgery
Background:
- Cerebral ventricular catheters (VCs) are crucial for pediatric hydrocephalus treatment but frequently fail due to obstruction.
- Existing VCs show limited long-term reliability despite various designs.
- Understanding factors influencing CSF drainage is vital for improving shunt system performance.
Purpose of the Study:
- To investigate the interplay between ventricular catheter design, patient-specific ventricular anatomy, and surgical placement on cerebrospinal fluid (CSF) drainage patterns.
- To identify design features and placement strategies that minimize obstruction risk.
Main Methods:
- Three patient-specific hydrocephalic ventricles were modeled from MRI data.
- Four distinct ventricular catheter designs were reverse-engineered.
- Virtual implantation into lateral ventricles with frontal, parietal, and occipital placements.
- Computational fluid dynamics (CFD) simulations quantified CSF flow rates through catheter drainage holes.
Main Results:
- Occipital placement consistently led to dominant inflow near the catheter valve.
- Frontal and parietal placements showed design-dependent flow patterns.
- In most cases, segments near the valve handled 65-82% of CSF inflow.
- Smaller ventricles and specific catheter designs caused valve-adjacent segments to be excluded, redistributing flow to tip-adjacent segments (up to 99.5%).
- Shorter perforated lengths and denser drainage holes improved functional segment activity across geometries.
Conclusions:
- Ventricular catheter drainage is a complex interaction of catheter architecture, ventricular morphology, and surgical placement, not solely catheter geometry.
- Catheter designs with shorter, denser perforations are more adaptable to varying ventricular anatomies.
- Optimized placement and design are essential for reliable CSF shunt function in pediatric hydrocephalus.
Abstract:
Cerebral ventricular catheters (VCs) remain the critical but failure-prone component of cerebrospinal fluid (CSF) shunt systems for pediatric hydrocephalus, with proximal obstruction accounting for most malfunctions. Several catheter geometries have been introduced to the market in the US alone, yet none demonstrate long-term reliability. This study investigates how catheter design interacts with patient-specific ventricular anatomy and surgical placement to influence CSF drainage patterns. Three patient-specific hydrocephalic ventricles were modeled from MRI scans, with FOHR values of 0.45, 0.30, and 0.29 and corresponding ventricular volumes of 167.5 (enlarged), 12.5 (moderate), and 20.6 mL (small). Four ventricular catheters with varying architectures from our institutional biobank were reverse engineered using confocal microscopy. Catheters were virtually implanted into the lateral ventricles under frontal, parietal, and occipital placements. Computational fluid dynamic simulations were performed, and mass flow rates were quantified across drainage holes grouped into longitudinal segments. Boundary conditions consisted of a constant CSF efflux rate of 0.35 mL/min applied uniformly across all configurations and a continuous pressure outlet at the proximal catheter outlet, representing valveless drainage. Occipital placement consistently produced valve adjacent dominant inflow across catheter designs, whereas frontal and parietal placements exhibited design-specific flow behaviors when segmental inflow through the catheter drainage holes was measured. In most configurations, segments nearest the catheter valve captured the majority of inflow, accounting for 65-82% of total CSF entry. In frontal placements, smaller ventricular geometries caused valve-adjacent segments in several catheter designs to extend outside the ventricular cavity. As a result, inflow was redistributed toward the remaining tip-adjacent segments, with up to 99.5% of total flow entering through these segments when valve-adjacent holes were excluded. Catheter designs with shorter perforated lengths and more closely spaced drainage holes maintained a greater number of functionally active segments across ventricular geometries, whereas longer perforated spans were more susceptible to anatomical exclusion. These findings demonstrate that ventricular catheter drainage is governed not by catheter geometry alone, but by the interaction between catheter architecture, ventricular morphology, and surgical placement.

Related Concept Videos
 01:21
Cerebrospinal Fluid
CSF Production
CSF is produced mainly in the choroid plexus, a network of capillaries and ependymal cells located within the ventricular system of the brain.
 01:14
Increased Intracranial Pressure l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:18
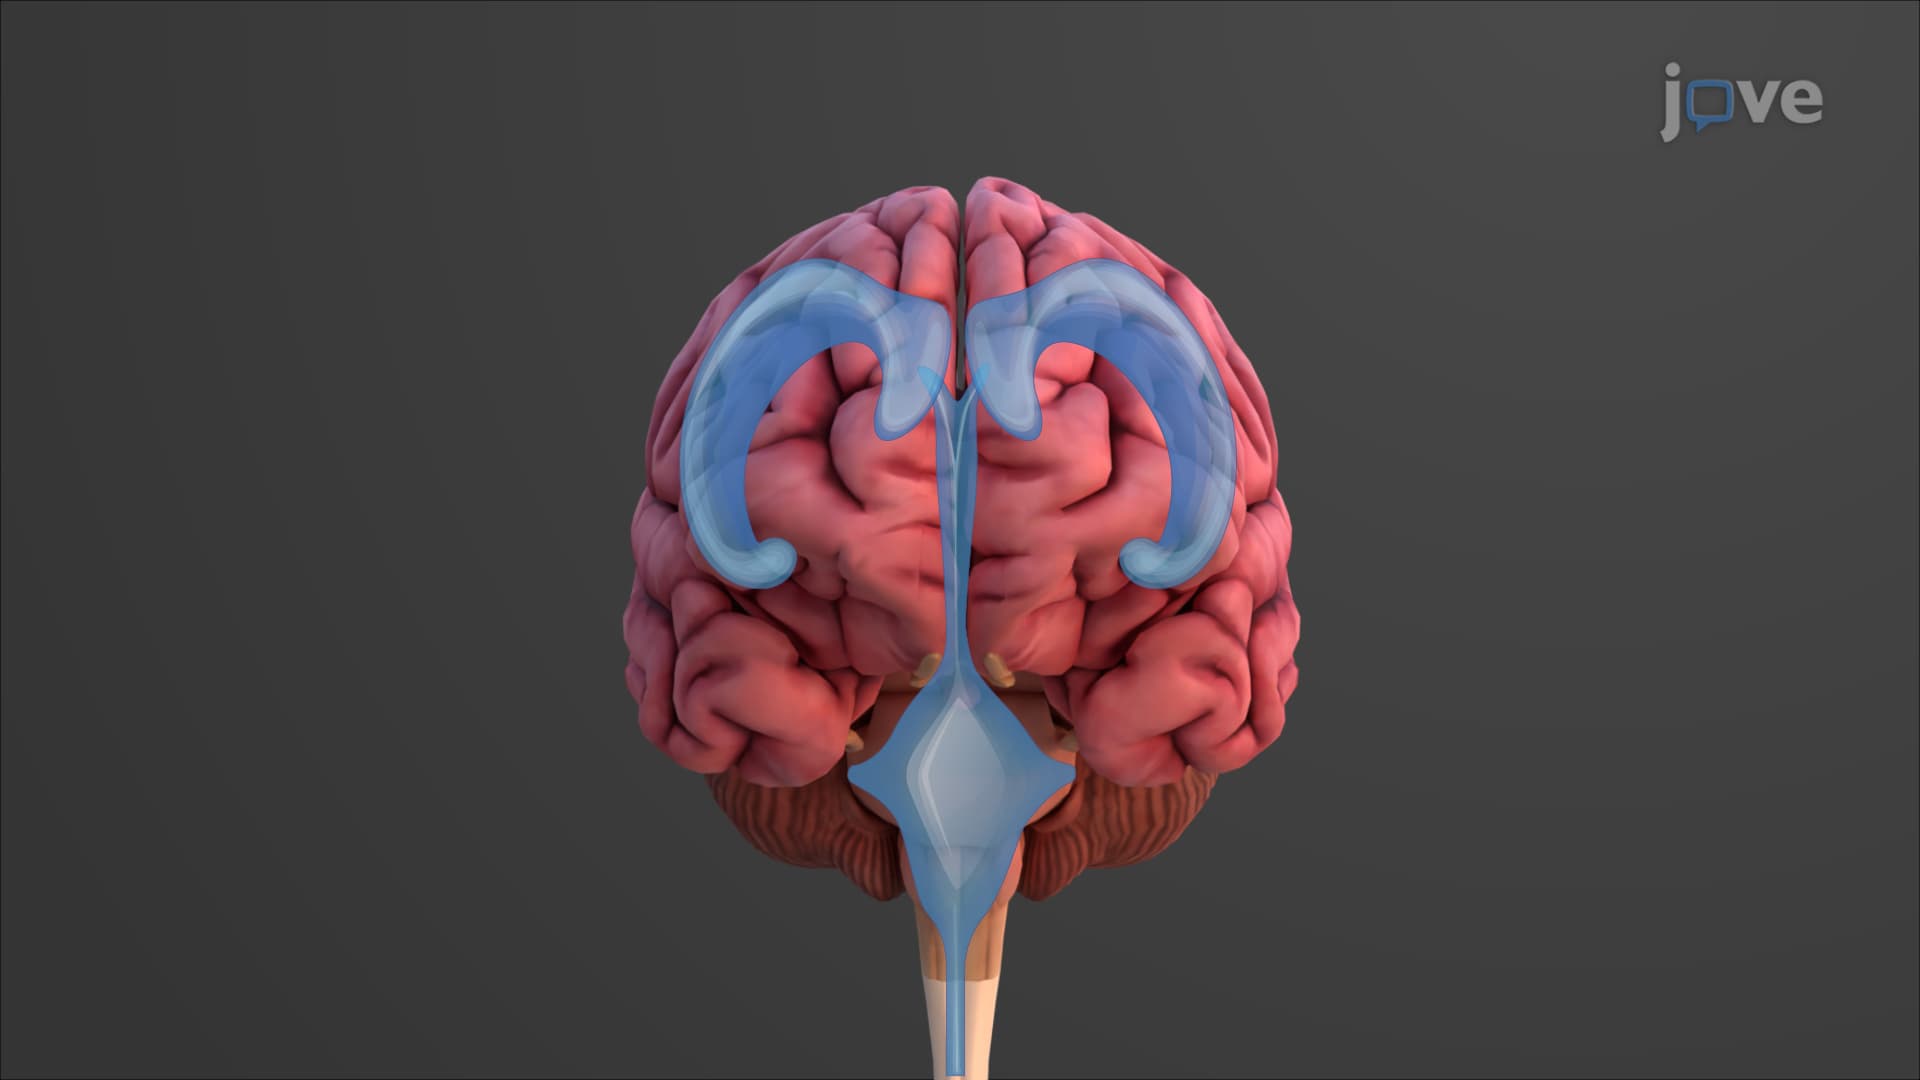
Anatomy of the Brain: Ventricles