Related Experiment Video
Updated: Jul 2, 2026
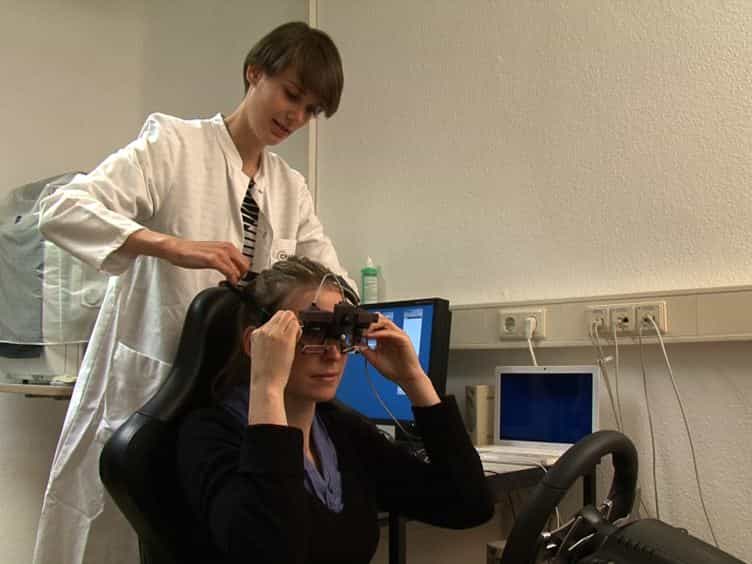

Driving Simulation in the Clinic: Testing Visual Exploratory Behavior in Daily Life Activities in Patients with Visual Field Defects
Published on: September 18, 2012
What drives family physicians to rural practice? A discrete choice experiment in Vietnam
Cam Anh Thi Pham1, Nguyen Quynh Trang Le2, Dohyeong Kim3,4
1FTU Research Lab (FRL), School of Economics and International Business, Foreign Trade University, 91 Chua Lang Street, Lang Thuong, Dong Da District, Viet Nam.

Abstract:
Despite commune health stations serving as the backbone of Vietnam's primary healthcare, severe physician maldistribution persists. To explore factors influencing the recruitment and retention of family physicians in rural areas, we conducted a discrete choice experiment among 315 family physicians in Vietnam. Mixed logit regression was used to estimate the relative importance of individual characteristics and key job attributes, which included income change, career promotion, living condition, and government support for private clinics. Our findings indicate that a 50% increase in salary has the most significant influence on rural job uptake for key subgroups, including those under 50, assistant doctors, and those with prior rural exposure. However, the marginal utility of financial incentives diminishes rapidly beyond a specific threshold. Subgroup analysis further reveals heterogeneous preferences: physicians who transitioned from commune health stations to higher-level facilities, and those working in primary health care areas, respond more strongly to non-financial incentives such as career promotion and private practice support than to additional income increases. Physicians would forgo 48.36% of their salary to secure an urban posting, yet would accept a rural position if offered expedited promotion or private practice support, each valued at approximately 38% of monthly income. Achieving sustainable rural deployment therefore requires differentiated rather than uniform intervention: moderate salary increases for younger and rural-exposed physicians, combined with accelerated promotion pathways and private practice facilitation for those in primary health care and higher-level facilities. Translating stated preferences into actual rural uptake ultimately hinges on government credibility in delivering promised benefits.
Related Concept Videos
 01:30
Primary Healthcare Services
In 1978, international leaders convened in Alma-Ata, Kazakhstan, for what would be a pivotal event in global health. The Alma-Ata Declaration was the first to call...
 01:26
Methods Of Healthcare Delivery System
Managed Care System:
The managed care system is designed to control the cost while maintaining the quality of care. The patient's care from admission to discharge is planned by the primary care provider or the case manager, also known as the gatekeeper. In a managed care system, the number of care providers is limited...
 01:14
Decision Making: Traditional Method
First, a specific claim about the population parameter is decided based on the research question and is stated in a simple form. Further, an opposing statement to this claim is also stated. These statements can act as null and alternative hypotheses, out of which a null hypothesis would be a...
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:11
Secondary Healthcare System
 01:29
Issues And Trends In Healthcare Delivery System
Cost Containment
Payment for healthcare services has historically promoted adoption of costly and often unnecessary or inefficient...