Related Experiment Video
Updated: Jul 2, 2026


Fecal Glucocorticoid Analysis: Non-invasive Adrenal Monitoring in Equids
Published on: April 25, 2016
Etomidate in severe hypercortisolism: early cortisol kinetics and clinical outcomes in a real-world cohort
Vivek Jha1, Tushar Bhadada2, Amal Shaharyar1
1Department of Endocrinology, Postgraduate Institute of Medical Education and Research (PGIMER), Chandigarh, India.

Purpose:
Severe hypercortisolism is a life-threatening endocrine emergency requiring rapid cortisol reduction. Oral steroidogenesis inhibitors may be limited in critically ill patients due to delayed onset, impaired absorption, and toxicity. Intravenous etomidate enables rapid, titratable suppression of cortisol synthesis, but data on early treatment response and real-world safety remain limited.
Methods:
We conducted a retrospective study of consecutive patients with severe endogenous hypercortisolism treated with intravenous etomidate at a tertiary care centre over a 3-year period. Serum cortisol was measured at baseline and at 12 and 24 h to assess early response. Biochemical control was defined as serum cortisol < 500 nmol/L (< 18.1 µg/dL). Clinical, biochemical, and safety outcomes were analysed.
Results:
Ten patients [median baseline cortisol 1285 nmol/L (46.6 µg/dL)] received etomidate infusion. Serum cortisol declined early, with median reductions of 45% at 12 h and 58.5% at 24 h. Biochemical control was achieved within 24 h in 80% of patients. Response categories included rapid (30%), intermediate (50%), and delayed (20%). Patients with < 25% cortisol reduction at 12 h tended to have delayed biochemical control. Serum potassium improved during treatment and normalized before discontinuation of infusion in all patients with available serial data, while clinical stabilization was achieved in 90%. Etomidate was well tolerated; one death due to sepsis was not related to therapy.
Conclusions:
In this real-world cohort of patients with severe hypercortisolism, low-dose intravenous etomidate was associated with early cortisol reduction and clinically useful biochemical control in most patients. Early cortisol trajectories may help guide dose titration, but these findings should be interpreted as descriptive and hypothesis-generating because of the small sample size and retrospective design.
Related Concept Videos
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:31
Hormones of the Adrenal Glands
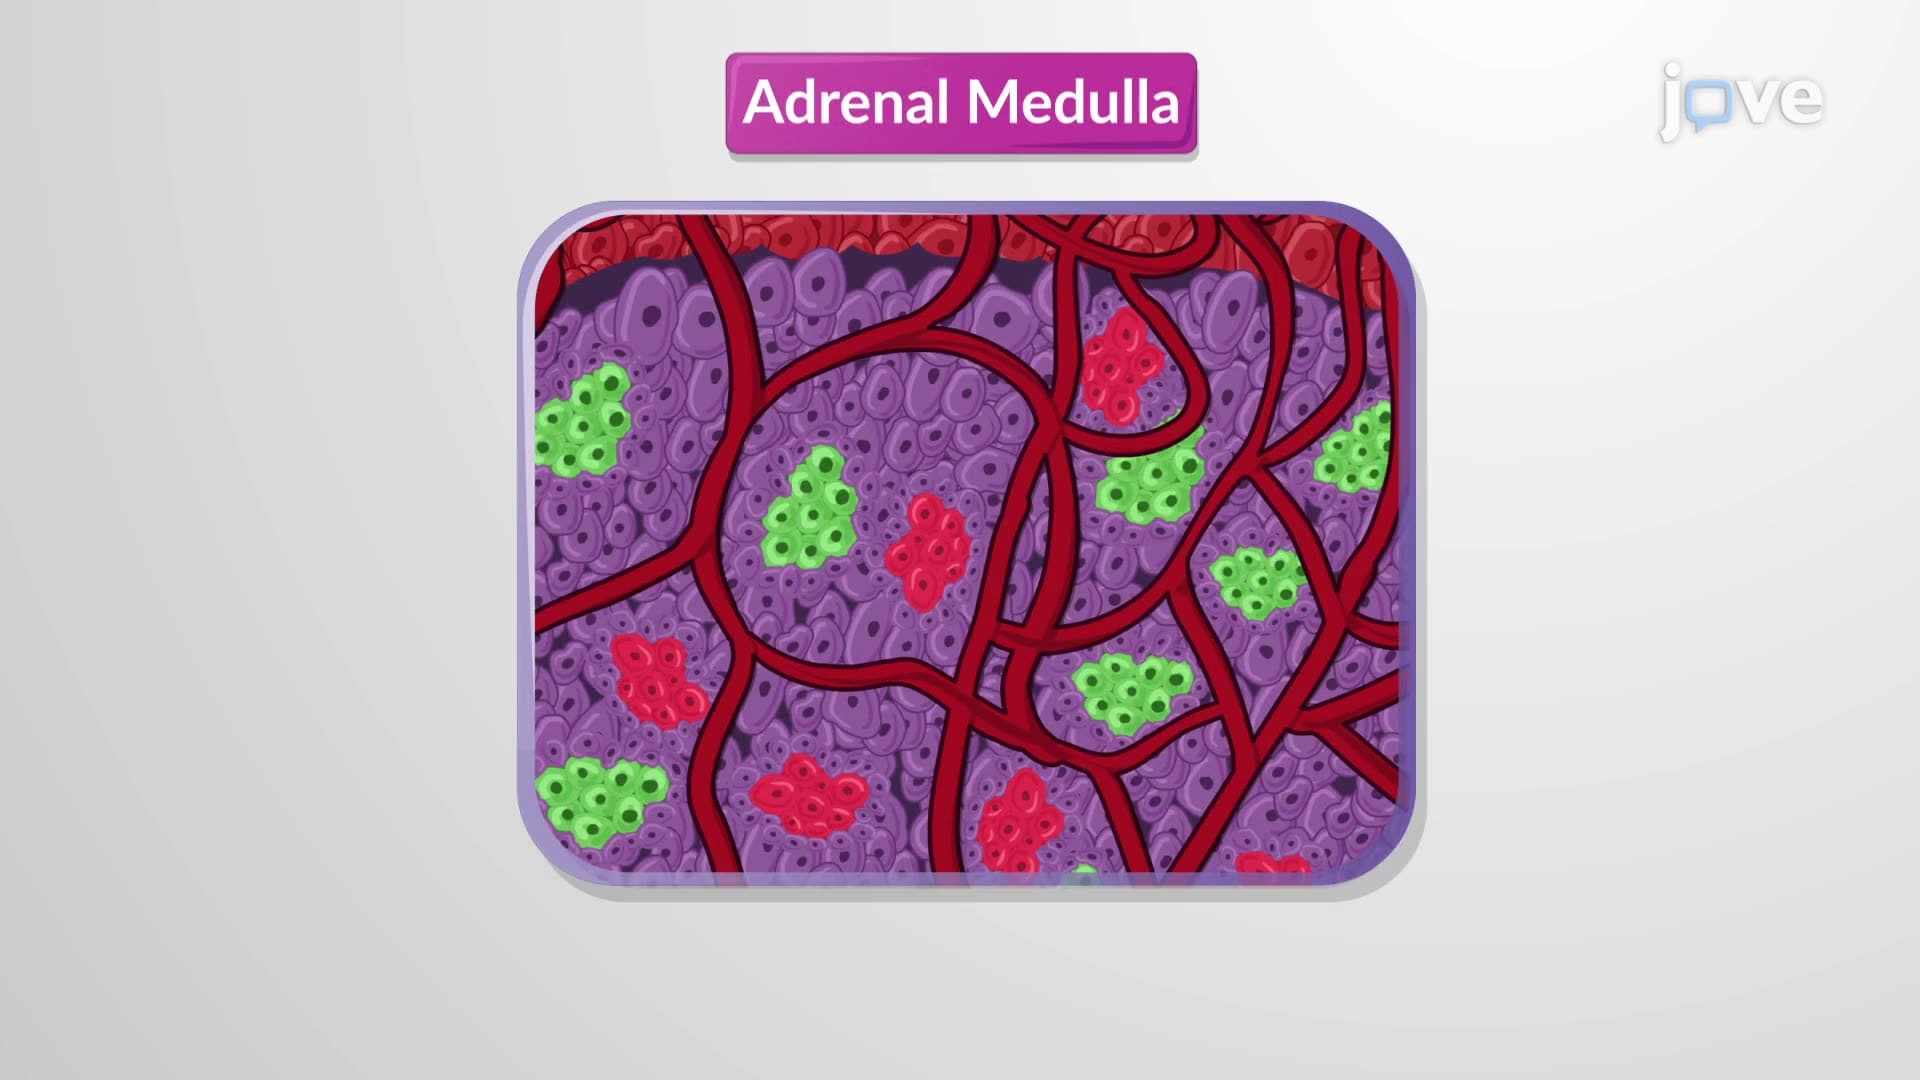
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...