Related Experiment Video
Updated: Jul 2, 2026
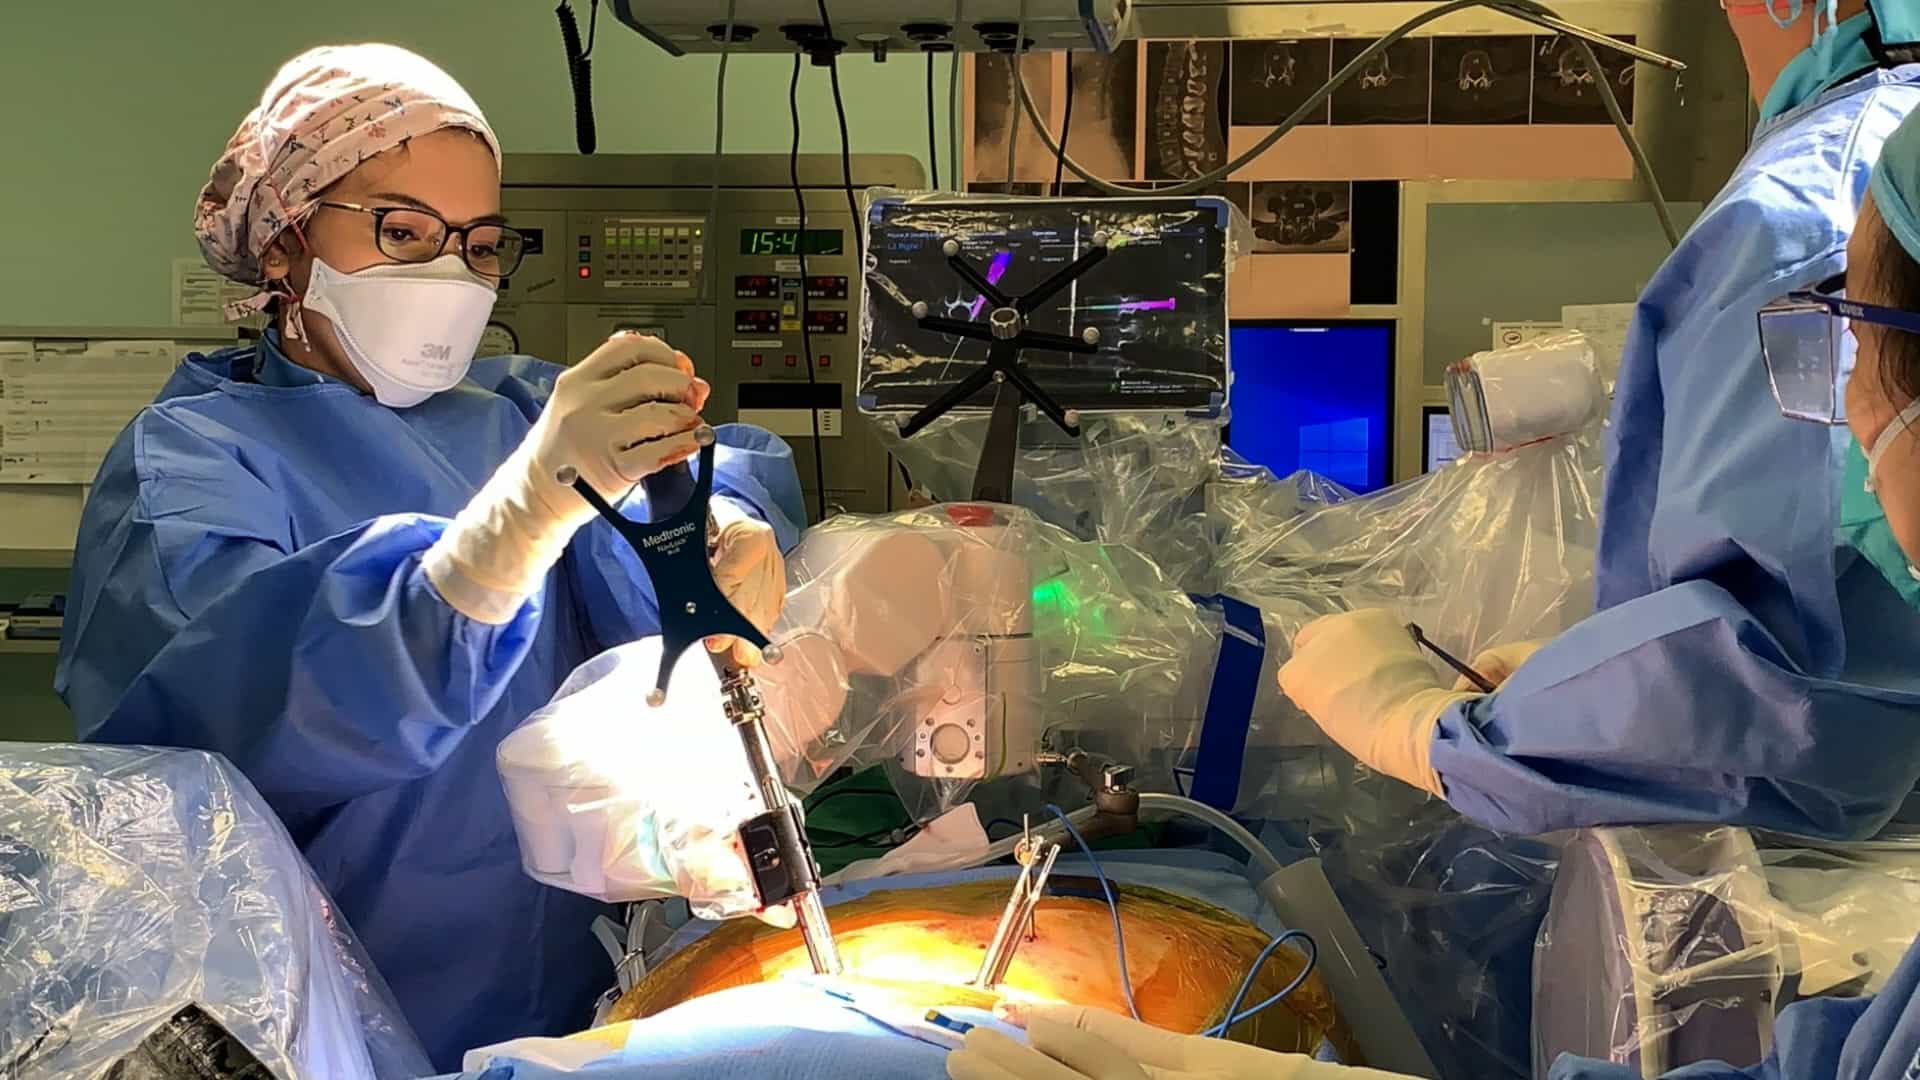

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
[Lumbar disc herniation]
Achim Benditz1, Philipp Koehl2, Mohamed Mahmoud3
1Klinik für Orthopädie und Unfallchirurgie, Sektion für Orthopädie und Wirbelsäulenchirurgie, Klinikum Fichtelgebirge, Schillerhain 1-8, 95615, Marktredwitz, Deutschland. a.benditz@klinikum-fichtelgebirge.de.

Abstract:
The annual prevalence of lumbar disc herniation (LDH) in western industrialized countries averages between 1% and 2.5% but shows a clear age dependency with a peak between the ages of 30 and 50 years. The medical history and physical examination are the most important parts of the examination, with attention being paid to so-called red flags that trigger further imaging. Most LDH can be successfully treated conservatively and tend to regress over time. It is not imaging but clinical symptoms that determine whether surgery is indicated. Patients with severe motor deficits (Medical Research Council, MRC < 2) benefit most from early surgical intervention within the first 48-72 h. Approximately 1-1.5% of patients develop acute conus/cauda symptoms, representing an absolute spinal surgical emergency. After confirmation of the diagnosis, surgical decompression should be performed without delay; decompression after more than 48 h is associated with poorer functional outcomes. Minimally invasive endoscopic discectomy shows identical results to conventional surgical techniques for LDH in terms of pain relief, functional improvement, safety and recurrence rate.
Related Concept Videos
 01:29
Herniated Intervertebral Disc l: Introduction
 01:23
Degenerative Disc Disease ll: Pathophysiology
 01:27
Degenerative Disc Disease I: Introduction