Related Experiment Video
Updated: Jul 3, 2026
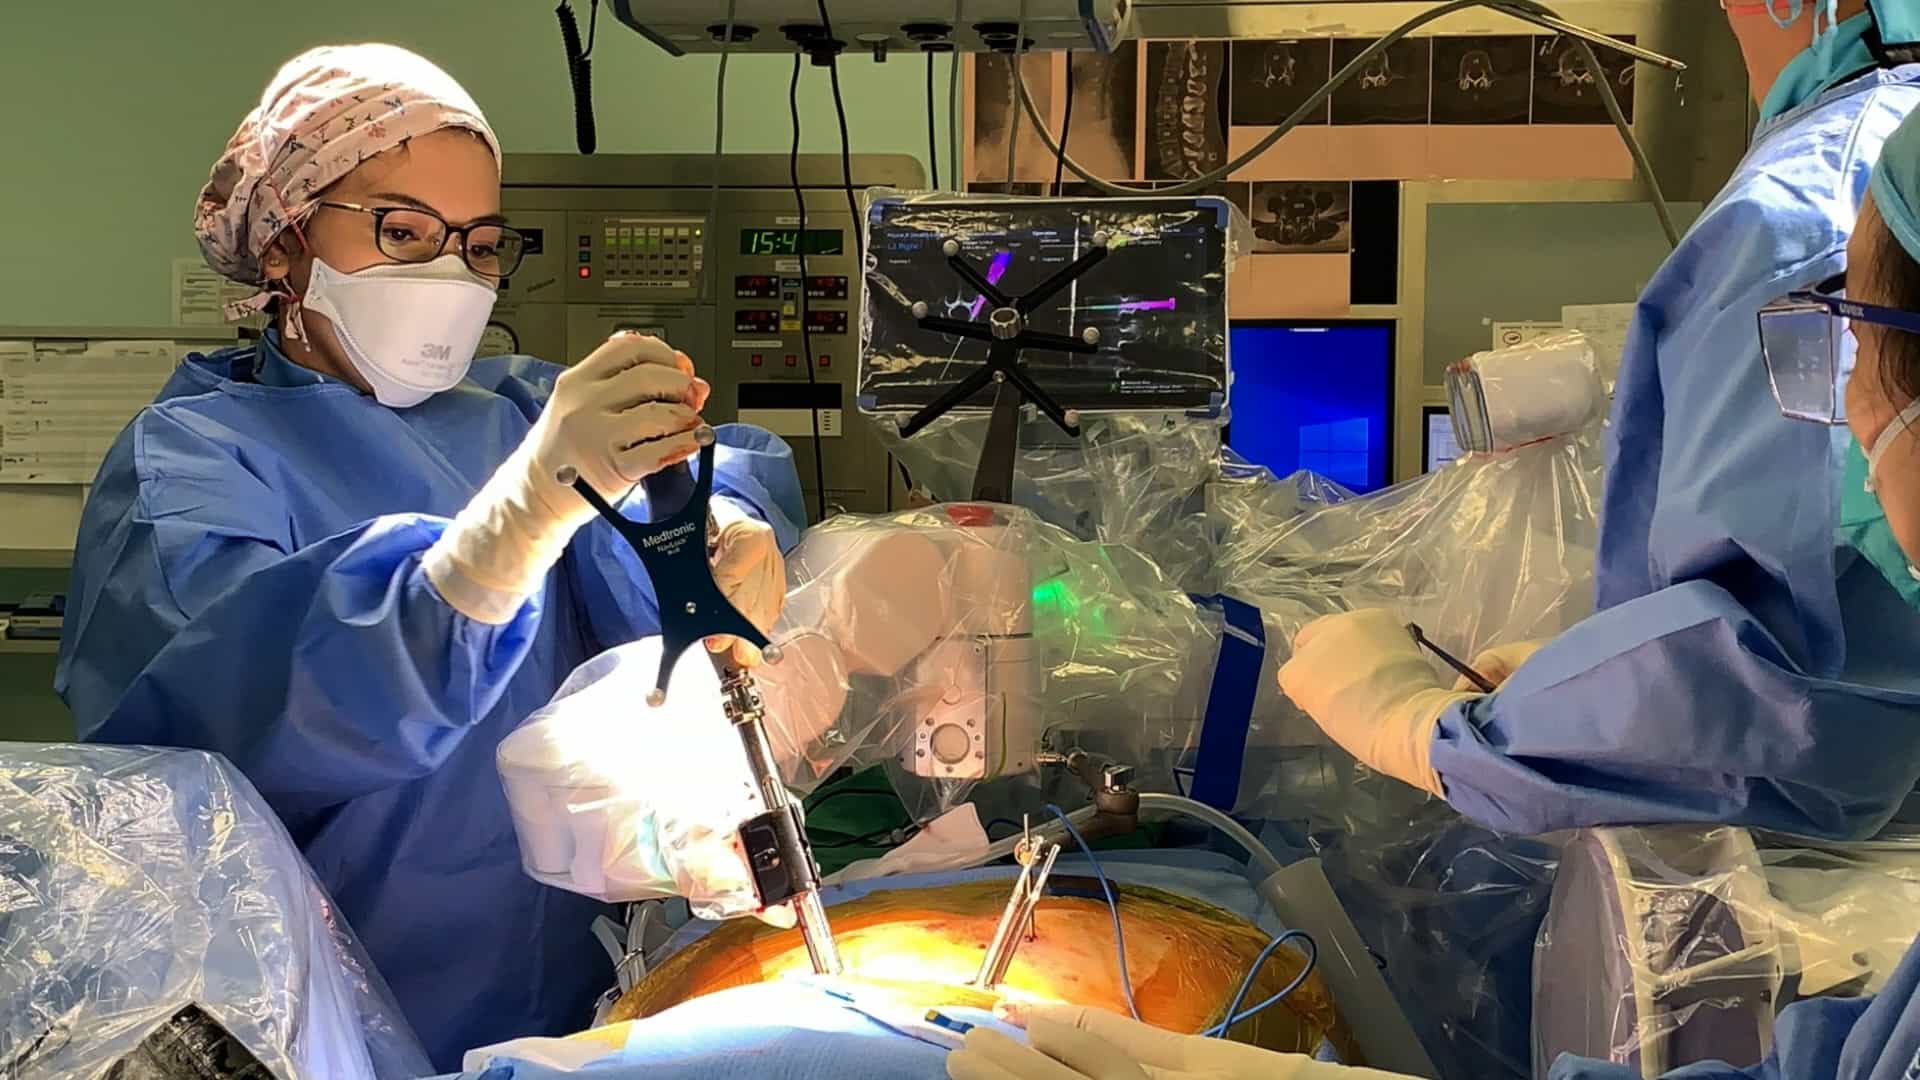

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Outcomes after cervical disc replacement compared with anterior cervical discectomy and fusion at medium- to
Omar Sbaih1, Mark Miller2, Matthew Meade3
11Department of Neurological Surgery, Georgetown University Medical School, Washington, DC.

Objective:
Cervical disc replacement (CDR) is an emerging alternative to arthrodesis for the treatment of degenerative cervical disc disease. The current surgical standard of care, anterior cervical discectomy and fusion (ACDF), allows for adequate decompression with good outcomes; however, this alters biomechanical stability and can eventually lead to adjacent segment disease and reoperation. By preserving motion at the pathological level, CDR might reduce the development of adjacent segment disease and the associated morbidity of reoperation. The aim of this study was to evaluate long-term functional outcomes with CDR compared with ACDF using a large federated electronic health record network.
Methods:
The TriNetX database was queried for all patients ≥ 18 years of age who underwent CDR or ACDF for degenerative indications. Propensity score matching based on demographic and clinical characteristics was performed using a 1:1 ratio. Cohorts were evaluated by calculating relative risk of functional and clinical outcomes at multiple time points from 6 months to 5 years. Kaplan-Meier survival curves were used to examine reoperation and adjacent segment disease.
Results:
After matching, 9458 patients (mean age 48 years) were included in both the ACDF and CDR groups. At all follow-up time points, there was a significantly lower risk of anterior reoperation (RR 0.62, 95% CI 0.52-0.74; p < 0.001) and new-onset cervical pain (RR 0.64, 95% CI 0.55-0.73; p < 0.001) among patients who underwent CDR compared with those who underwent ACDF. At the 1-, 2-, and 5-year follow-ups, there was significantly lower risk of surgical site infection (RR 0.62, 95% CI 0.48-0.78; p < 0.001) in the CDR group. After 2 years, there was no difference in codes for acquired kyphosis or lordosis of the cervical spine between the two groups (p > 0.05), and after 5 years, there was significantly lower risk of opioid use (RR 0.66, 95% CI 0.54-0.82; p < 0.001) among patients who underwent CDR.
Conclusions:
These propensity-matched results suggest that CDR offers superior long-term outcomes compared with ACDF. While these findings suggest potential advantages associated with motion-preserving surgery, the results should be interpreted cautiously given the inherent limitations of retrospective electronic health record-based analyses. As the US population continues to age and technologies continue to improve, CDR should be considered as a viable alternative to motion-sacrificing procedures for the treatment of degenerative cervical spine pathologies. Future studies should investigate long-term clinical and radiographic outcomes to further elucidate the findings of this study.