Feasibility and safety of an adaptive endoscopic resection algorithm guided by the muscle-retracting sign for early rectal cancer
Related Experiment Video
Updated: Jul 3, 2026
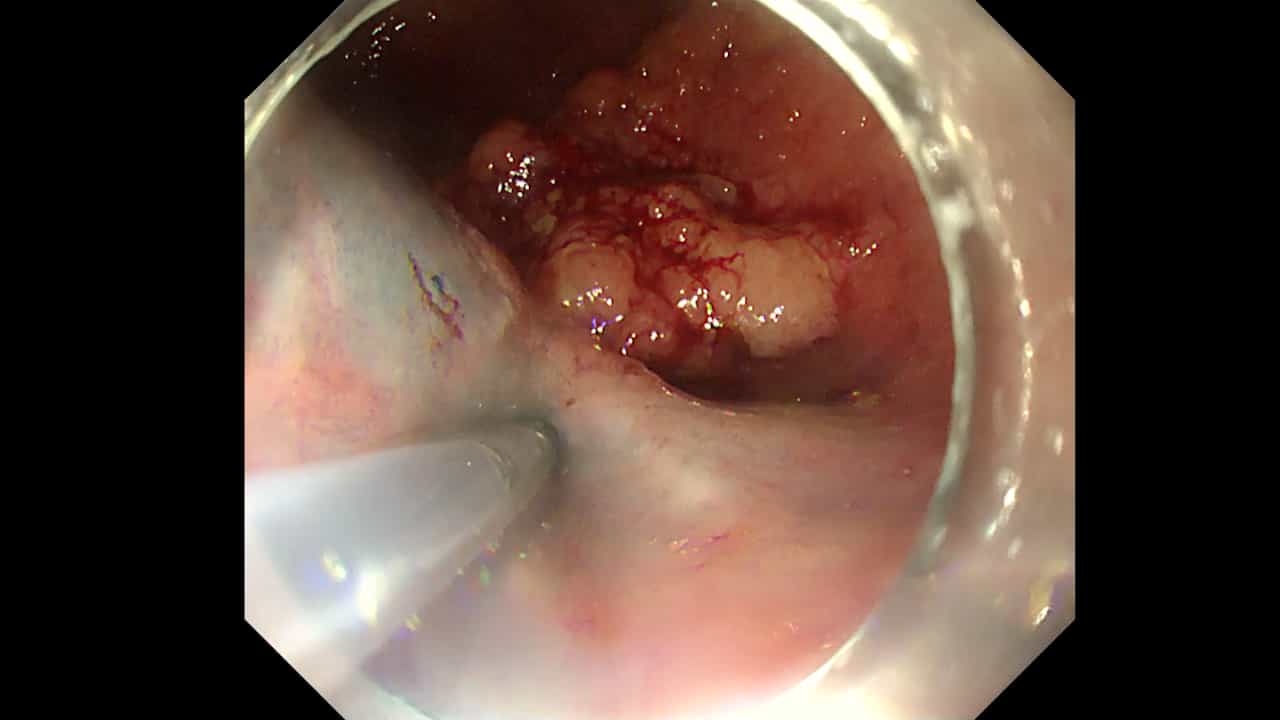
The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Andrea Sorge1,2,3, Maria Eva Argenziano1,4, Pieter Jan Poortmans1,4,5
1University Hospital Ghent, Department of Gastroenterology and Hepatology, Flanders, Belgium, Ghent.

Background:
Endoscopic and radiological staging of early rectal cancer (ERC) remains suboptimal, contributing to inaccurate treatment allocation and the risk of under- and overtreatment. This study aimed to evaluate the feasibility and safety of the Pocket-detection method with Real-time Intraprocedural Muscle-retracting sign Evaluation (PRIME) resection algorithm for ERC.
Methods:
We retrospectively analyzed a prospective registry of rectal lesions managed according to the PRIME algorithm between August 2023 and October 2025. The muscle-retracting sign (MRS) status guided adaptive dissection plane selection: endoscopic submucosal dissection (ESD) if MRS negative; endoscopic intermuscular dissection (EID) or full-thickness resection (knife-assisted [kFTR] or device-assisted [FTRD]) for MRS-positive lesions. Primary outcomes were technical success and the rate of R0 endoscopic resection. The secondary outcomes were the technical success of deep-margin optical diagnosis and adverse events.
Results:
47 lesions were included. MRS prevalence was 34.0% (16/47). Technical success of endoscopic resection was 97.9% (46/47; 95%CI 88.7%-99.9%). ESD was performed in 31 lesions, EID in nine, kFTR in five, and FTRD in one. R0 resection was achieved in 89.1% (41/46; 95%CI 76.4%-96.4%) and R0 vertical margin in 95.7% (44/46; 95%CI 85.2%-99.5%). Technical success of deep-margin optical diagnosis was 100% (47/47; 95%CI 92.5%-100%). Nonsevere (AGREE classification grade I-IIIa) adverse events occurred in 10.6% of patients (5/47; 95%CI 3.5%-23.1%).
Conclusion:
The MRS-guided adaptive endoscopic resection algorithm (PRIME) was feasible and safe for ERC achieving high R0 rates. These findings support its validation in larger studies with longer follow-up.
