Related Experiment Video
Updated: Jul 3, 2026
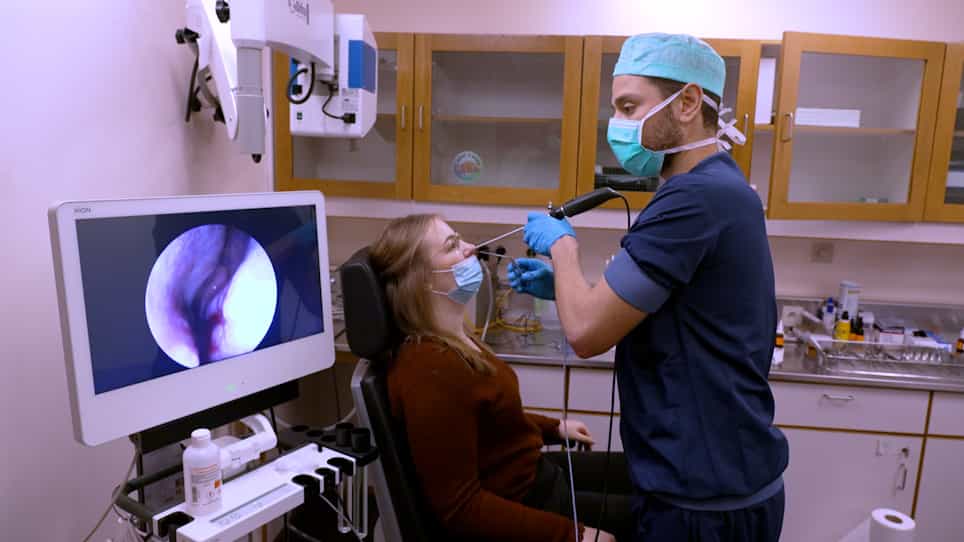

Nasal Brushing Sampling and Processing Using Digital High Speed Ciliary Videomicroscopy – Adaptation for the COVID-19 Pandemic
Published on: November 7, 2020
Preclinical human models of primary ciliary dyskinesia
Jonathan W Y Ong1,2,3, Claire L Jackson1,2,3, Marina Arbi3,4,5
1School of Clinical and Experimental Sciences, University of Southampton Faculty of Medicine, Southampton, UK.

Abstract:
Primary ciliary dyskinesia (PCD) is a genetically heterogeneous disorder caused by defective motile cilia, resulting in impaired mucociliary clearance, chronic respiratory disease, laterality defects and subfertility. Currently, no disease-modifying treatments exist. Targeting PCD at its root cause requires emerging genetic therapies, such as small molecules, oligonucleotides, mRNA therapy, gene replacement and genome editing. With over 52 implicated genes and numerous patient-specific variants, there is a need for robust preclinical models to evaluate and accelerate these approaches. This review examines human preclinical models that recapitulate patient-specific genotypes and phenotypes while providing sufficient scalability for screening and detailed efficacy assessment. The models should also resolve knowledge gaps, including which cells need targeting and at what stage of differentiation. Air-liquid interface cultures of primary human airway epithelial cells or induced pluripotent stem cells (iPSCs) represent the current practice, alongside three-dimensional organoids, spheroids and lung-on-a-chip platforms. To overcome the limited proliferative capacity of primary cells, strategies include BMI-1 or hTERT transduction, conditional reprogramming with Rho-associated kinase (ROCK) inhibitors and feeder layers, and differentiation of iPSCs. Patient-derived and CRISPR-edited models have been developed for multiple PCD genes. Outcome measures to confirm efficacy of the therapy include high-speed video microscopy for quantifying ciliary beat pattern, transmission electron microscopy for ultrastructural assessment, mucociliary clearance assays and deep molecular phenotyping. There is a need for field-wide standardisation through consensus protocols, core outcome sets, minimum reporting criteria, quality benchmarks and regulatory alignment to facilitate accelerated translation of preclinical findings to clinical therapeutics.
Insights
Primary ciliary dyskinesia (PCD) research needs better preclinical models for genetic therapies. This review explores human models to evaluate treatments for this rare respiratory disease.
Area of Science:
- * Genetics and regenerative medicine
- * Respiratory diseases and cell biology
Background:
- * Primary ciliary dyskinesia (PCD) is a genetic disorder affecting motile cilia, leading to chronic respiratory issues and subfertility.
- * Current treatments for PCD are not disease-modifying, highlighting the need for advanced genetic therapies.
- * Over 52 genes are implicated in PCD, with numerous patient-specific variants, necessitating effective preclinical models.
Purpose of the Study:
- * To review human preclinical models for primary ciliary dyskinesia (PCD) that accurately reflect patient genotypes and phenotypes.
- * To assess the scalability and efficacy of these models for screening genetic therapies.
- * To identify knowledge gaps and inform the development of targeted therapeutic strategies for PCD.
Main Methods:
- * Examination of various human preclinical models including air-liquid interface cultures, 3D organoids, spheroids, and lung-on-a-chip platforms.
- * Discussion of strategies to enhance cell proliferation, such as BMI-1/hTERT transduction and induced pluripotent stem cell (iPSC) differentiation.
- * Review of patient-derived and CRISPR-edited models for evaluating genetic therapies.
Main Results:
- * Human preclinical models, including iPSC-derived and organoid systems, can recapitulate PCD patient-specific genotypes and phenotypes.
- * Various methods like high-speed video microscopy and deep molecular phenotyping are used to assess therapeutic efficacy.
- * Strategies exist to overcome limitations of primary cell cultures, enabling robust model development.
Conclusions:
- * Robust preclinical models are crucial for accelerating the development and translation of genetic therapies for PCD.
- * Standardized protocols, core outcome sets, and regulatory alignment are needed to advance PCD therapeutics.
- * Further research into cell targeting and differentiation stages is required for effective treatment strategies.


