Related Experiment Video
Updated: Jul 3, 2026
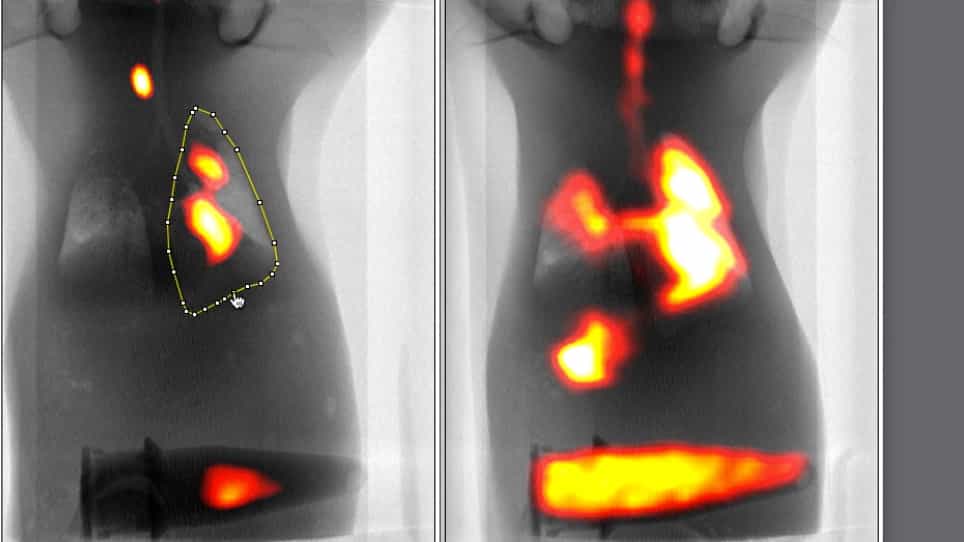

In vivo Evaluation of Mucociliary Clearance in Mice
Published on: December 18, 2020
Airway structural involvement detected by quantitative computed tomography in controlled and uncontrolled asthma
Letícia Pereira Lima1, Izabela Maria Elias Silva1, Lucas Botelho Azevedo1
1Department of Medicine, Medical School of Ribeirão Preto, University of São Paulo, Ribeirão Preto, Brazil.

Background:
Structural airway changes (airway remodeling) are traditionally associated with severe and uncontrolled asthma. The extent to which they are present in asthmatics with different clinical control statuses is unknown. Quantitative computed tomography (qCT) is an underused tool for assessing airway morphology and remodeling. In this study, we aimed to compare airway morphology between individuals with severe uncontrolled asthma (SA), controlled asthma (CA), and non-asthmatic controls (C) using qCT. We also sought correlations between qCT metrics and spirometric measurements.
Methods:
In this cross-sectional observational study, we recruited asthmatics (SA, CA) and non-asthmatic controls (C) aged 18-65 between March 2016 and February 2018. All subjects underwent spirometry and high-resolution chest computed tomography (CT). Quantitative CT analysis was performed using an automated software (YACTA v2.7). Airway metrics included total airway count (TAC), airway wall thickness (WT), relative wall thickness (Wall%), lumen area (LA) and mean maximal attenuation of airway walls. We compared groups using ANOVA and investigated correlations between spirometry and qCT metrics through Pearson coefficients.
Results:
Seventy-six individuals were included (SA n = 27, CA n = 28, C n = 21). Severe uncontrolled asthmatics were taking more intense asthma treatment and had lower forced expiratory volume in the first second (FEV1) compared with CA and C groups (FEV1%predicted: 55.37 + 12.64 × 91.21 + 9.74 × 104.93 + 15.7, respectively; p = 0.0001). Wall% (49.4 + 3.38 × 48.3 + 4.51 × 45.3 + 3.71; p = 0.001) and WT were higher in both asthma groups compared with controls (2.06 + 0.28 × 1.89 + 0.34 × 1.62 + 0.27; p = 0.0001; mm; 3rd bronchial generation); TAC was progressively greater from SA to CA and C groups (27.22 + 17.29 × 43,61 + 20,11 × 57,23 + 16,82; p = 0.0001). Lumen area (bronchial 3rd generation, in mm2) was lower in SA than in CA and C (52.95 + 17.29 × 65.78 + 14.53 × 66.92 + 13.57; p = 0.002). Forced expiratory volume in the first second correlated positively with TAC (r = 0.67) and negatively with Wall% (r=-0.59).
Conclusions:
Our findings defy the usual outlook of morphological airway involvement only in severe asthma. Further studies are needed to explore the nature of structural involvement in CA, while we showed the usefulness of qCT in evaluating seldom-assessed elements of asthma pathophysiology.
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:13
Asthma III: Clinical Manifestations
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma