Related Experiment Video
Updated: Jul 4, 2026
Combination of High Ligation and Intraoperative Embolization Using Polidocanol for Treatment of Varicoceles
Published on: December 22, 2023
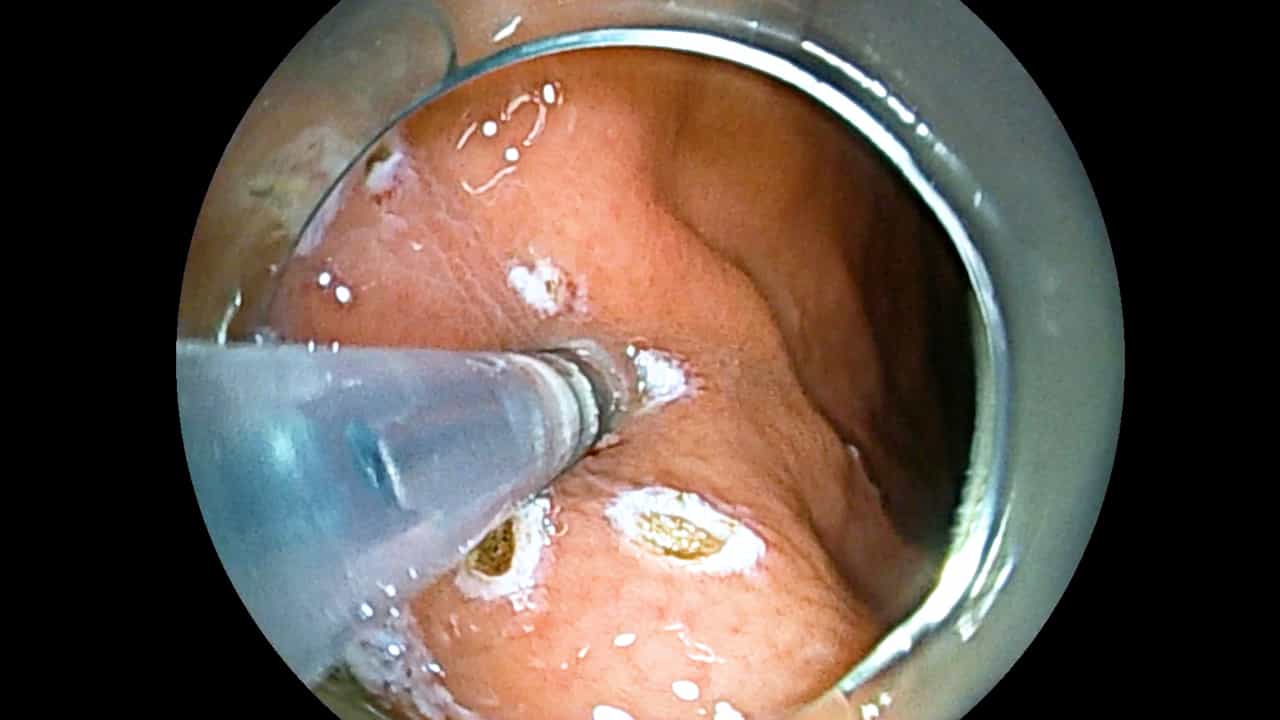
Low excision and high suspension hemorrhoidectomy versus conventional Milligan-Morgan hemorrhoidectomy for mixed
Yingzi Shu1,2, Heng Deng3, Jing Zhu4
1Department of Colorectal Surgery, The Second Affiliated Hospital, Anhui University of Chinese Medicine, No 300, Shouchun Road, Hefei City, 230000, China.

Background:
Mixed hemorrhoids represent a highly prevalent benign anorectal disorder. Milligan-Morgan hemorrhoidectomy (MM) is the gold-standard treatment but carries substantial risks of severe postoperative pain, delayed recovery, and anal dysfunction due to extensive tissue resection. Low excision and high suspension hemorrhoidectomy (LEHS) is a refined, function-preserving technique, yet high-quality long-term comparative evidence remains limited. This study aimed to assess the efficacy, safety, and anal functional outcomes of LEHS versus MM for grade III-IV mixed hemorrhoids over 12 months.
Methods:
This single-center, prospective, randomized, non-inferiority trial enrolled 120 eligible patients between January 2024 and June 2024, randomized 1:1 to LEHS or MM groups with allocation concealment and blinded outcome assessment. Primary outcomes were 12-week clinical effective rate and 12-month hemorrhoid recurrence rate; secondary outcomes included perioperative indicators, pain scores, recovery metrics, complications, anorectal manometry, and patient satisfaction. Statistical analysis was performed via SPSS 26.0 with a -10% non-inferiority margin (P < 0.05).
Results:
Baseline characteristics were well balanced between groups (all P > 0.05). The 12-week effective rate (96.4% vs. 92.9%) and 12-month recurrence rate (1.8% vs. 5.4%) confirmed LEHS non-inferiority (both P > 0.05). LEHS yielded longer operative time, less blood loss, lower VAS pain scores, faster recovery, fewer complications (14.8% vs. 33.3%, P = 0.027), and more favorable anorectal physiology (all P < 0.001), with higher patient satisfaction.
Conclusions:
LEHS is non-inferior to MM in clinical efficacy and long-term recurrence control for grade III-IV mixed hemorrhoids, with superior safety, faster recovery, and better-preserved anal function without excessive hypertonia. It is a reliable, minimally invasive surgical alternative worthy of clinical promotion.
Trial Registration:
ClinicalTrials.gov, NCT07495046 (Registered: March 2026, retrospectively registered).

Related Concept Videos
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: