Related Experiment Video
Updated: Jul 4, 2026
Clinical Efficacy of Ultrasound-Assisted Scoliosis-Specific Exercise in Mild-Grade Adolescent Idiopathic Scoliosis
Published on: December 2, 2025
Does apical vertebra location influence the final outcome of bracing for idiopathic scoliosis?
Angelo G Aulisa1, Martina Marsiolo2, Marco Giordano3
1Department of Human Sciences, Society and Health, University of Cassino and Southern Lazio, Cassino, Frosinone, Italy.

Background:
Idiopathic scoliosis represents a complex spinal alteration characterized by lateral curvature and rotation of the spine. Among the numerous factors influencing treatment response, the role of the apical vertebra in idiopathic scoliosis remains a topic of significant interest and debate. The apical vertebra, situated at the apex of the scoliotic curve, holds a pivotal position in determining the overall spinal alignment and, consequently, the efficacy of conservative treatments. Several studies have shown that patients with apical vertebrae located in the thoracic spine are more likely to have progression of their curves than patients with apical vertebrae located in the lumbar spine. Additionally, patients with apical vertebrae located in the upper thoracic spine are more likely to have poorer outcomes than patients with apical vertebrae located in the lower thoracic spine. Therefore, understanding the nuanced relationship between the characteristics of the apical vertebra and treatment outcomes is paramount for tailoring therapeutic strategies and optimizing patient care.
Aim:
This study aims to comprehensively analyze the influence of apical vertebra location and rotation on the outcome of conservative treatment of idiopathic scoliosis.
Design:
This is an observational controlled cohort study nested in a prospective clinical ongoing database in patients with idiopathic scoliosis.
Setting:
Inpatient and outpatient in Rome.
Methods:
From a consecutive series of patients included in a prospective database, we selected 491 patients with Adolescent Idiopathic Scoliosis with curves of 20-40° (mean: 27.89°±5.15°), Risser grade 0-2 who were treated with a brace at 2 years minimum follow-up (mean: 53.62±49.63 months). X-rays were used to obtain Cobb degrees and torsion of the apical vertebrae (Perdriolle's method). Three outcomes were distinguished according to SRS-SOSORT criteria: correction, stabilization, and progression. The location and rotation of the apex vertebra and8 the degrees of the curve were analyzed using statistical analysis.
Results:
The results of our study showed that, among 491 patients with a definite outcome, the Cobb mean value was 27.89±5.158 SD at baseline and 16.99±15.85 SD at follow-up (P<0.0001; R=0.3228). Perdriolle was initially 11.9±7.319 and 7.319±7.816 at follow-up (P<0.0001, R=0.4865). Overall, 411 patients (84%) achieved curve correction, and stabilization was attained in 70 cases (14%). Ten patients (2%) experienced curve progression, and one patient was recommended for surgery because the curve at follow-up was greater than 45°. The analysis of subgroups shows statistically significant differences in the means of L1 and D9, L1 and D8, L1 and D7, L2 and D7, and D12 and D7; the P values are less than 0.05 (Table I). Moreover, a significant correlation was observed between the apex vertebra and the mean Cobb correction (P<0.0001) (R=0.64).
Conclusions:
Our study demonstrates that the apical vertebra plays a significant role in the outcome of conservative treatment for AIS. Patients with apical vertebrae located in the thoracic spine, particularly in the upper thoracic spine, were more likely to have poorer outcomes compared to patients with apical vertebrae located in the lumbar spine.
Clinical Rehabilitation Impact:
These findings highlight the importance of considering the location of the apical vertebra when determining the prognosis and treatment plan for patients with AIS. Moreover, we can affirm that brace treatment is an effective method for the treatment of AIS, in fact, the majority of patients achieved curve correction and stabilization, with a low incidence of curve progression and surgery.
More Related Videos
 07:12
Clinical Efficacy of an Innovative Multidimensional Traction Therapy in Moderate Adolescent Idiopathic Scoliosis
Published on: February 10, 2026
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:16
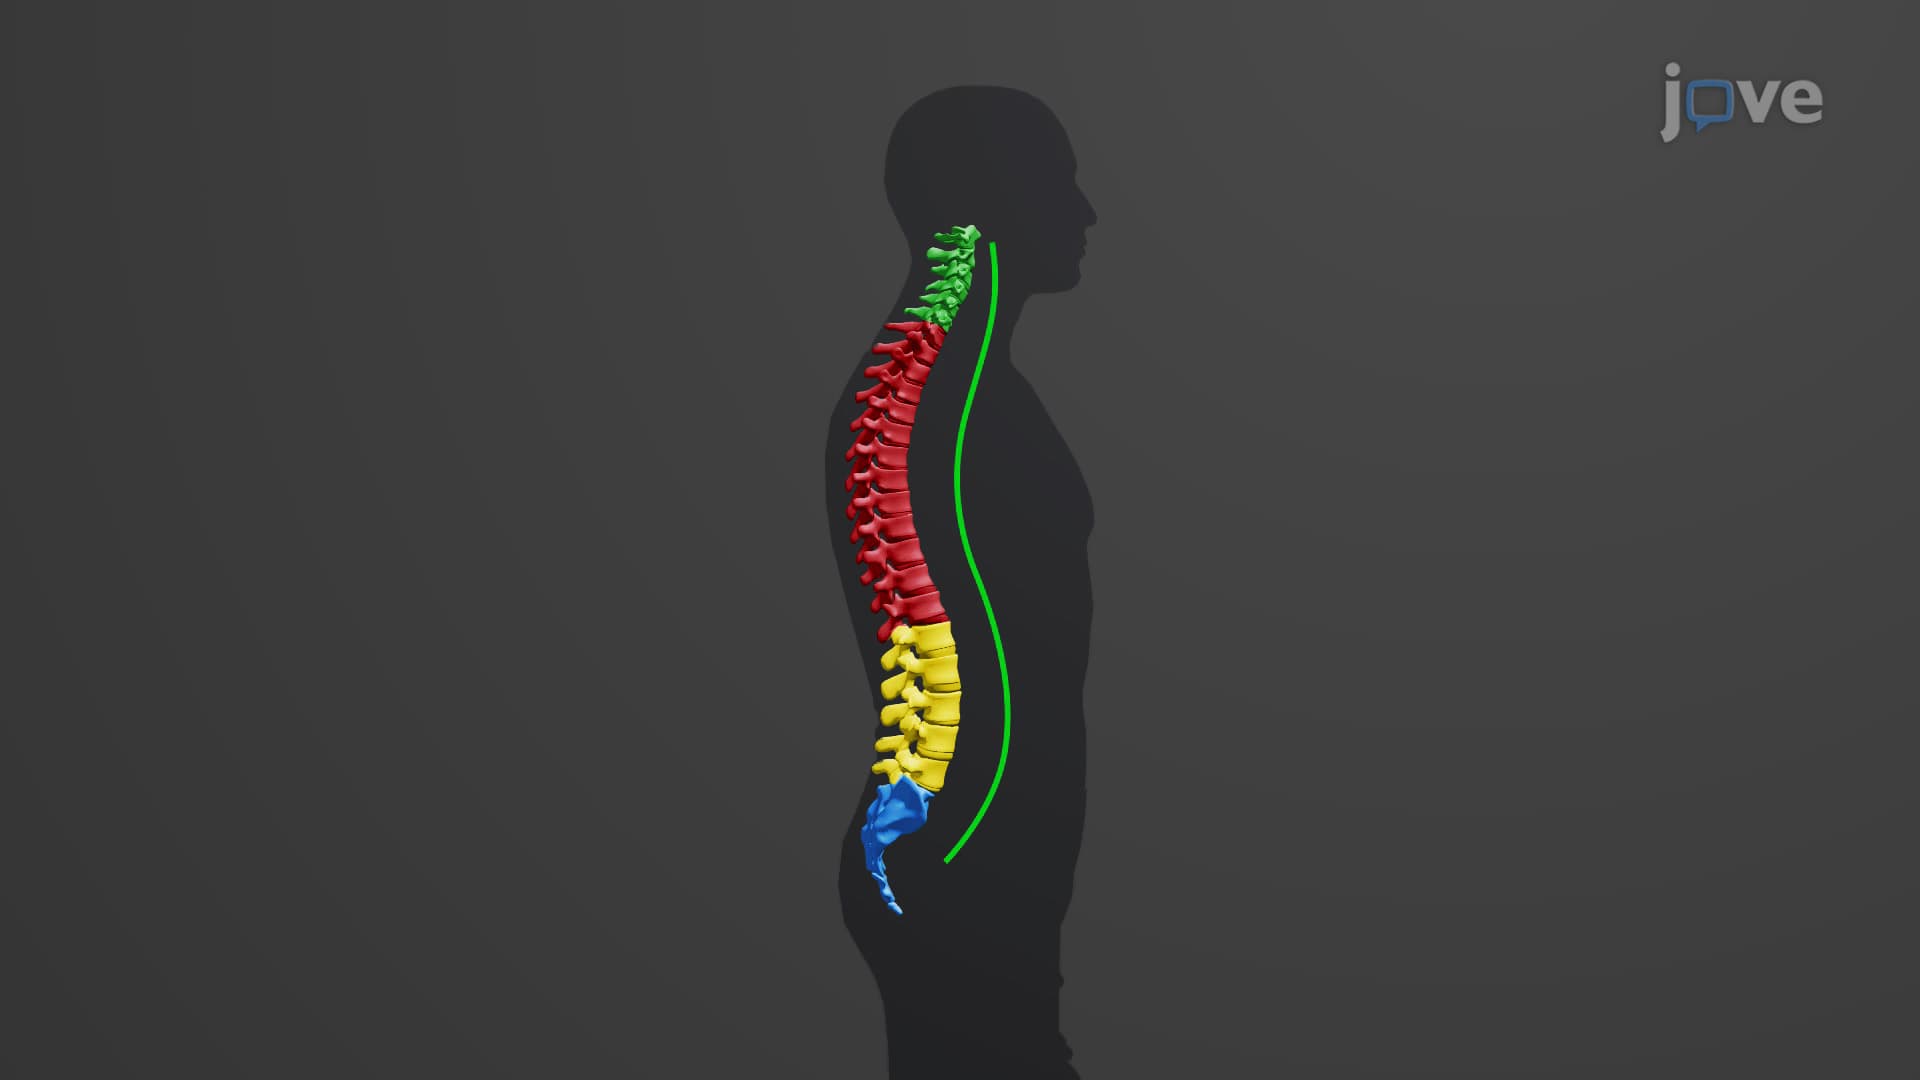
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:30
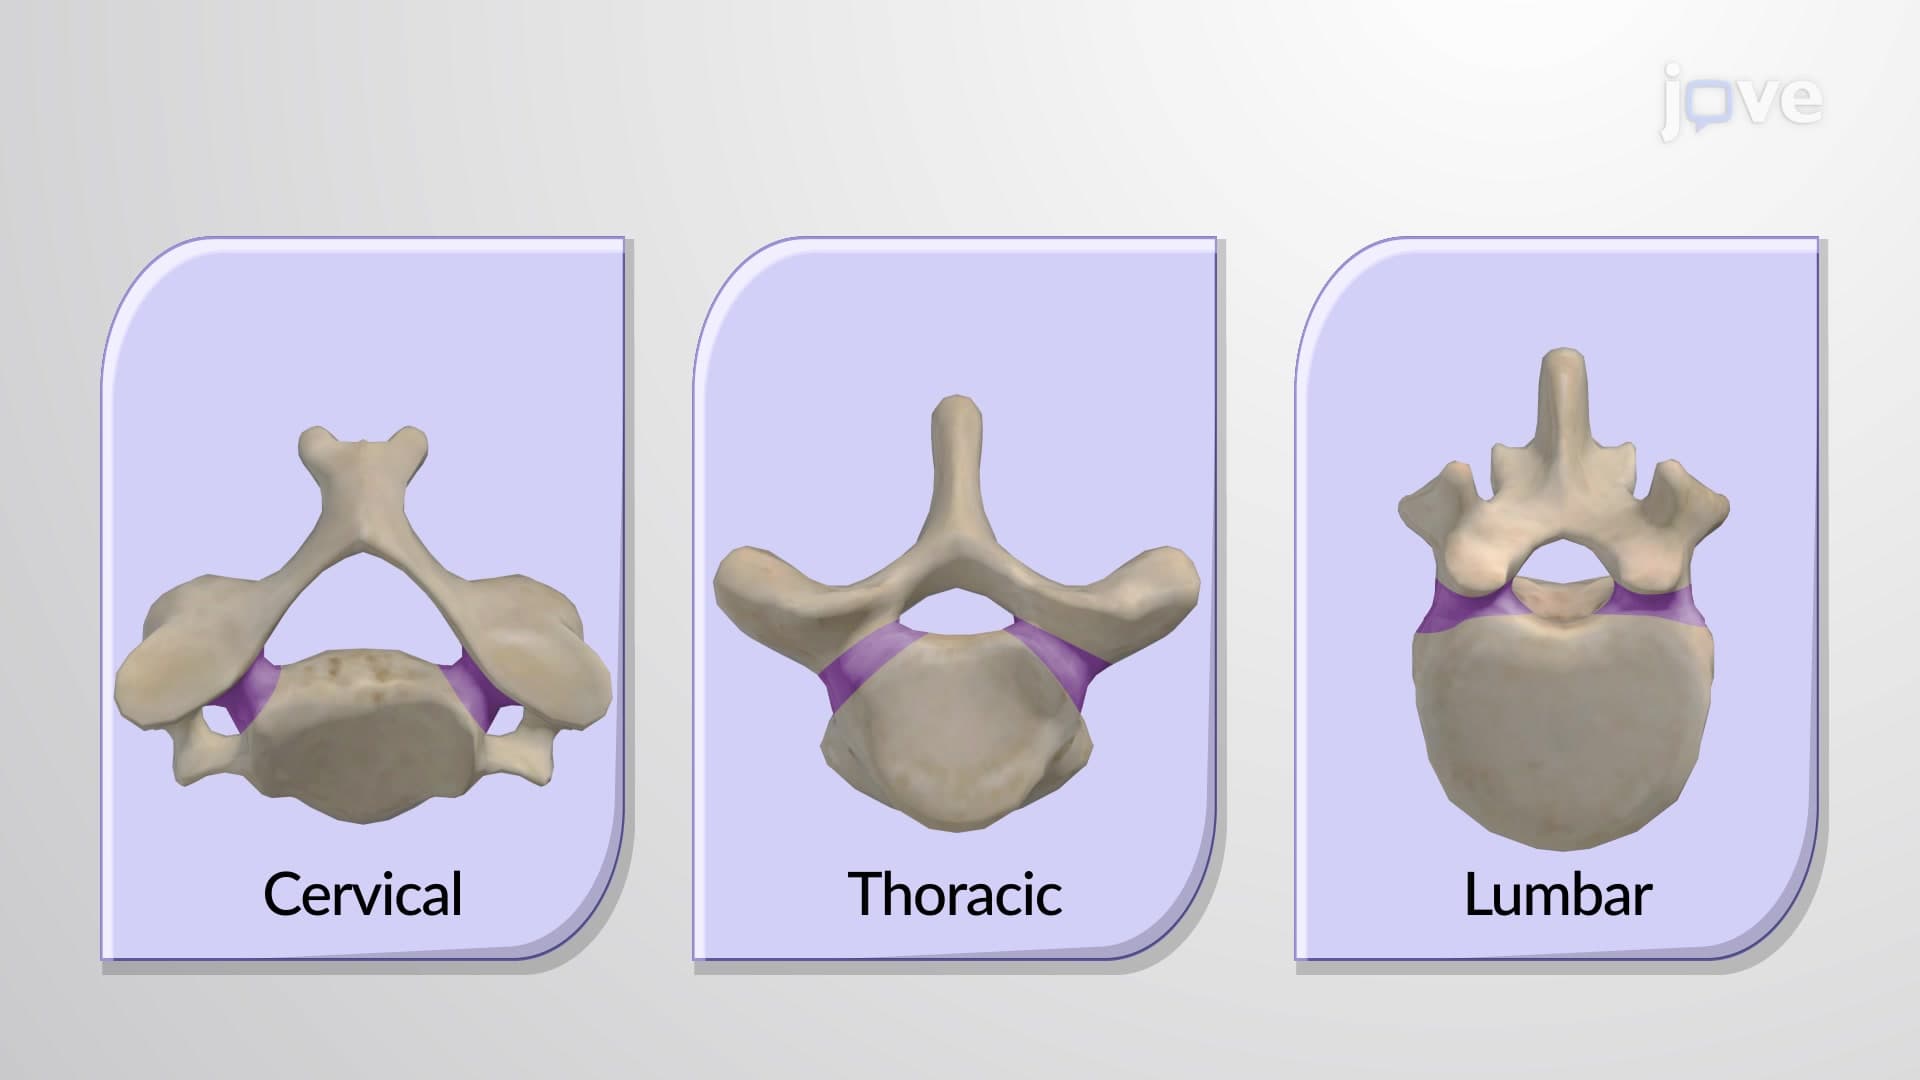
General Structure of a Vertebra
 01:28
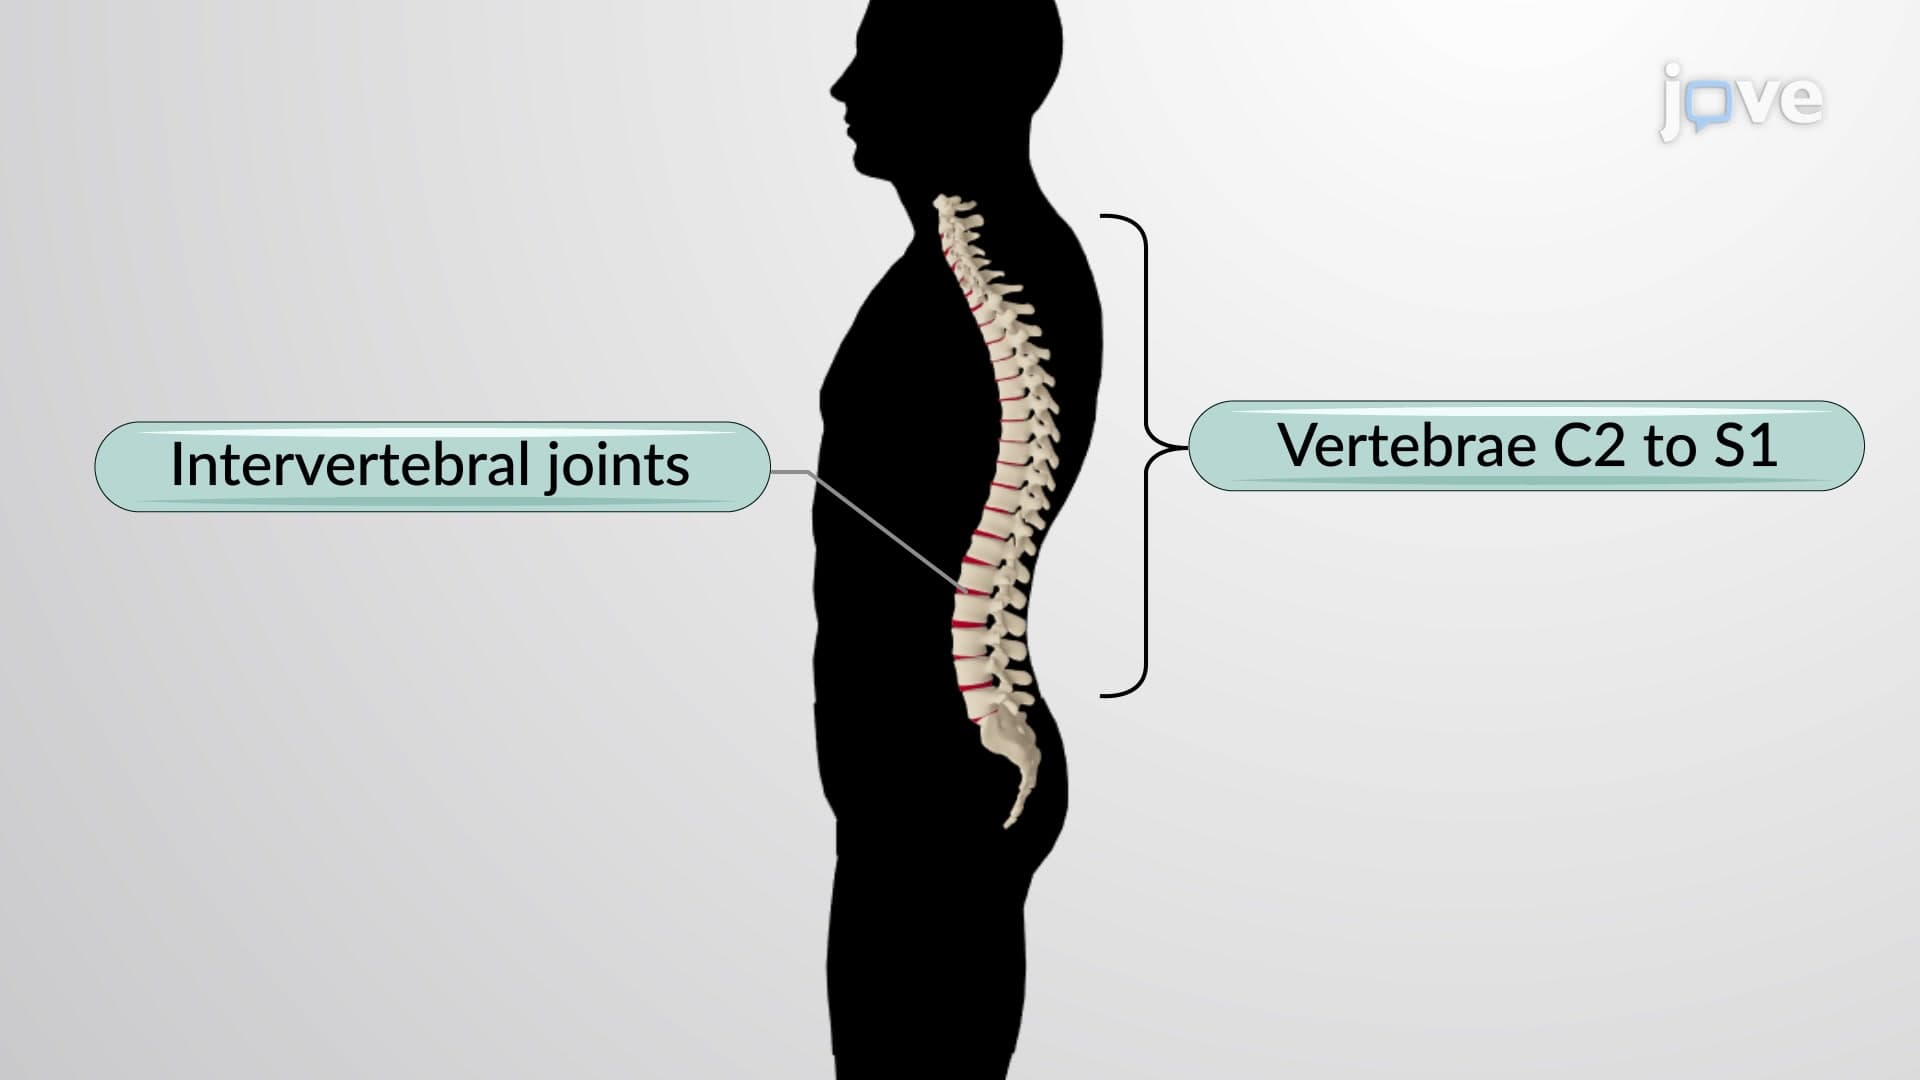
Articulations of the Vertebral Column