Related Experiment Video
Updated: Jul 4, 2026


Using Continuous Data Tracking Technology to Study Exercise Adherence in Pulmonary Rehabilitation
Published on: November 8, 2013
Adherence to pulmonary rehabilitation in COPD: determinants and development of a parsimonious risk model
Yide Wang1,2, Qianqian Liang1, Xiangpeng Li1
1Department of Comprehensive Pulmonary Medicine, The Fourth Clinical Medical College of Xinjiang Medical University, Urumqi, China.

Background:
Adherence to pulmonary rehabilitation (PR) among individuals with chronic obstructive pulmonary disease (COPD) is suboptimal and highly variable, attenuating real-world benefits. We sought to quantify PR adherence and its determinants across domains and to develop a parsimonious, clinically usable risk model for non-adherence.
Methods:
We performed a PRISMA-guided systematic review and meta-analysis of observational studies including adults with COPD (inception to June 30, 2025; PROSPERO CRD420251068914). Random- or fixed-effects models pooled adherence proportions and odds ratios (ORs) for prespecified determinants spanning disease, patient, treatment, system/health-care personnel, and socioeconomic domains. Pooled log-odds were mapped to logistic coefficients to construct candidate prediction models; performance was assessed by AUC, calibration, and decision-curve analysis.
Results:
Twenty-eight studies (N.=17,903; 1999-2025) were included. The pooled adherence rate was 58.36% (95% CI 52.8-63.8; I2=97.6%). Adherence was higher in high-income settings (66.84%) than in upper-/lower-middle income settings (49.76%); highest in hybrid hospital-community programs (67.03%) versus facility-based (62.89%) and home/remote programs (53.91%); and lower during AECOPD phases (46.46%) than in stable COPD (61.96%). Non-adherence was associated with greater symptom/HRQoL burden (OR=1.35), higher treatment intensity (OR=1.97), smoking exposure (OR 3.26), depression (OR=1.35), and recent exacerbation (fixed-effects OR=1.62); protective factors included better exercise capacity (OR=0.41), higher educational attainment (OR=0.44), and higher income/SES (OR=0.61). A 16-variable model achieved AUC=0.802 with good calibration, while a four-predictor parsimonious model (smoking, exercise capacity, acute exacerbation, higher education) maintained robust discrimination (AUC=0.752), good calibration, and superior net benefit versus "treat all/none" across clinically relevant thresholds.
Conclusions:
PR adherence in COPD is modest and highly heterogeneous, shaped by disease burden, psychological/behavioral factors, program design, and socioeconomic context. The parsimonious model should be interpreted as an evidence-informed screening framework rather than a definitive individual-level prediction tool; external validation, local recalibration, and prospective testing are required before routine implementation.
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:24
Chronic Obstructive Pulmonary Disease
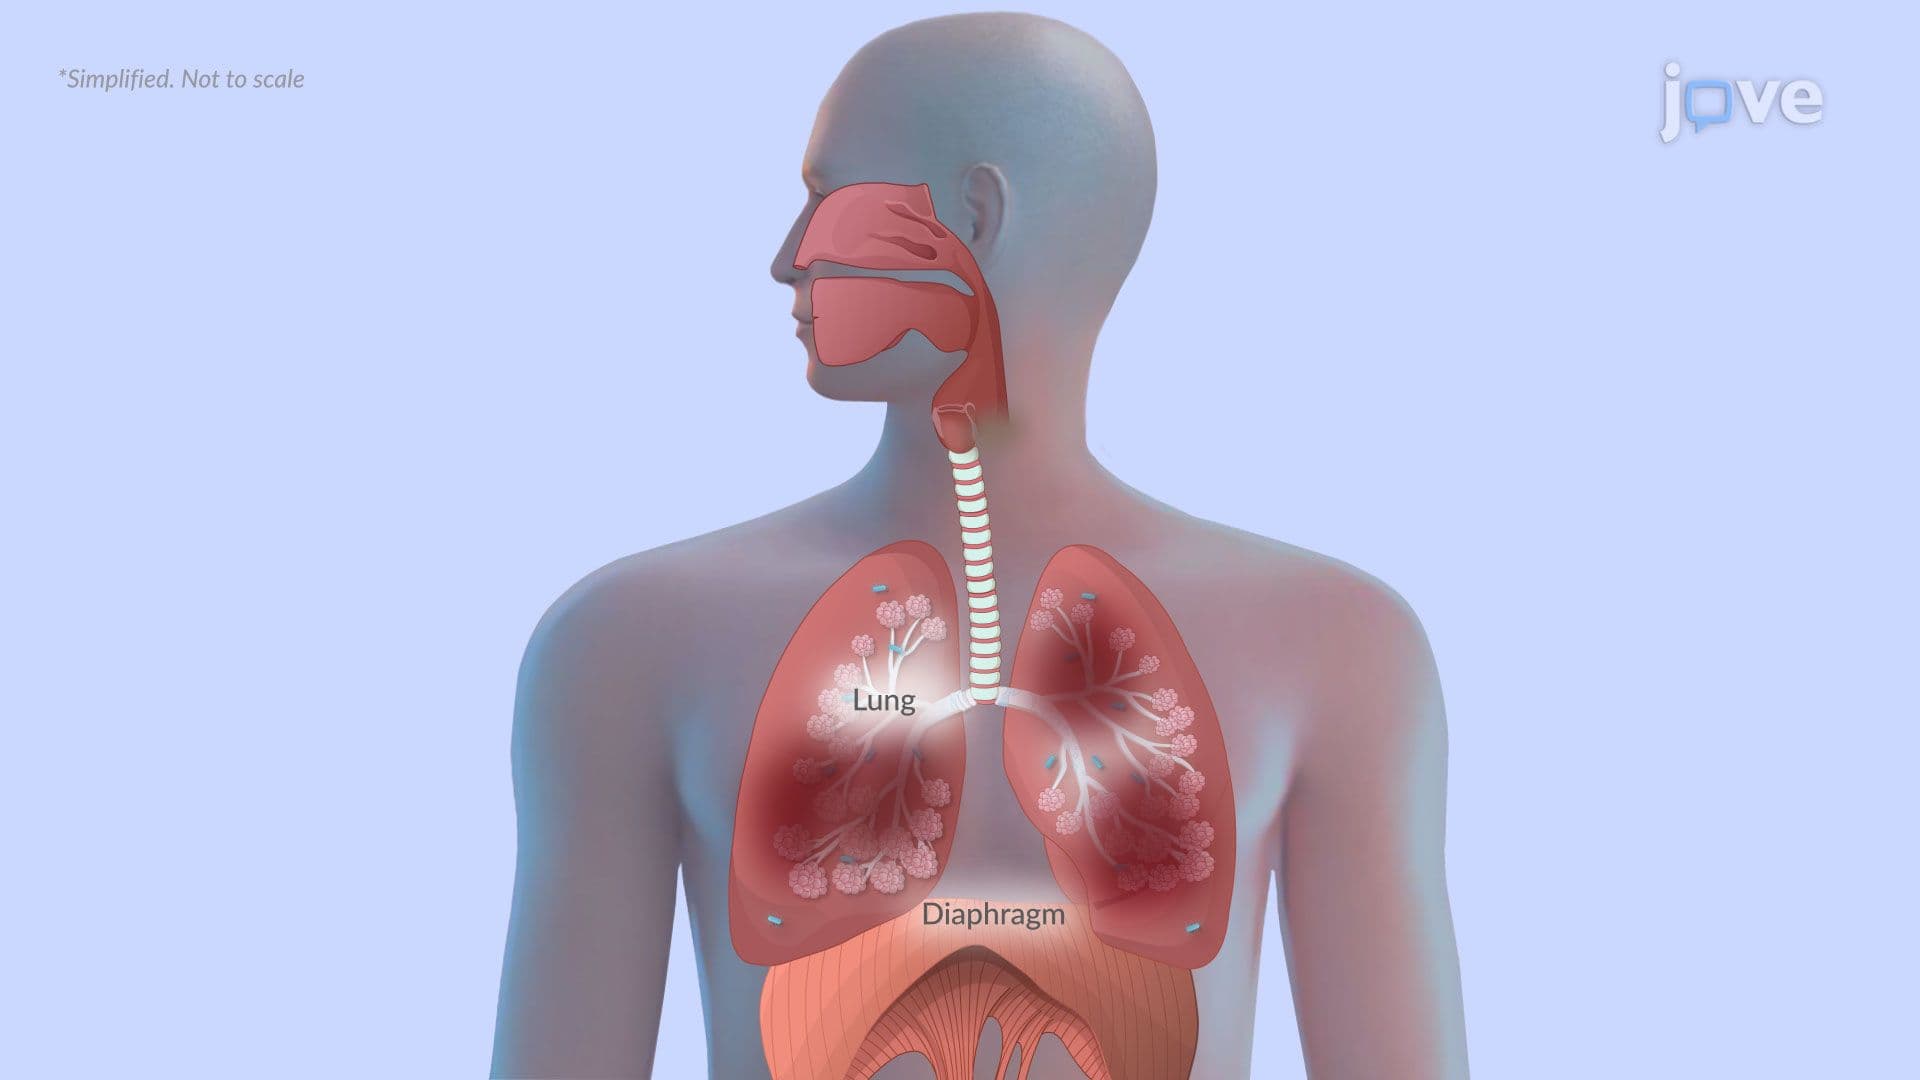
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...