Related Experiment Video
Updated: Jul 4, 2026
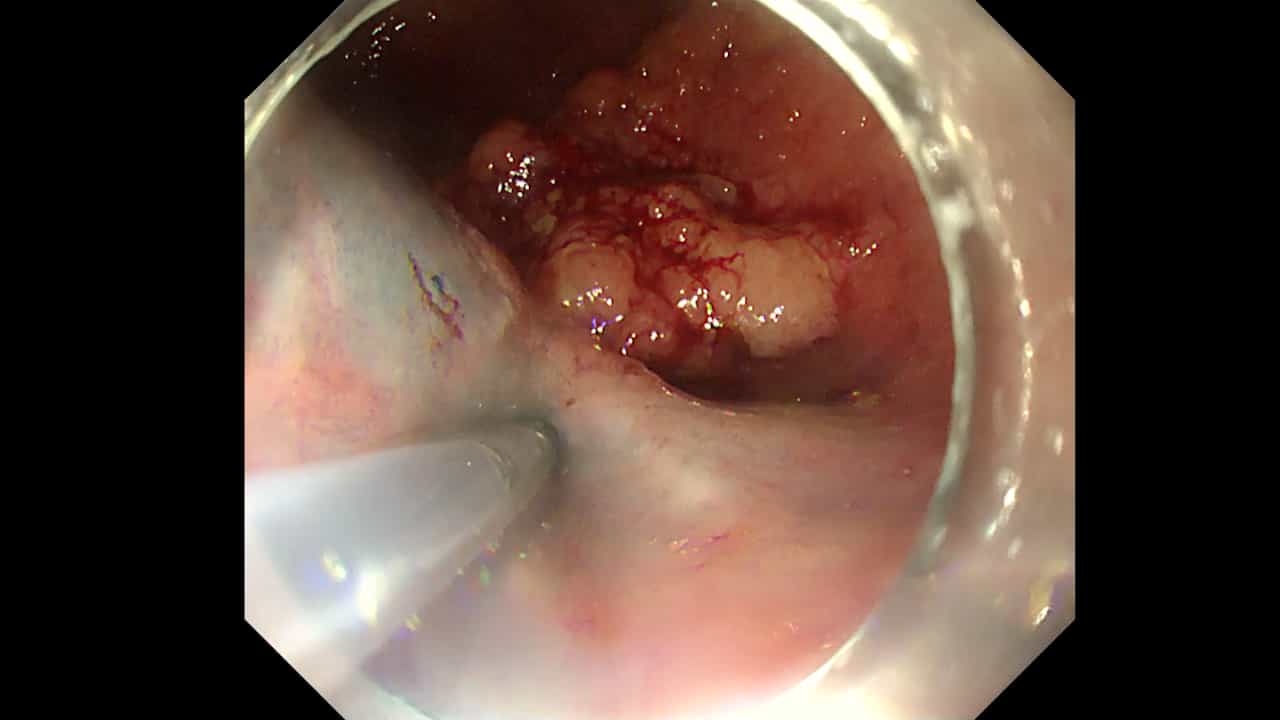

The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Outcomes of subsequent endoscopic resection for rectal neuroendocrine tumors with positive/indeterminate vertical
Mitsunori Kusuhara1,2, Masau Sekiguchi1,3,4, Naoya Toyoshima1
1Department of Endoscopy, Gastrointestinal Endoscopy Division, National Cancer Center Hospital, Chuo-ku, Tokyo, Japan.

Background And Aims:
Management of rectal neuroendocrine tumors (NETs) with positive/indeterminate vertical margins (VM1/VMX) after endoscopic resection (ER) remains unestablished. We aimed to evaluate the outcomes of subsequent ER for rectal NETs after initial ER with VM1/VMX.
Methods:
We conducted a retrospective analysis of rectal NET cases undergoing subsequent ER at a high-volume center, where such cases were frequently referred and subsequent ER was the principal management strategy, except when the risk of metastasis was considered especially high. We assessed the presence of a residual tumor based on lesion characteristics as well as initial ER techniques and outcomes. Additionally, we assessed subsequent ER outcomes, including en bloc and R0 (en bloc with negative cut margins) resection and adverse events. For patients with follow-up longer than 1 year, we examined recurrence.
Results:
Among 54 lesions in 51 patients undergoing subsequent ER, a residual tumor was found histologically in 20.4%, despite no endoscopic evidence of residual on the initial resection site. Subsequent ER, mainly endoscopic submucosal resection with a ligation device and endoscopic submucosal dissection, achieved en bloc resection in all and R0 resection in 10 of 11 residual cases without any adverse events. No recurrences were observed during a median follow-up period of 40 months.
Conclusions:
A residual tumor was present in a nonnegligible proportion of rectal NETs undergoing subsequent ER after initial ER with VM1/VMX. ER of residual rectal NET in patients with VM1/VMX was successful with no recurrence. Our findings suggest the potential usefulness of subsequent ER for these rectal NET cases.
