Related Experiment Video
Updated: Jul 4, 2026

Generation of a Chronic Obstructive Pulmonary Disease Model in Mice by Repeated Ozone Exposure
Published on: August 25, 2017
Declining age-adjusted mortality but persistent inequalities in chronic obstructive pulmonary disease in the United
Hongnan Zhang1,2,3, Fan Xiao1,2,3, Lieliang Zhang1,2,3
1Department of Anesthesiology, The Second Affiliated Hospital of Nanchang University, Nanchang, China.

Background:
Chronic obstructive pulmonary disease (COPD) remains a leading cause of premature mortality and disability worldwide. National averages in the United States often obscure heterogeneity across sex, geography, rurality, and age. We examined U.S. COPD mortality trends from 1999 to 2024 and contextualized findings using Global Burden of Disease (GBD) 2023 data.
Methods:
We conducted a serial cross-sectional ecological study using Centers for Disease Control and Prevention Wide-ranging Online Data for Epidemiologic Research (CDC WONDER) mortality data and investigator-generated GBD 2023 visual outputs. Age-adjusted mortality rates (AAMRs, per 100,000 population, standardized to the year 2000 U.S. standard population) were assessed by sex, age group, race and ethnicity, census region, state, and urbanization. Joinpoint regression (National Cancer Institute Joinpoint software, v5.2.0) was used to estimate annual percent changes (APCs), average annual percent changes (AAPCs), and 95% confidence intervals (CIs). GBD 2023 figures contextualized global prevalence, socio-demographic development and COPD disability-adjusted life-years (DALYs), and regional risk-factor contributions.
Results:
From 1999 to 2024, COPD deaths rose from 99,550 to 132,115 (+32.71%), while the AAMR declined from 56.38 to 45.26 per 100,000 (AAPC, -0.88; 95% CI, -1.15 to -0.61). Men showed greater improvement (74.09 to 47.97; AAPC, -1.59) than women (46.03 to 43.17; AAPC, -0.31), whose rates rose until 2016 before declining. Urban-rural disparities widened: metropolitan areas improved (54.91 to 47.16; AAPC, -0.61), whereas nonmetropolitan areas worsened (62.73 to 72.41; AAPC, +0.77). In 2024, state-level AAMRs ranged from 18.51 to 85.39 per 100,000. Age gradients were steep, from 0.08 among adults aged 25-34 years to 523.69 per 100,000 among those aged ≥85 years. GBD 2023 data confirmed a non-linear pattern across socio-demographic development, with burden driven by smoking, ambient particulate pollution, occupational exposures, and household air pollution.
Conclusion:
U.S. COPD mortality has improved nationally, yet progress remains uneven. Population ageing, slower decline among women, and persistent rural and geographic inequalities sustain the burden. Public health strategies should prioritize women-centered case finding, rural access to smoking cessation and pulmonary rehabilitation, and place-based exposure reduction.
Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
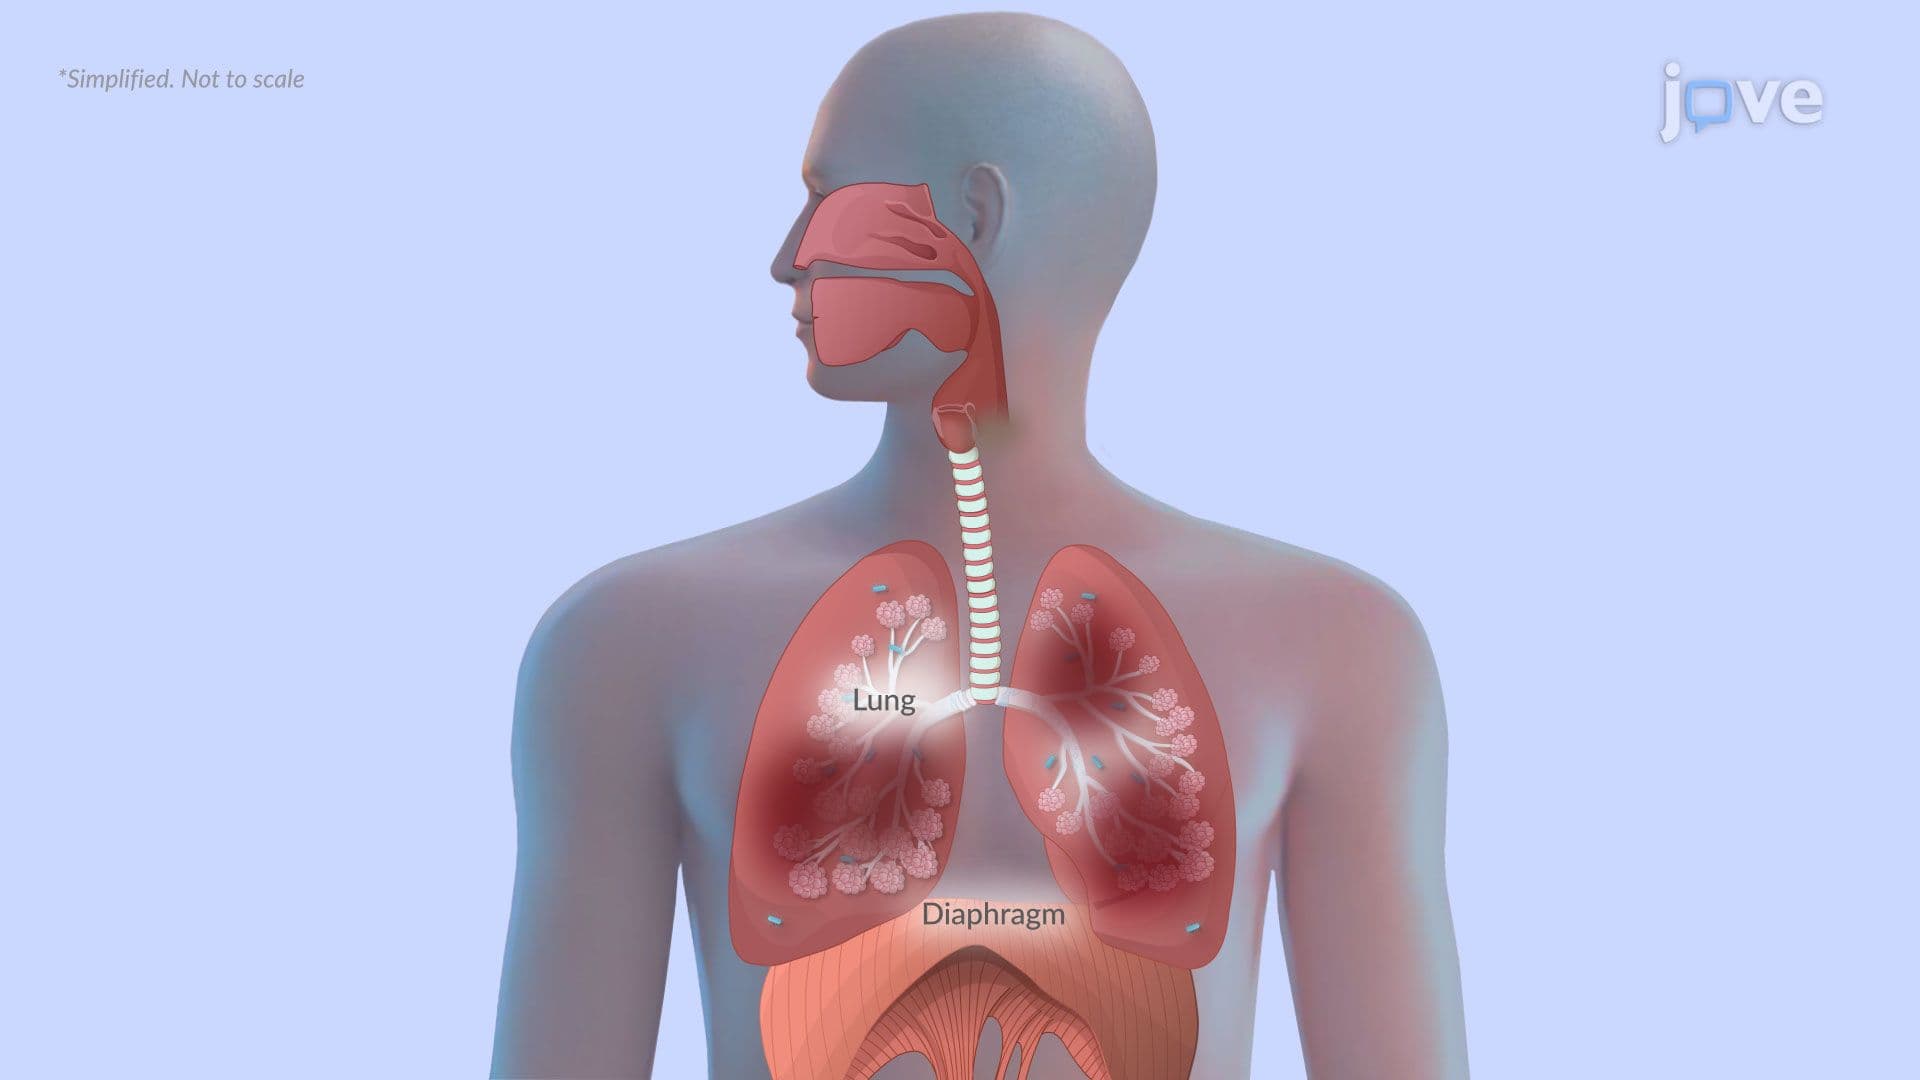
Chronic Obstructive Pulmonary Disease I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation