Related Experiment Video
Updated: Jul 4, 2026
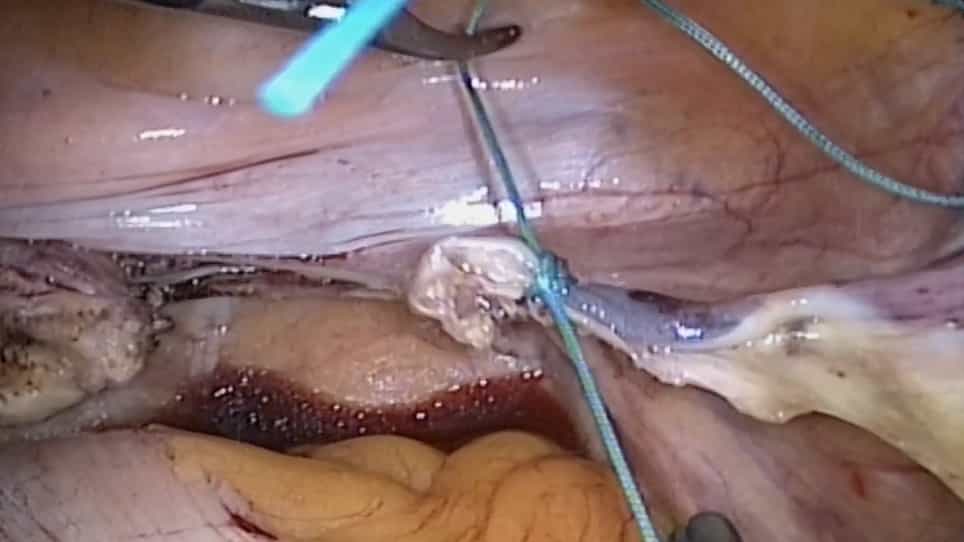
Laparoscopic Non-Mesh Cerclage Pectopexy for Pelvic Organ Prolapse
Published on: September 13, 2022
Neutrophil-to-lymphocyte ratio is associated with early cervical shortening after cerclage: a single-center cohort
Yuance Xu1, Linlin Zhang1, Shuang Guo1
1Department of Gynecology, Jilin Women And Children Health Hospital (Jilin Province Maternal and Child Health Quality Control Center), Changchun, China.

Objective:
This study aimed to explore whether pre-operative systemic inflammatory markers-neutrophil-to-lymphocyte ratio (NLR) and C-reactive protein (CRP)-are associated with early post-cerclage cervical shortening and to examine whether atosiban use varied according to inflammatory status in this retrospective cohort.
Methods:
A single-center retrospective cohort study conducted in 2023 included 84 singleton pregnancies that underwent McDonald cerclage. Full blood count and CRP were measured within 24 h before surgery. The primary outcomes were (i) the cervical length (CL) shortening rate (mm/week) up to 28 weeks' gestation and (ii) spontaneous preterm birth before 32 weeks' gestation. Atosiban was administered at the attending physician's discretion to women with threatened preterm labor or recurrent uterine contractions, not by random allocation. Treatment allocation was non-random and susceptible to confounding by indication.
Results:
NLR correlated linearly with CL shortening (r = 0.61, p < 0.001). A multivariable regression analysis showed that each 1-unit increase in NLR was associated with an additional 0.09 mm/week of cervical shortening. Among high-NLR (≥3.5) women, PTB before 32 weeks' gestation occurred in 60.0% (3/5) of those without atosiban compared with 14.3% (3/21) of those receiving atosiban, compared with 0% (0/58) in women with low NLR (<3.5). Prolonged antibiotics lowered post-operative CRP but did not alter CL loss. Atosiban exposure was differentially distributed by NLR status; however, due to confounding by indication and critically small subgroups, no inference regarding atosiban efficacy or clinical utility can be supported. Combined NLR and CRP predicted large shortening (ΔCL ≤ -5 mm) with an area under the curve (AUC) of 0.81.
Conclusion:
In this small (n = 84), single-center, retrospective cohort, pre-operative NLR and CRP were statistically associated with accelerated cervical shortening after cerclage. Atosiban and antibiotic exposure were determined by clinical indication, and subgroup analyses were based on severely inadequate sample sizes (n = 5, n = 2) with extreme confounding by indication. These findings are exploratory observations only. No causal inference, therapeutic claim, or clinical recommendation is justified. Prospective validation in randomized trials is essential.