Related Experiment Video
Updated: Jul 4, 2026
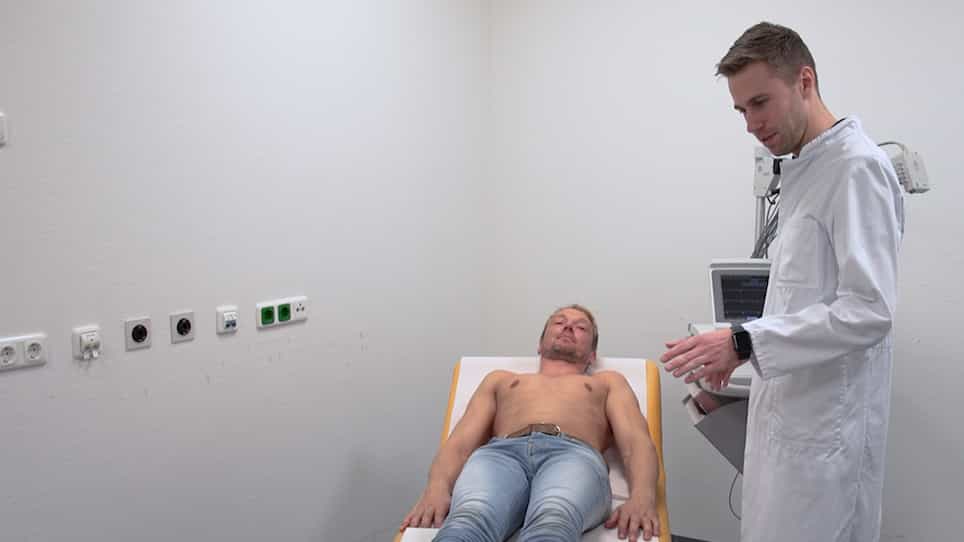

Patient Directed Recording of a Bipolar Three-Lead Electrocardiogram using a Smartwatch with ECG Function
Published on: December 11, 2019
Artificial Intelligence-Enabled Cardiac Function Estimation from Phone Videos of Echocardiograms
Dhawal Modi1, Jay Kim1, Alexander Ye2
1Division of Research, Kaiser Permanente Northern California, Pleasanton, California, USA.

Importance:
Mobile phone-recorded echocardiogram videos are commonly used in point-of-care, telemedicine, and resource-limited workflows, but artificial intelligence models for left ventricular ejection fraction (LVEF) estimation have primarily been evaluated on native Digital Imaging and Communications in Medicine (DICOM) videos.
Objective:
To evaluate whether previously described artificial intelligence models for LVEF estimation retain performance when applied to mobile phone-recorded echocardiographic videos.
Design:
Multicenter model validation study comparing model-estimated LVEF with clinician-reported LVEF.
Setting:
Three medical centers: Kaiser Permanente Northern California, Beth Israel Deaconess Medical Center through MIMIC-IV-ECHO, and Cedars-Sinai Medical Center.
Participants:
Source studies with clinician-reported LVEF and apical 4-chamber or apical 2-chamber views, yielding 6209 phone-recorded videos from 2648 studies and 2611 patients.
Exposures:
Mobile phone recording of native echocardiographic videos and fine-tuning of pretrained models using mobile phone-recorded videos from the Kaiser Permanente Northern California training cohort.
Main Outcomes And Measures:
Mean absolute error in ejection fraction percentage points, R2 for continuous estimation, and area under the receiver operating characteristic curve for identifying ejection fraction greater than 50%.
Results:
The study included 6209 mobile phone-recorded echocardiographic videos from 2648 studies and 2611 patients; the weighted mean age was 68.4 years, and 1031 patients were male (39.5%). Without phone-video fine-tuning, the primary model achieved a mean absolute error of 7.00 percentage points, coefficient of determination of 0.49, and area under the receiver operating characteristic curve of 0.91 on phone-recorded videos; corresponding native DICOM performance was 6.08 percentage points, 0.60, and 0.93, respectively. On the 2396-video fine-tuning evaluation cohort, fine-tuning improved primary model performance to a mean absolute error of 6.96 percentage points, coefficient of determination of 0.61, and area under the receiver operating characteristic curve of 0.93. Fine-tuning the public EchoNet-Dynamic model improved performance from 9.36 percentage points, 0.37, and 0.84 to 7.86 percentage points, 0.50, and 0.89, respectively. Progressive central zoom preprocessing degraded model performance.
Conclusions And Relevance:
These findings suggest that artificial intelligence-assisted left ventricular ejection fraction estimation from mobile phone-recorded echocardiograms may be feasible when native image export is unavailable, although prospective evaluation is needed before clinical deployment.
