Related Experiment Video
Updated: Jul 4, 2026
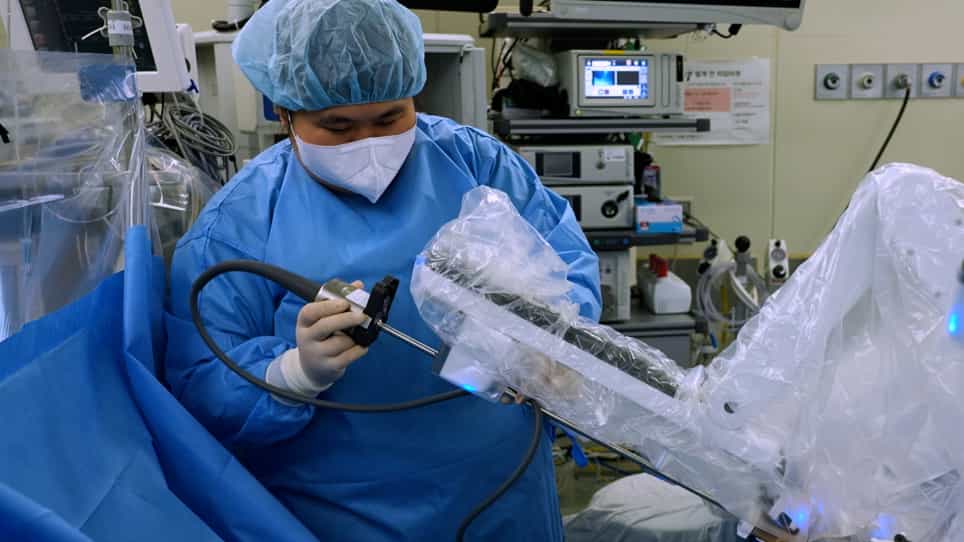
Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Outcomes of belatacept-based quadruple immunosuppression therapy in kidney transplant recipients with persistent
Basheer Ahamad Kummangal1, Ali Olyaei1, Angelo de Mattos1
1Division of Nephrology and Hypertension, Oregon Health and Science University, Portland, OR, United States.

We conducted a retrospective review of adult kidney transplant recipients (KTRs) who received belatacept in addition to calcineurin inhibitors, antimetabolites, and corticosteroids for recurrent or refractory rejection or for persistent donor-specific antibodies (DSAs) unresponsive to standard therapy. Fifteen recipients were included. Kidney function remained stable on follow-up; median eGFR was 52 mL/min (R 23-91) at baseline and 54 mL/min (R 25-105) at 6 months (p = 0.15) after belatacept initiation. The DSA intensity declined significantly from a median of 4,990 mean fluorescence intensity (MFI) (R 0-23,305) at baseline to 1,644 MFI (R 0-6,903) at 3-6 months (p = 0.03). There was also a small reduction in biopsy-proven rejections from 85.7% to 63.6%. Infections occurred in most recipients (73.3%), with a majority arising more than 6 months after therapy initiation. Two patients developed post-transplant lymphoproliferative disorder (PTLD), each with either substantial prior exposure to lymphocyte-depleting agents or prolonged immunosuppression. Two deaths occurred, one related to PTLD and one to septic shock. These findings suggest that belatacept-based quadruple immunosuppression may reduce DSA and stabilize kidney function in patients with persistent alloimmunity, but without a statistically significant reduction in rejections. There is also a significant burden of infections and PTLD, highlighting the need for careful patient selection and caution before adopting this approach.
We conducted a retrospective review of adult kidney transplant recipients (KTRs) who received belatacept in addition to calcineurin inhibitors, antimetabolites, and corticosteroids for recurrent or refractory rejection or for persistent donor-specific antibodies (DSAs) unresponsive to standard therapy. Fifteen recipients were included. Kidney function remained stable on follow-up; median eGFR was 52 mL/min (R 23-91) at baseline and 54 mL/min (R 25-105) at 6 months (p = 0.15) after belatacept initiation. The DSA intensity declined significantly from a median of 4,990 mean fluorescence intensity (MFI) (R 0-23,305) at baseline to 1,644 MFI (R 0-6,903) at 3-6 months (p = 0.03). There was also a small reduction in biopsy-proven rejections from 85.7% to 63.6%. Infections occurred in most recipients (73.3%), with a majority arising more than 6 months after therapy initiation. Two patients developed post-transplant lymphoproliferative disorder (PTLD), each with either substantial prior exposure to lymphocyte-depleting agents or prolonged immunosuppression. Two deaths occurred, one related to PTLD and one to septic shock. These findings suggest that belatacept-based quadruple immunosuppression may reduce DSA and stabilize kidney function in patients with persistent alloimmunity, but without a statistically significant reduction in rejections. There is also a significant burden of infections and PTLD, highlighting the need for careful patient selection and caution before adopting this approach.
Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Kidney Transplant I: Introduction
 01:16
Kidney Transplant III: Nursing Management
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...