Related Experiment Video
Updated: Jul 4, 2026
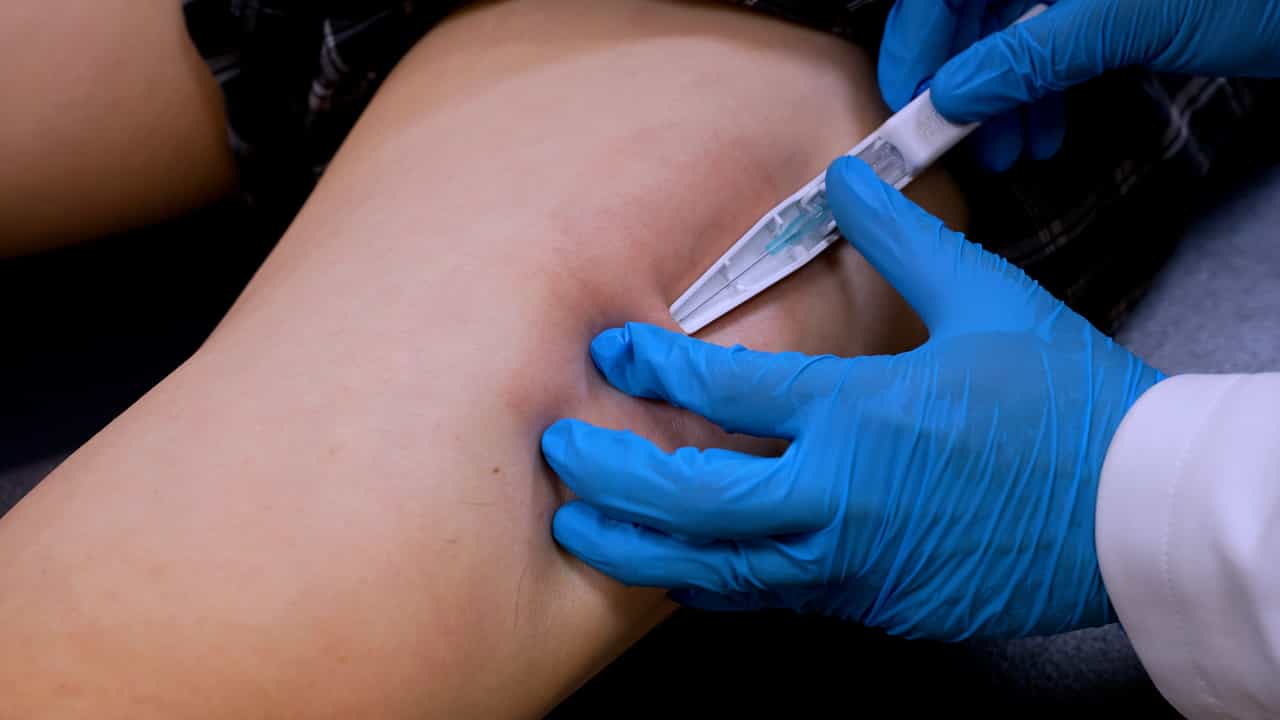

Fu's Subcutaneous Needling for Knee Osteoarthritis Pain
Published on: March 24, 2023
A Multicenter Randomized Pragmatic Trial Comparing Intra-Articular Injection, Genicular Nerve Block, and
Steven P Cohen1, Daniel O Scharfstein2, Robert W Hurley3
1Northwestern University Feinberg School of Medicine, Departments of Anesthesiology, Neurology, Physical Medicine & Rehabilitation, Psychiatry and Neurological Surgery; 259 E Erie St Ste 1400, Chicago, IL 60611.

Background:
Knee osteoarthritis (KOA) is a leading cause of chronic pain and disability worldwide, yet clinical guidelines disagree on how to escalate care when conservative management fails. Procedural interventions, including intra-articular injections, genicular nerve blocks (GNB), and genicular nerve radiofrequency ablation (GN-RFA), are used widely, but head-to-head comparative evidence is limited and recent RFA trials have produced inconsistent results, in part because prior studies have used controls that do not adequately mimic the procedural experience of the active arm.
Methods/Design:
SKOAP Phase 2 is a multisite, pragmatic, randomized comparative-effectiveness trial that is expected to enroll at least 900 knees across 30 U.S. centers. Knees will be randomized 1:1:1 to one of three interventions: (1) image-guided intra-articular hyaluronic acid combined with corticosteroid and local anesthetic (IA-HA+); (2) image-guided GNB with sustained-release liposomal bupivacaine and corticosteroid, followed by a sham radiofrequency procedure; or (3) comprehensive GN-RFA with post-lesioning corticosteroid injection. Participants randomized to GNB or GN-RFA will remain blinded to allocation for 12 weeks, supported by harmonized procedural environments, identical sedation and imaging protocols, a standardized sham-RFA sequence, and restricted documentation. This blinding design is rarely implemented in prior RFA trials and is central to the study's methodological rigor. The primary outcome is change in the modified Brief Pain Inventory (mBPI) from baseline to 12 weeks; secondary outcomes included pain interference, physical function, quality of life, and global improvement. Effectiveness will be evaluated using three prespecified estimands (modified intention-to-treat, receipt of intervention, and minimum effective dose) using augmented inverse-weighting methods that account for off-schedule assessments, loss to follow-up, and when appropriate non-adherence.
Discussion:
By combining pragmatic design with rigorous sham-controlled blinding and prespecified estimands, SKOAP Phase 2 will generate the most methodologically robust comparative evidence to date on procedural management of KOA pain and will directly inform guidelines and clinical decision-making on non-operative interventions including when and whether to escalate from intra-articular injection to nerve block to ablation.