Related Experiment Video
Updated: Jul 6, 2026
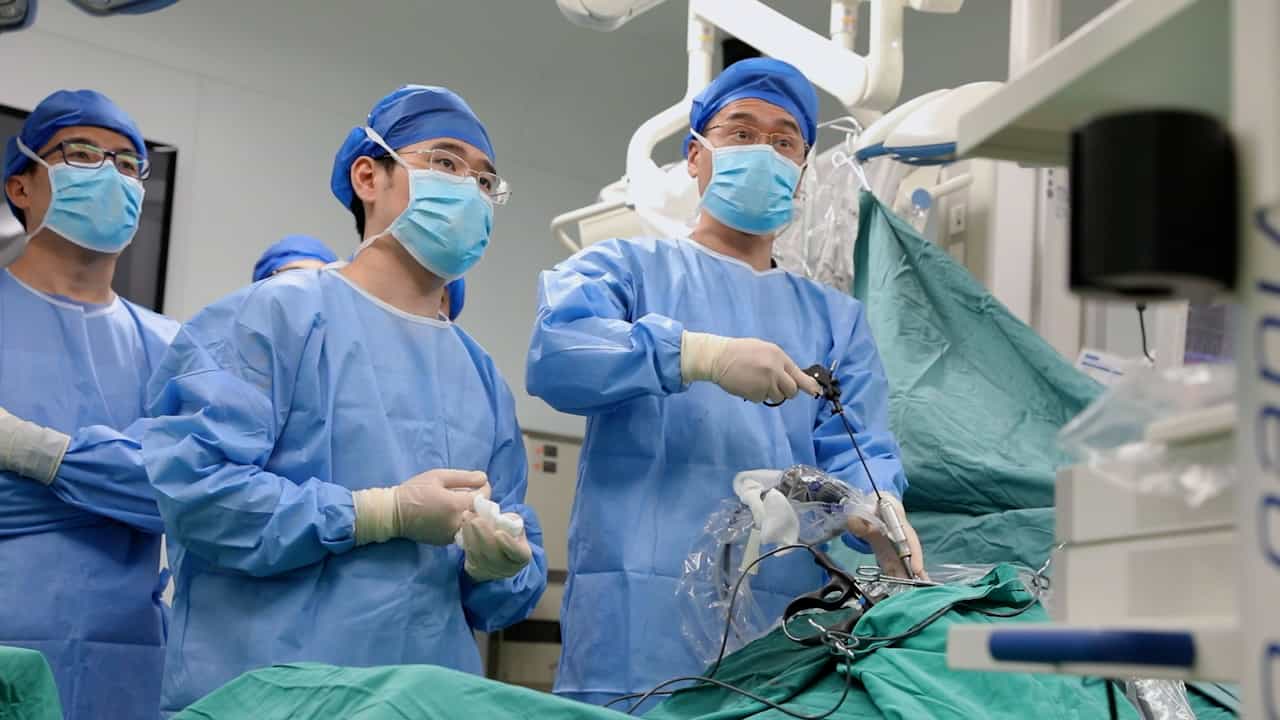

Percutaneous Endoscopic Unilateral-Approach Bilateral Decompression for Lumbar Spinal Stenosis
Published on: February 9, 2024
Improving Reliability of MRI Lumbar Spinal Stenosis Assessment Across Radiology and Spine Specialties: Impact of a
Pamela J Walsh1, Un Jung Lee2, Jason S Lipetz3
1Department of Radiology, Donald and Barbara Zucker School of Medicine at Hofstra, Northwell, 300 Community Drive, 1st Floor, Manhasset, NY 11030, USA (P.J.W.).

Rationale And Objectives:
Magnetic Resonance Imaging (MRI) is the preferred modality for evaluating Lumbar Spinal Stenosis (LSS), yet grading remains subjective and inconsistent. Currently, no standardized reporting system, such as the American College of Radiology Reporting and Data systems (RADS), exists for LSS. The objective of this study is to assess the impact of a structured educational intervention using a classification system, on correctness and interobserver reliability of MRI LSS grading among radiology and non-radiology spine physicians.
Materials And Methods:
Health Insurance Portability and Accountability Act-compliant, Institutional Review Board-approved retrospective study analyzed 114 lumbar disc levels. Thirty-seven physicians across six specialties (musculoskeletal radiology (MR), neuroradiology (NR), radiology residents (RR), orthopedic surgery, neurosurgery (NS) and physiatry (PH)) graded stenosis (none, mild, moderate, severe) in two phases: pre-intervention (routine practice) and post-intervention following training with a classification system. Cases correct and discrepant by more than one grade (ex: mild-severe) were compared to a reference standard. Descriptive statistics and analyses included paired t-test, Wilcoxon test and intraclass correlation coefficient (ICC).
Results:
Pre-intervention, overall correctness was 54.5% and improved to 61.2% post-intervention (p = 0.006). Cases discrepant more than one grade decreased from 3.7% to 2.0% (p = 0.002). Interobserver reliability improved significantly, with ICC increasing from 0.71 (95% CI: 0.65-0.76) to 0.75 (95% CI: 0.70-0.80); p = 0.030. Pre-intervention, musculoskeletal group had the highest percentage of cases correct (67.7%) and lowest discrepant cases (1.6%) and post-intervention, NR had the highest correct (64.9%) and lowest discrepant (0.7%). MR had the highest ICC pre (0.774 (0.709 to 0.829)) and post-intervention (0.781 (0.720 to 0.834)).
Conclusion:
Education and implementation of a standardized MRI LSS classification system significantly improved grading concordance and interobserver reliability across a large multidisciplinary physician cohort.