Related Experiment Video
Updated: Jul 6, 2026
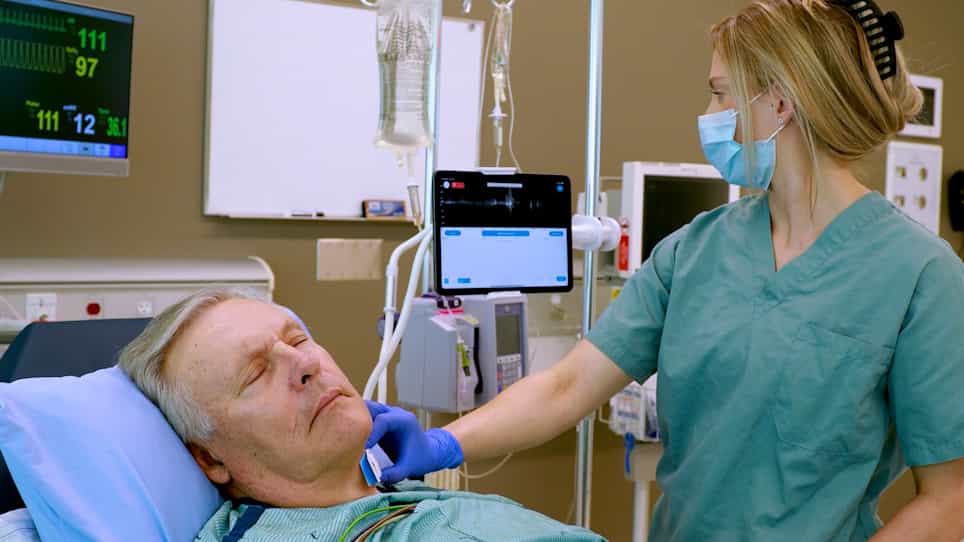

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Pulse pressure versus continuous flow monitoring for fluid responsiveness prediction during passive leg raising: a
Fatemeh Monjazebi1, Vahid Zamanzadeh2, Mansoureh Ashoub1
1Department of Medical Surgical Nursing, School of Nursing and Midwifery, Shahid Beheshti University of Medical Sciences, Tehran, Iran.

Background:
Accurate prediction of fluid responsiveness is essential in managing circulatory shock. While passive leg raising (PLR) is recommended in international guidelines, its diagnostic validity depends critically on the monitoring modality used to detect hemodynamic responses. In resource-limited settings, manual blood pressure measurement remains the predominant available technology, yet its adequacy for PLR interpretation has not been rigorously evaluated in an adequately powered study with an independent reference standard.
Objective:
To compare the diagnostic accuracy of manual pulse pressure change (ΔPP%) versus continuous flow monitoring (USCOM-1 A, ΔSV%) for predicting fluid responsiveness during PLR in intensive care unit (ICU) patients with undifferentiated shock, using echocardiographic cardiac output assessment as an independent reference standard.
Methods:
Prospective single-center diagnostic accuracy study enrolling consecutive ICU patients with undifferentiated shock at Sina Educational and Medical Center, Tehran, Iran (2020-2021). A standardized PLR protocol was performed with simultaneous blinded measurements by three independent operators: manual blood pressure via calibrated sphygmomanometer, continuous flow monitoring via USCOM-1 A, and echocardiographic velocity-time integral (VTI) measurement as the reference standard. Fluid responsiveness was defined as ≥ 15% cardiac output increase following 500 mL crystalloid challenge. Primary outcome was area under the receiver operating characteristic curve (AUC). The study followed Standards for Reporting Diagnostic Accuracy Studies (STARD) 2015 guidelines (Ethics approval: IR.SBMU.PHARMACY.REC.1399.316).
Results:
Of 124 patients analyzed (mean age 58.1 ± 19.8 years, 65.3% female), 58 (46.8%) were fluid responders. Continuous flow monitoring demonstrated acceptable diagnostic accuracy (AUC 0.712, 95% confidence interval [CI] 0.622-0.802; sensitivity 81.0%; specificity 61.8%; negative predictive value [NPV] 79.2%). Manual pulse pressure demonstrated significantly inferior discrimination (AUC 0.601, 95%CI 0.502-0.700; DeLong test P = 0.029) with critically low sensitivity (32.8%) and clinically inadequate NPV (57.8%). Bootstrap-corrected performance estimates confirmed the robustness of findings (USCOM AUC 0.708; Manual pulse pressure [PP] AUC 0.596). Mean pulse pressure remained essentially unchanged during PLR (+ 0.4 ± 4.6 mmHg, P = 0.287) despite significant proportional increases in both systolic (+ 3.7%) and diastolic (+ 5.6%) pressures, and despite echocardiographically confirmed stroke volume augmentation (left ventricular outflow tract [LVOT] VTI + 15.9%). The correlation between ΔPP% and ΔSV% was weak (r = 0.39, R²=0.15). Baseline method comparison between USCOM-derived and echocardiography-derived cardiac output showed low paired bias, although the percentage error exceeded the conventional interchangeability threshold, supporting interpretation of USCOM as a directional flow-monitoring index rather than a fully interchangeable substitute for echocardiography.
Conclusions:
In this single-center study, manual pulse pressure demonstrated insufficient sensitivity (32.8%) and inadequate NPV (57.8%) for reliable fluid responsiveness prediction during PLR. Our findings suggest it should be interpreted with considerable caution, particularly when the test result is negative. Continuous flow monitoring provides superior and clinically acceptable diagnostic accuracy when available, although USCOM should be interpreted as a directional flow-monitoring index rather than a fully interchangeable substitute for echocardiographic cardiac output measurement. The proportional pressure increase phenomenon provides a mechanistic explanation for this diagnostic limitation. These findings require multicenter validation before definitive practice recommendations can be issued.
More Related Videos

Related Concept Videos
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:17
Measurement of Blood Pressure
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:30
Equipments Used To Measure Blood Pressure
This invasive approach involves cannulating a peripheral artery. During each cardiac contraction, pressure generates mechanical motion within the catheter, transmitted through rigid, fluid-filled tubing to a transducer. This transducer converts mechanical motion into electrical signals displayed as waveforms on a monitor. An automatic flushing system prevents blood backflow. Due to the potential risk of unexpected arterial blood loss, this method is primarily used in intensive...
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure