Related Experiment Video
Updated: Jul 7, 2026


Portable Thermographic Screening for Detection of Acute Wallenberg's Syndrome
Published on: September 19, 2019
Lady Windermere Syndrome Presenting As Prolonged Febrile Illness in an Immunocompetent Woman
Paolo Romero Merino1, Mijali L Lerzundi Mamani2, Eslin Cipion-Bueno3
1Primary Health Care Management, Valladolid Este, Valladolid, ESP.

Lady Windermere syndrome is a distinct clinical entity associated with Mycobacterium avium complex infection that classically affects immunocompetent elderly women, particularly those with voluntary cough suppression, resulting in impaired airway clearance and mucus stasis within dependent bronchi. The condition has also been associated with a characteristic lean body habitus and thoracic skeletal abnormalities that may further compromise mucociliary clearance. We report the case of a 60-year-old woman with a history of pulmonary embolism and hypothyroidism who presented with a 45-day history of persistent nonproductive cough, intermittent fever, and right-sided chest discomfort. Physical examination revealed a lean body habitus and visible pectus excavatum. Laboratory studies demonstrated elevated inflammatory markers, and chest computed tomography showed bronchiectasis predominantly involving the middle lobe and lingula. Microbiological cultures confirmed Mycobacterium avium infection. The patient received a targeted 12-month multidrug regimen consisting of rifampicin, ethambutol, and azithromycin, achieving microbiological clearance and marked clinical improvement, with follow-up imaging demonstrating stable radiologic findings and sustained remission.
Lady Windermere syndrome is a distinct clinical entity associated with Mycobacterium avium complex infection that classically affects immunocompetent elderly women, particularly those with voluntary cough suppression, resulting in impaired airway clearance and mucus stasis within dependent bronchi. The condition has also been associated with a characteristic lean body habitus and thoracic skeletal abnormalities that may further compromise mucociliary clearance. We report the case of a 60-year-old woman with a history of pulmonary embolism and hypothyroidism who presented with a 45-day history of persistent nonproductive cough, intermittent fever, and right-sided chest discomfort. Physical examination revealed a lean body habitus and visible pectus excavatum. Laboratory studies demonstrated elevated inflammatory markers, and chest computed tomography showed bronchiectasis predominantly involving the middle lobe and lingula. Microbiological cultures confirmed Mycobacterium avium infection. The patient received a targeted 12-month multidrug regimen consisting of rifampicin, ethambutol, and azithromycin, achieving microbiological clearance and marked clinical improvement, with follow-up imaging demonstrating stable radiologic findings and sustained remission.
Related Concept Videos
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:25
Arboviral Encephalitis
 01:26
Rocky Mountain Spotted Fever
 01:19
Encephalitis l: Introduction
 01:26
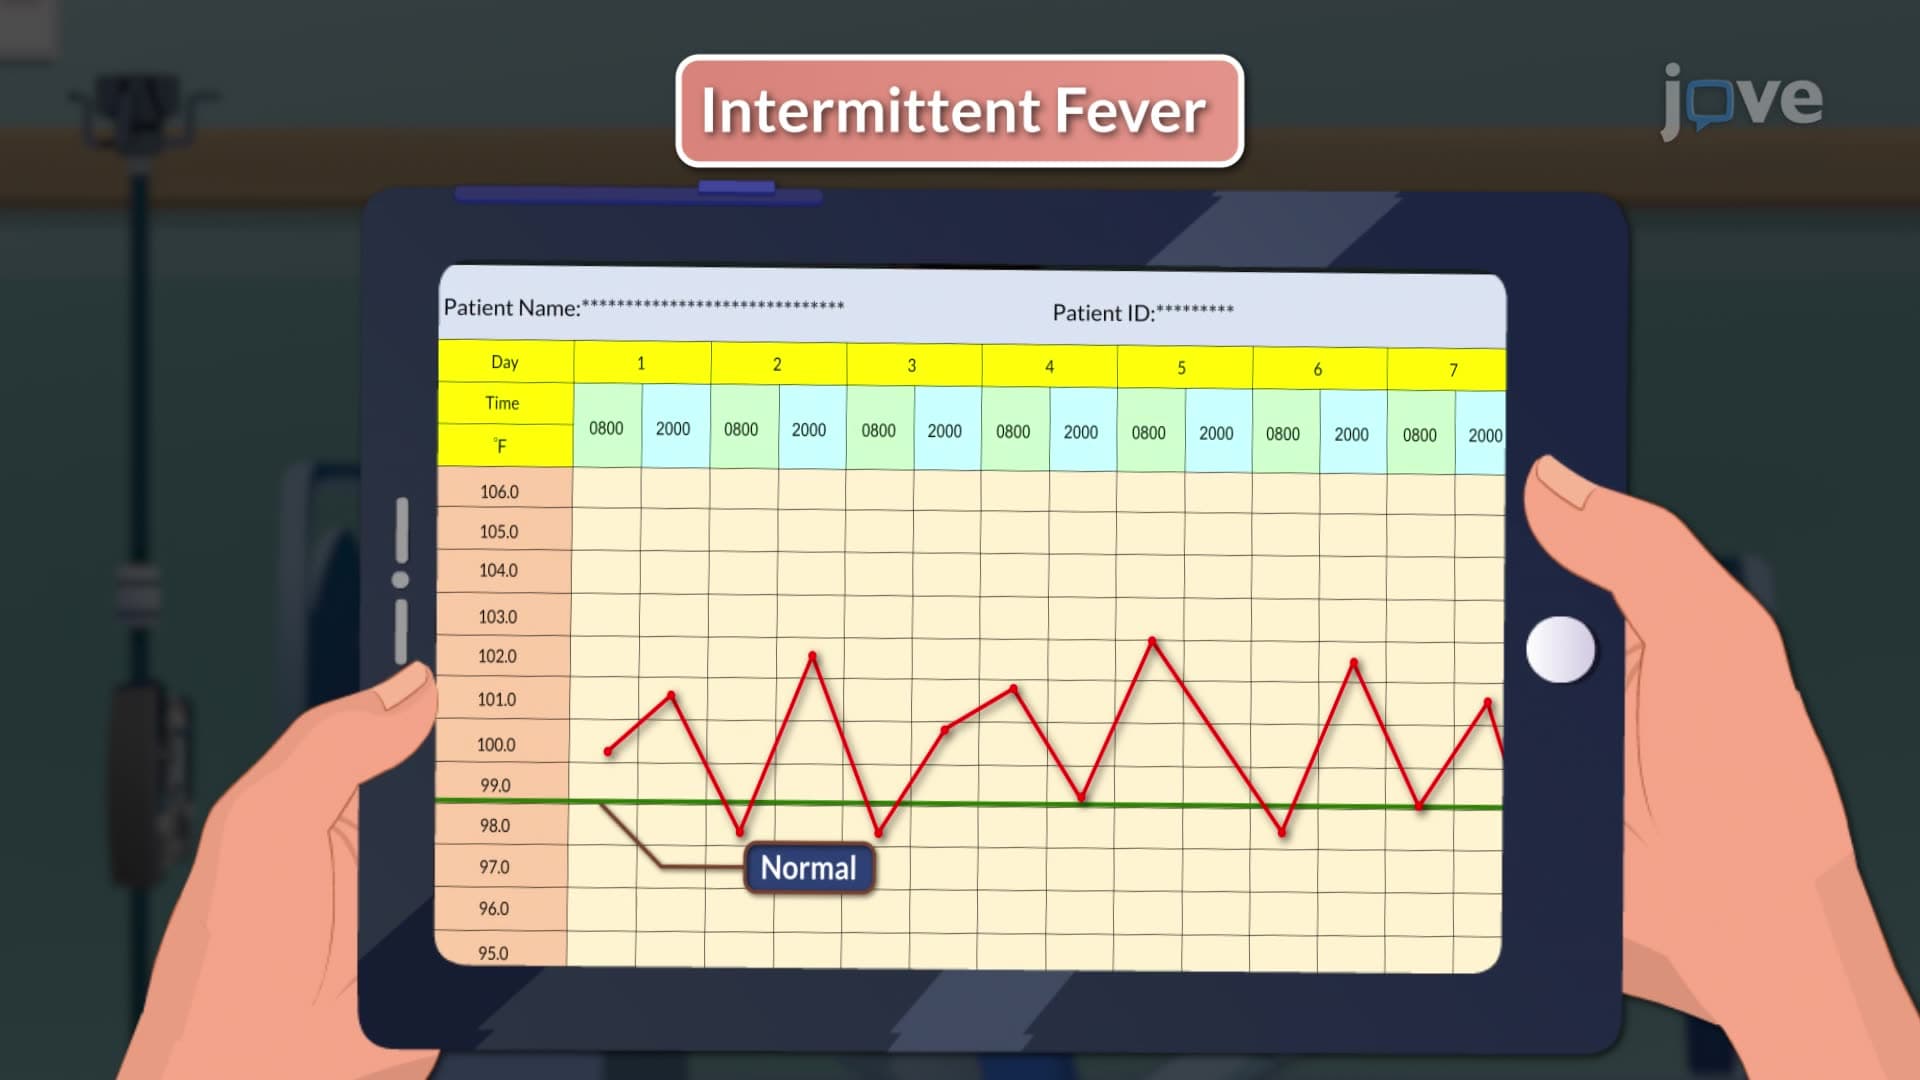
Patterns of Fever
 01:22
Bacterial Meningitis I: Introduction