Related Experiment Video
Updated: Jul 7, 2026


Treatment of Ankle Osteoarthritis with Total Ankle Replacement Through a Lateral Transfibular Approach
Published on: January 24, 2018
Predictors of Limited Weight-Bearing Dorsiflexion Following Total Ankle Arthroplasty
Grant M Thomas1, Joseph A S McCahon1,2, Yoni Dulitzki1
1Rothman Orthopaedic Institute at Thomas Jefferson University, Philadelphia, PA, USA.

Background:
Limited dorsiflexion (DF) after total ankle arthroplasty (TAA) is a challenge that has been associated with worse functional outcomes and lower patient-reported satisfaction. The purpose of this study was to identify predictive variables for limited DF following TAA.
Methods:
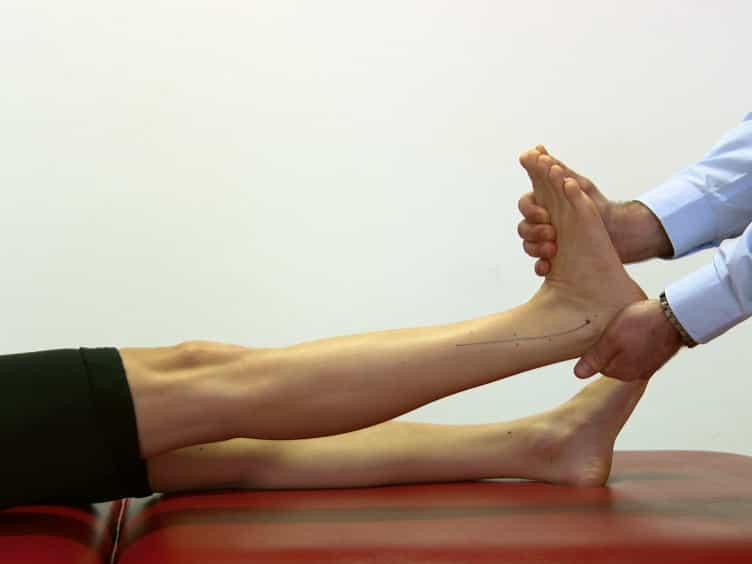
A retrospective cohort study was conducted on patients who underwent elective primary TAA between 2013 and 2023 by a single surgeon. Postoperative range of motion (ROM) was assessed using weight-bearing lateral radiographs obtained in maximal DF and plantarflexion (PF). Limited DF was defined as <20° and preoperative DF was based solely on clinical assessment (C-DF). Demographic variables, medical comorbidities, surgical history, and adjunctive procedures, including gastrocnemius recession and tendo-Achilles lengthening (TAL), were collected and compared between patients who achieved full vs limited postoperative DF. Additionally, Foot and Ankle Ability Measure activities of daily living subscale (FAAM-ADL) and visual analog scale (VAS) scores were collected. Multivariable logistic regression was performed to identify independent predictors of final DF.
Results:
A total of 175 patients were included in this study, with 111 (63.4%) demonstrating limited postoperative DF and 64 (36.6%) achieving full DF at a mean 3.3 years. Age was significantly greater in the full DF group (65.5 vs 61.5 years, P = .013). No significant associations were identified between body mass index / weight, tobacco use, diabetes, sex, medical comorbidities, polyethylene size, or adjuvant procedures and postoperative DF following TAA. Prior open reduction internal fixation was more prevalent in patients with limited DF (P < .05), whereas postoperative FAAM-ADL scores were more favorable in the full DF group (70.0 vs 86.9, P = .010). Multivariable regression analyses identified full C-DF as the only significant independent predictor of improved postoperative DF following TAA.
Conclusion:
Preoperative clinical dorsiflexion was the only significant independent predictor of postoperative dorsiflexion following TAA. A thorough preoperative discussion regarding anticipated postoperative motion can help establish appropriate expectations and potentially enhance patient satisfaction following TAA.