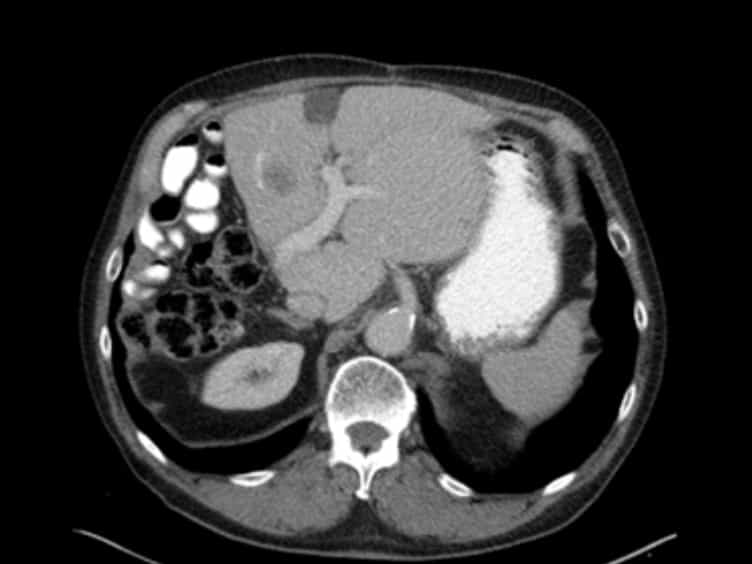
Prediction of recurrence in patients with mass-forming intrahepatic cholangiocarcinoma using computed
Hang Li1, Hongyan Yang2, Lei Xu3
1Unit of Radiology, Department of Clinical Science, Intervention and Technology (CLINTEC), Karolinska Institutet, Stockholm, Sweden; Department of Radiology, Sichuan Academy of Medical Sciences and Sichuan Provincial People's Hospital, 32# Second Section of First Ring Road, Qingyang District, Chengdu 610070, Sichuan, China; Department of Radiology, Karolinska University Hospital Huddinge, Stockholm, Sweden.

Objectives:
To evaluate if preoperative imaging features from CT at mass-forming intrahepatic cholangiocarcinoma (MF-iCCA) are related to histo-pathologic factors, and to evaluate if those associations can be used to construct an imaging score to predict postoperative recurrence.
Material And Methods:
Consecutive patients with MF-iCCA who underwent preoperative contrast-enhanced CT at two centers between September 2017 and December 2025 were retrospectively reviewed by two radiologists. After independent annotation of 16 imaging features, univariate and multivariate regression analyses were performed to identify independent predictors for high-risk histo-pathologic factors (microvascular invasion, LNM [lymph node metastasis], or poor tumor differentiation). A risk scoring system was developed and used to predict very early recurrence (VER) and early recurrence (ER).
Results:
In total 152 patients (median age, 62 years [IQR, 54-69 years]; 57 women) were included from two medical centers (training cohort: n = 109; external validation cohort: n = 43). Peritumoral enhancement at arterial phase had the strongest association with high-risk histo-pathologic factors, followed by multinodularity, intrahepatic bile duct dilation, and CT-reported LNM (P < 0.05, all). The four features were used to construct the risk scoring system. Area under the curve (AUC) of VER-weighted and ER-weighted risk scoring system for high-risk histo-pathologic factors was 0.827 and 0.829 in external validation cohort, respectively. The risk scoring system based on high-risk histo-pathologic factors showed superior prognostic performance for VER (AUC, 0.870 [95% CI: 0.761, 0.978]) and ER (AUC, 0.860 [95% CI: 0.737, 0.983]) in external validation cohort.
Conclusion:
Recurrence of MF-iCCA can be predicted by evaluating preoperative imaging features at CT.