Related Experiment Video
Updated: Jul 8, 2026
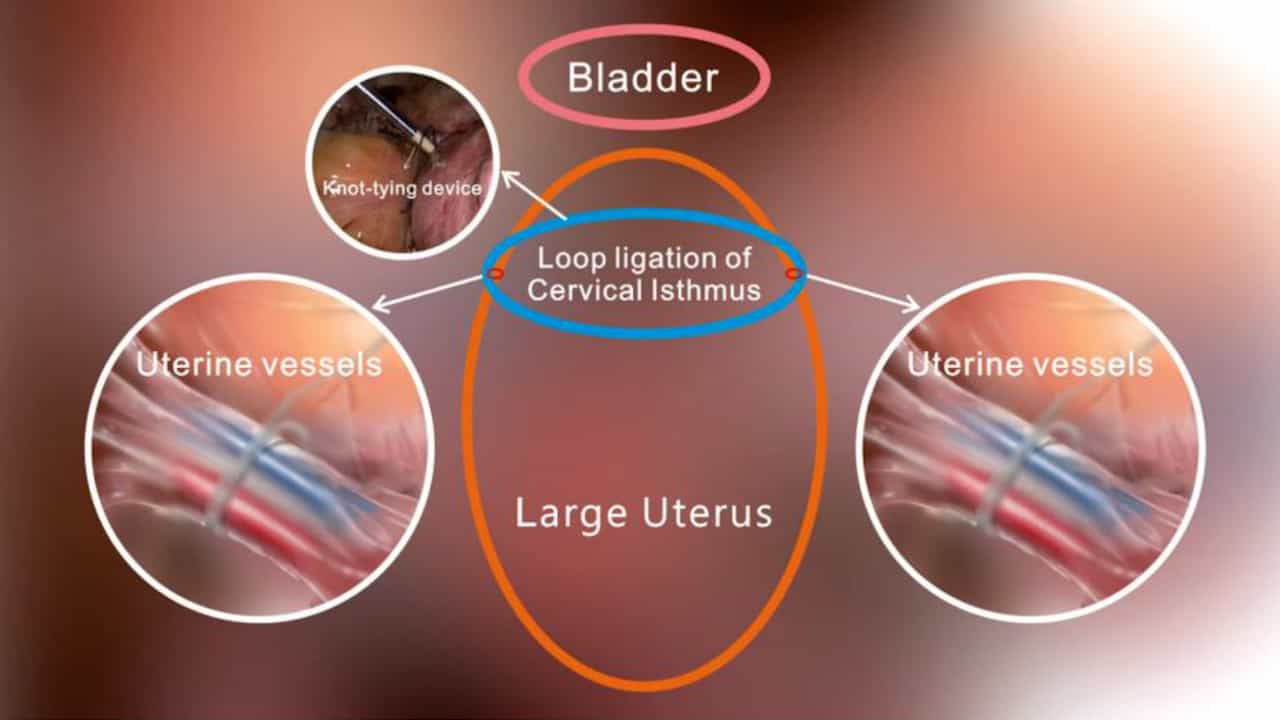

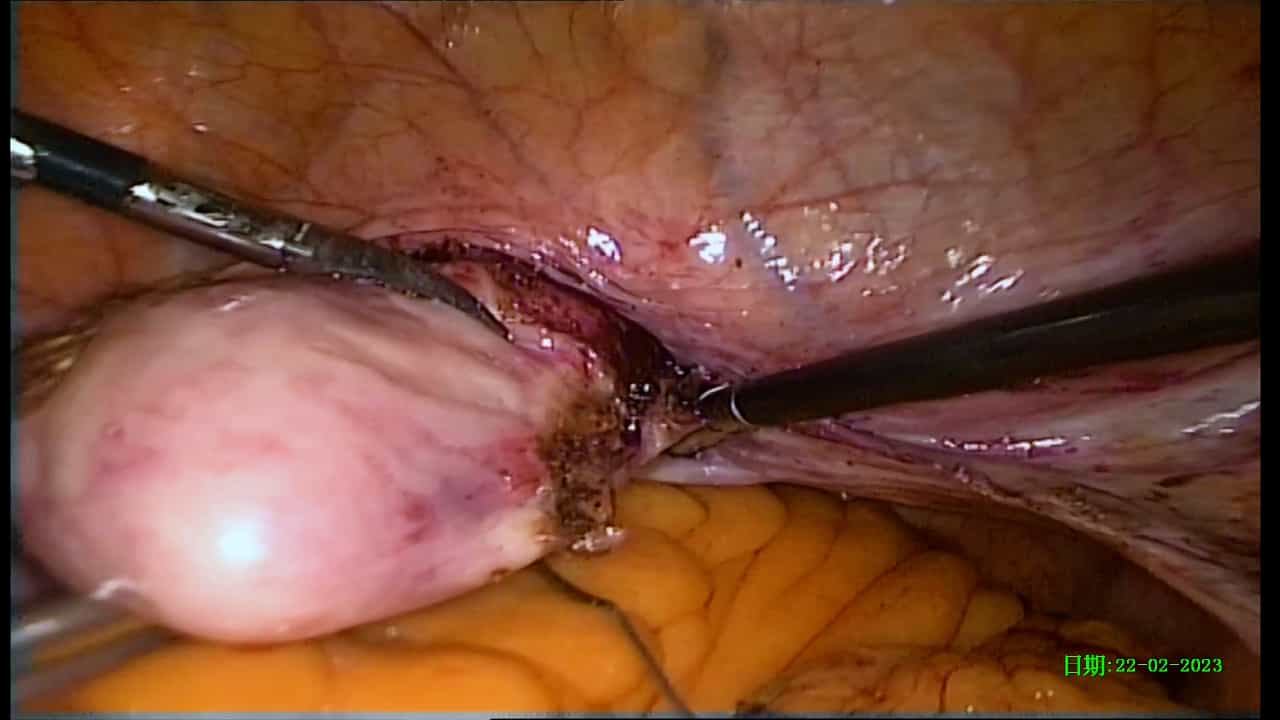
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Preoperative risk score for invasive uterus-sparing hemostasis at cesarean delivery: a retrospective cohort study
Ying Chen1, Zishu Zhan2, Sheng Wan1
1The International Peace Maternity and Child Health Hospital, Shanghai Key Laboratory of Embryo Original Disease, School of Medicine, Shanghai Jiao Tong University, Shanghai, China.

Background:
To develop a simple preoperative risk score identifying women requiring invasive hemostatic interventions during cesarean delivery.
Methods:
This retrospective cohort included women undergoing cesarean delivery at a Hainan maternity hospital. The primary outcome was intraoperative use of intrauterine balloon tamponade and/or uterine artery ligation. Continuous variables were compared using Student's t test or Mann-Whitney U test, and categorical variables using chi-square or Fisher's exact test. Multivariable logistic regression identified independent risk factors, which were translated into an integer-based risk score. Model performance was assessed using discrimination and calibration metrics. Women were classified into three risk categories. For each risk group, mean scores were calculated and radar-chart personas was created.
Results:
Among 8,687 cesarean deliveries, 386 (4.44%) required invasive hemostatic interventions. These women had greater blood loss, larger hemoglobin declines, higher transfusion rates, and more frequent peripartum hysterectomy. Independent predictors included placenta previa, low-lying placenta, severe preoperative anemia, prior postpartum hemorrhage, multiple gestation, preeclampsia, large leiomyoma, chorioamnionitis, and low platelet count. Based on these factors, we derived a preoperative risk score demonstrated good discrimination (AUC 0.7642, 95% CI: 0.7430-0.8305). The estimated probability of invasive hemostasis increased from about 2% in the low-risk group to (2.80 ~ 5.84)% in the medium-risk group and approximately 8% in the high-risk group. Although comprising only 8.28% of the cohort, the high-risk group accounted for 44% of all procedures.
Conclusions:
A simple preoperative risk score using routinely available variables can stratify the likelihood of invasive uterus-sparing hemostatic interventions during cesarean delivery and may help optimize perioperative preparedness.