Related Experiment Videos
Blood Pressure Phenotypes and Cardio-Kidney Outcomes: Findings From UK Biobank Data
Yongin Cho1, Hye-Sun Park2, Jong Ho Jhee3
1Department of Endocrinology and Metabolism, Inha University School of Medicine, Incheon, Republic of Korea (Y.C.).

Insights
Different blood pressure (BP) patterns, not just high BP, increase cardio-kidney outcome (CKO) risks. Understanding these distinct BP phenotypes is crucial for managing CKO and preventing cardiovascular and kidney diseases.
Area of Science:
- Cardiology
- Nephrology
- Public Health
Background:
- Hypertension is a primary driver of cardio-kidney outcomes (CKO).
- Specific blood pressure (BP) phenotypes and their impact on CKO require further investigation.
- This study addresses the need to understand the independent contributions of various BP phenotypes to CKO.
Purpose of the Study:
- To evaluate the independent contributions of distinct blood pressure (BP) phenotypes to cardio-kidney outcomes (CKO).
- To analyze the association between different BP classifications and the risk of CKO in a large population cohort.
Main Methods:
- A prospective, population-based study utilizing UK Biobank data from 2006-2010.
- Classification of participants into five BP phenotypes: normotension, systolic-diastolic hypertension, isolated systolic hypertension, isolated diastolic hypertension, and isolated low diastolic BP.
- Primary outcome (CKO) defined as a composite of incident chronic kidney disease, major cardiovascular events, and all-cause mortality, analyzed using multivariable Cox proportional hazards models.
Main Results:
- Analysis included 322,328 participants with a median follow-up of 13.6 years, during which 32,440 CKO events occurred.
- All identified BP phenotypes demonstrated an increased risk of CKO compared to normotension.
- Specific findings include elevated CKO risks for isolated systolic hypertension (HR, 1.22), systolic-diastolic hypertension (HR, 1.21), isolated diastolic hypertension (HR, 1.11), and isolated low diastolic BP (HR, 1.10).
Conclusions:
- Distinct blood pressure (BP) phenotypes, beyond absolute thresholds, are associated with differential risks for cardio-kidney outcomes (CKO).
- Further interventional studies are warranted to explore strategies targeting combined systolic-diastolic BP phenotypes to mitigate CKO risk.
Background:
Hypertension is a leading cause of cardio-kidney outcomes (CKO). However, distinct blood pressure (BP) phenotypes and their effect on CKO remain underexplored. This study aimed to evaluate the independent contributions of BP phenotypes to CKO.
Methods:
This prospective, population-based study included UK Biobank participants enrolled between 2006 and 2010 with baseline systolic BP ≥90 mm Hg and estimated glomerular filtration rate ≥60 mL/min per 1.73 m2, excluding those with prior chronic kidney disease and cardiovascular disease. Five BP phenotypes were constructed based on the 2017 American Heart Association hypertension criteria (≥130/80 mm Hg): normotension, systolic-diastolic hypertension, isolated systolic hypertension, isolated diastolic hypertension, and isolated low diastolic BP. The primary outcome was CKO, a composite of incident chronic kidney disease, 3-point major cardiovascular events, and all-cause mortality based on the International Classification of Diseases and Office of Population Censuses and Surveys Classification of Interventions and Procedures, Version 4, codes. Associations between BP phenotypes and CKO were evaluated using multivariable Cox proportional hazards models adjusted for demographic, lifestyle, and clinical covariates.
Results:
Among 322 218 participants (mean age, 55.8±8.1 years; 42.5% men), 61 918 (19.2%) had normotension, 159 853 (49.6%) had systolic-diastolic hypertension, 43 939 (13.6%) had isolated systolic hypertension, 28 169 (8.7%) had isolated diastolic hypertension, and 28 339 (8.8%) had isolated low diastolic BP. Over a median follow-up of 13.6 years, 32 440 CKO events occurred. All BP phenotypes were associated with an increased CKO risk compared with normotension: isolated systolic hypertension (hazard ratio, 1.22 [95% CI, 1.17-1.27]), systolic-diastolic hypertension (hazard ratio, 1.21 [95% CI, 1.16-1.25]), isolated diastolic hypertension (hazard ratio, 1.11 [95% CI, 1.05-1.17]), and isolated low diastolic BP (hazard ratio, 1.10 [95% CI, 1.05-1.17]).
Conclusions:
Distinct BP phenotypes beyond absolute BP thresholds confer differential risks for CKO. Interventional studies are needed to evaluate strategies targeting combined systolic-diastolic phenotypes to reduce CKO risk.
Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:30
Blood Pressure
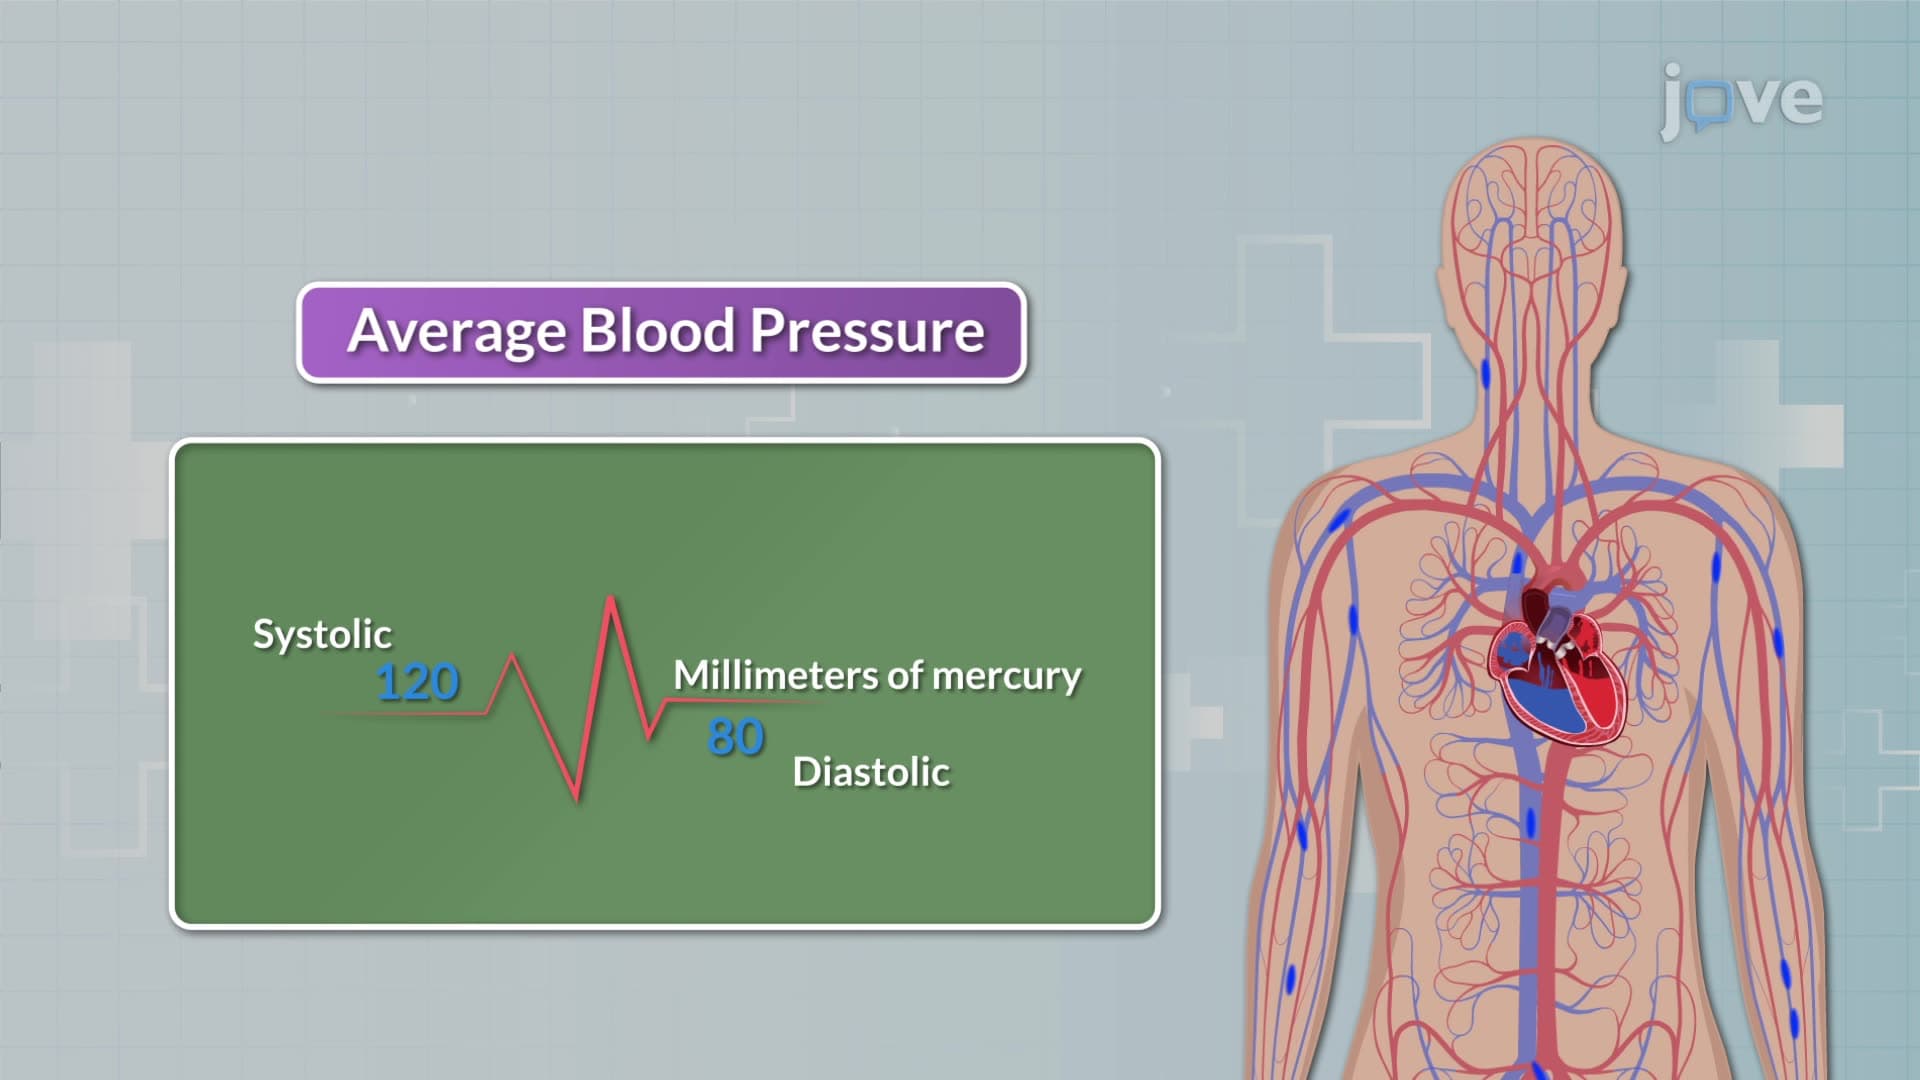
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...
 01:24
Blood Pressure
 01:29
Hypertension II: Pathophysiology