Related Experiment Video
Updated: Jul 9, 2026
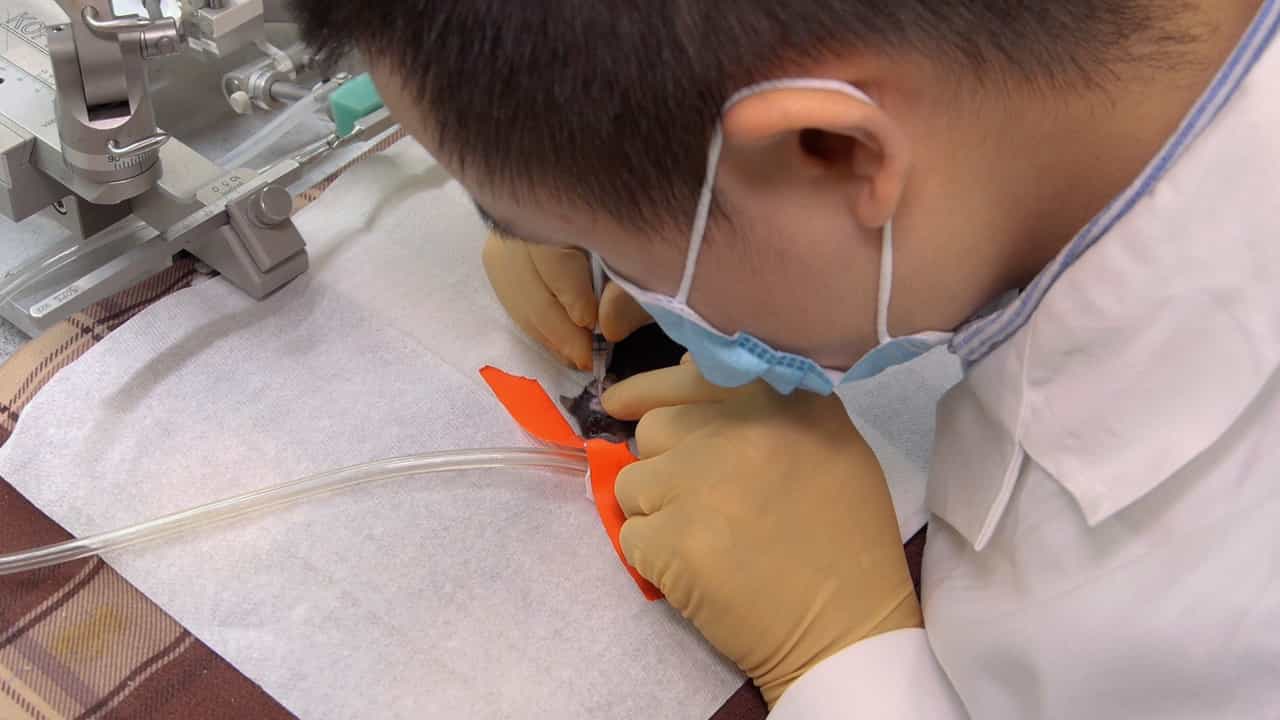

Temporomandibular Joint Pain Measurement by Bite Force and Von Frey Filament Assays in Mice
Published on: September 13, 2024
Does adding ultrasonography to clinical-psychosocial measures improve discrimination for temporomandibular disorders?
Raquel Delgado-Delgado1,2, Sebastián Truyols-Domínguez1,2, Orlando Conde-Vázquez1,3
1Grupo de Investigación Fisioterapia y Salud, Departamento de Fisioterapia, Facultad HM de Ciencias de la Salud, Universidad Camilo José Cela, Villanueva de la Cañada, Madrid, Spain.

Purpose:
To compare ultrasonography (US) measures and symptoms between temporomandibular disorders (TMD) and non-TMD groups and to quantify the incremental diagnostic value of US beyond a clinical-psychosocial core.
Materials And Methods:
This cross-sectional study included 57 adults (28 with TMD; 29 without TMD) assessed using the Diagnostic Criteria for Temporomandibular Disorders. US measured the lateral condyle-capsule distance and masseter thickness. The clinical-psychosocial core comprised pain intensity and disability, jaw function, oral behaviors, central sensitization, pain distribution, and pressure pain thresholds. Penalized logistic regression with paired nested cross-validation was used to compare 3 models: A (core), B (US only), and C (combined). Performance was evaluated using the area under the receiver operating characteristic curve (AUC) and Brier score. Incremental value was assessed using paired changes in AUC, net reclassification improvement, integrated discrimination improvement, and decision-curve analysis.
Results:
Anthropometric characteristics did not differ between groups. US measures showed no between-group differences, whereas psychosocial and pain-related measures did. Model A demonstrated good discrimination (AUC = 0.827). The US-only model performed poorly, and adding US to the core did not improve performance (AUC = 0.781); the paired difference in AUC was -0.051 (95% CI: -0.115 to 0.004). Reclassification and decision-curve analyses favored the core model. Sensitivity analyses (all pressure pain threshold sites and multiple imputation) yielded consistent results.
Conclusion:
US did not provide incremental diagnostic value beyond a clinical-psychosocial core for TMD classification and tended to worsen reclassification and clinical utility. Routine ultrasonography for general TMD diagnosis appears unwarranted and may be reserved for targeted structural indications. Larger, validated studies are needed.

